p.74 抽出テキスト
disease. The role of palliative and supportive care spans the entire course of HF, beginning early in the disease, intensifying as the condition progresses, and extending into caregiver bereavement. Evidence supports the use of multidisciplinary palliative care in people with advanced HF to improve patient-reported outcomes (symptom burden, depression, functional status, QoL), but trials do not identify who would benefit most from specialist palliative referral.1063–1065 There are no sufficiently robust multicentre evaluation phase trials to provide generalizable findings.

12 Specific conditions

12.1 Pregnancy and heart failure

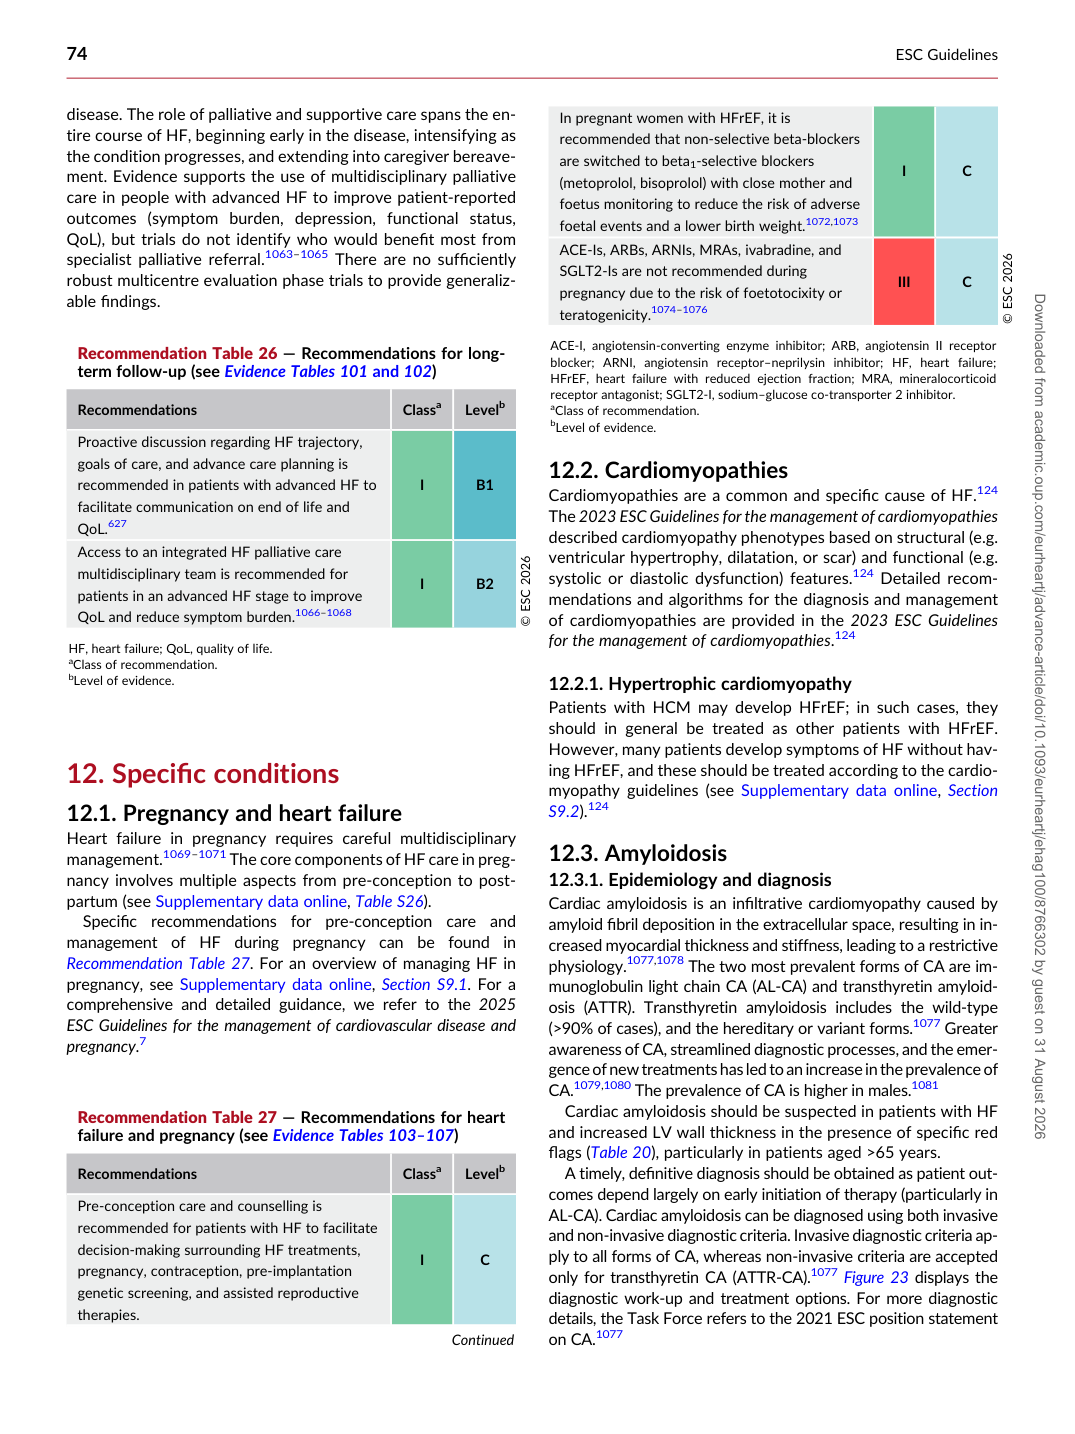
Heart failure in pregnancy requires careful multidisciplinary management.1069–1071 The core components of HF care in pregnancy involves multiple aspects from pre-conception to postpartum (see Supplementary data online, Table S26). Specific recommendations for pre-conception care and management of HF during pregnancy can be found in Recommendation Table 27. For an overview of managing HF in pregnancy, see Supplementary data online, Section S9.1. For a comprehensive and detailed guidance, we refer to the 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy.7 12.2 Cardiomyopathies

Cardiomyopathies are a common and specific cause of HF.124 The 2023 ESC Guidelines for the management of cardiomyopathies described cardiomyopathy phenotypes based on structural (e.g. ventricular hypertrophy, dilatation, or scar) and functional (e.g. systolic or diastolic dysfunction) features.124 Detailed recommendations and algorithms for the diagnosis and management of cardiomyopathies are provided in the 2023 ESC Guidelines for the management of cardiomyopathies.124

12.2.1 Hypertrophic cardiomyopathy

Patients with HCM may develop HFrEF; in such cases, they should in general be treated as other patients with HFrEF. However, many patients develop symptoms of HF without having HFrEF, and these should be treated according to the cardiomyopathy guidelines (see Supplementary data online, Section S9.2).124

12.3 Amyloidosis

12.3.1. Epidemiology and diagnosis Cardiac amyloidosis is an infiltrative cardiomyopathy caused by amyloid fibril deposition in the extracellular space, resulting in increased myocardial thickness and stiffness, leading to a restrictive physiology.1077,1078 The two most prevalent forms of CA are immunoglobulin light chain CA (AL-CA) and transthyretin amyloidosis (ATTR). Transthyretin amyloidosis includes the wild-type (>90% of cases), and the hereditary or variant forms.1077 Greater awareness of CA, streamlined diagnostic processes, and the emergence of new treatments has led to an increase in the prevalence of CA.1079,1080 The prevalence of CA is higher in males.1081 Cardiac amyloidosis should be suspected in patients with HF and increased LV wall thickness in the presence of specific red flags (Table 20), particularly in patients aged >65 years. A timely, definitive diagnosis should be obtained as patient outcomes depend largely on early initiation of therapy (particularly in AL-CA). Cardiac amyloidosis can be diagnosed using both invasive and non-invasive diagnostic criteria. Invasive diagnostic criteria apply to all forms of CA, whereas non-invasive criteria are accepted only for transthyretin CA (ATTR-CA).1077 Figure 23 displays the diagnostic work-up and treatment options. For more diagnostic details, the Task Force refers to the 2021 ESC position statement on CA.1077

Recommendation Table 26 — Recommendations for longterm follow-up (see Evidence Tables 101 and 102)

Recommendations Classa Levelb Proactive discussion regarding HF trajectory, goals of care, and advance care planning is recommended in patients with advanced HF to facilitate communication on end of life and QoL.627 I B1 Access to an integrated HF palliative care multidisciplinary team is recommended for patients in an advanced HF stage to improve QoL and reduce symptom burden.1066–1068 I B2 © ESC 2026 HF, heart failure; QoL, quality of life. aClass of recommendation. bLevel of evidence.

Recommendation Table 27 — Recommendations for heart failure and pregnancy (see Evidence Tables 103–107)

Recommendations Classa Levelb Pre-conception care and counselling is recommended for patients with HF to facilitate decision-making surrounding HF treatments, pregnancy, contraception, pre-implantation genetic screening, and assisted reproductive therapies. I C

Continued In pregnant women with HFrEF, it is

recommended that non-selective beta-blockers are switched to beta1-selective blockers (metoprolol, bisoprolol) with close mother and foetus monitoring to reduce the risk of adverse foetal events and a lower birth weight.1072,1073 I C ACE-Is, ARBs, ARNIs, MRAs, ivabradine, and SGLT2-Is are not recommended during pregnancy due to the risk of foetotocixity or teratogenicity.1074–1076 III C © ESC 2026 ACE-I, angiotensin-converting enzyme inhibitor; ARB, angiotensin II receptor blocker; ARNI, angiotensin receptor–neprilysin inhibitor; HF, heart failure; HFrEF, heart failure with reduced ejection fraction; MRA, mineralocorticoid receptor antagonist; SGLT2-I, sodium–glucose co-transporter 2 inhibitor. aClass of recommendation. bLevel of evidence. Downloaded from academic.oup.com/eurheartj/advance-article/doi/10.1093/eurheartj/ehag100/8766302 by guest on 31 August 2026