p.49 抽出テキスト
Check frequently for hypotension/hypoperfusion. Check serum creatinine and electrolytese at least every 24 h

FMT initiation/uptitration

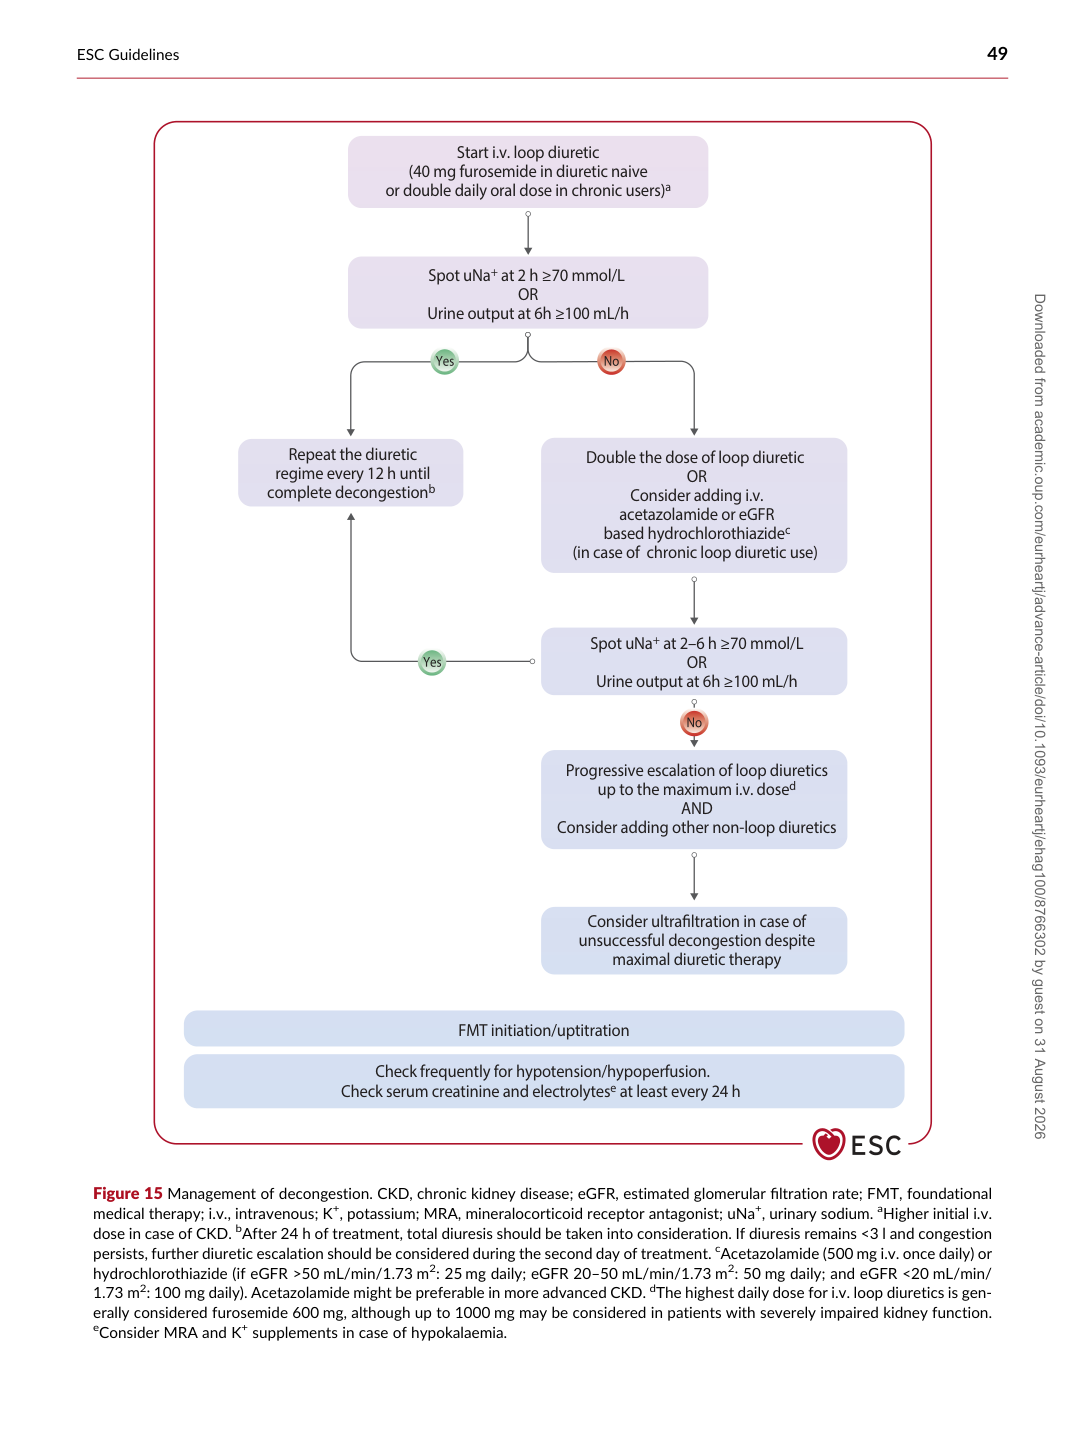
Start i.v. loop diuretic (40 mg furosemide in diuretic naive or double daily oral dose in chronic users)a

Spot uNa+ at 2 h ≥70 mmol/L OR Urine output at 6h ≥100 mL/h

Repeat the diuretic regime every 12 h until complete decongestionb Double the dose of loop diuretic

OR Consider adding i.v. acetazolamide or eGFR based hydrochlorothiazidec (in case of  chronic loop diuretic use)

Spot uNa+ at 2–6 h ≥70 mmol/L OR Urine output at 6h ≥100 mL/h

Progressive escalation of loop diuretics

up to the maximum i.v. dosed AND Consider adding other non-loop diuretics

Consider ultrafiltration in case of unsuccessful decongestion despite

maximal diuretic therapy

Figure 15 Management of decongestion. CKD, chronic kidney disease; eGFR, estimated glomerular filtration rate; FMT, foundational medical therapy; i.v., intravenous; K+, potassium; MRA, mineralocorticoid receptor antagonist; uNa+, urinary sodium. aHigher initial i.v. dose in case of CKD. bAfter 24 h of treatment, total diuresis should be taken into consideration. If diuresis remains <3 l and congestion persists, further diuretic escalation should be considered during the second day of treatment. cAcetazolamide (500 mg i.v. once daily) or hydrochlorothiazide (if eGFR >50 mL/min/1.73 m2: 25 mg daily; eGFR 20–50 mL/min/1.73 m2: 50 mg daily; and eGFR <20 mL/min/ 1.73 m2: 100 mg daily). Acetazolamide might be preferable in more advanced CKD. dThe highest daily dose for i.v. loop diuretics is generally considered furosemide 600 mg, although up to 1000 mg may be considered in patients with severely impaired kidney function. eConsider MRA and K+ supplements in case of hypokalaemia. Downloaded from academic.oup.com/eurheartj/advance-article/doi/10.1093/eurheartj/ehag100/8766302 by guest on 31 August 2026