p.37 抽出テキスト
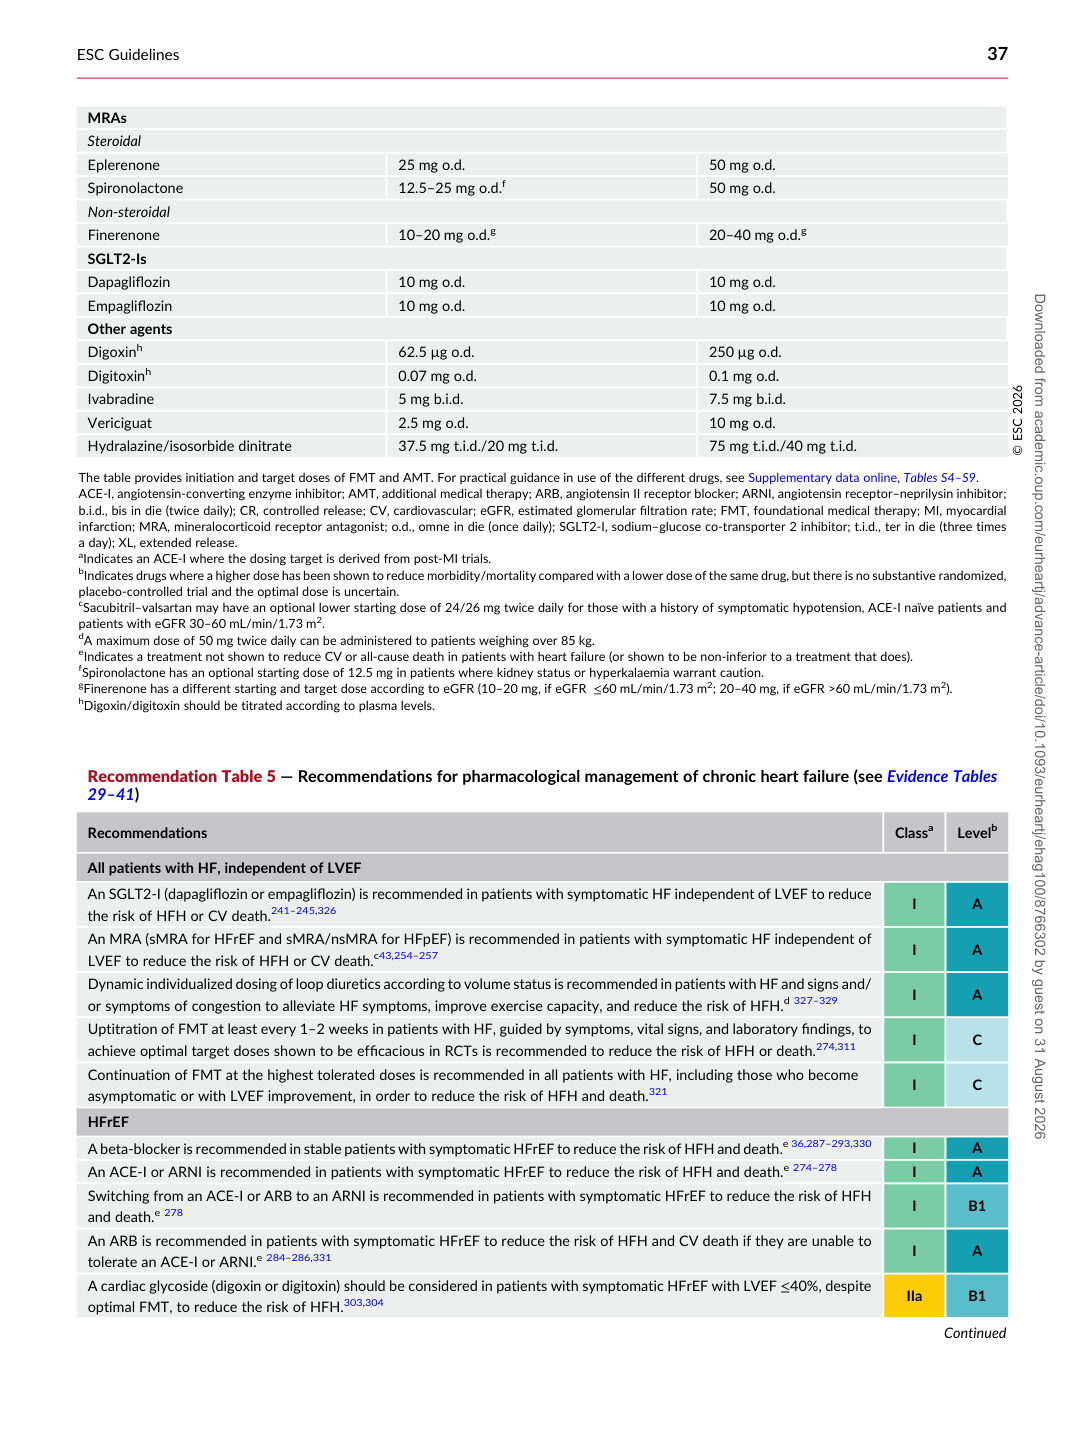
MRAs Steroidal Eplerenone 25 mg o.d. 50 mg o.d. Spironolactone 12.5–25 mg o.d.f 50 mg o.d. Non-steroidal Finerenone 10–20 mg o.d.g 20–40 mg o.d.g SGLT2-Is Dapagliflozin 10 mg o.d. 10 mg o.d. Empagliflozin 10 mg o.d. 10 mg o.d. Other agents Digoxinh 62.5 μg o.d. 250 μg o.d. Digitoxinh 0.07 mg o.d. 0.1 mg o.d. Ivabradine 5 mg b.i.d. 7.5 mg b.i.d. Vericiguat 2.5 mg o.d. 10 mg o.d. Hydralazine/isosorbide dinitrate 37.5 mg t.i.d./20 mg t.i.d. 75 mg t.i.d./40 mg t.i.d. © ESC 2026 The table provides initiation and target doses of FMT and AMT. For practical guidance in use of the different drugs, see Supplementary data online, Tables S4–S9. ACE-I, angiotensin-converting enzyme inhibitor; AMT, additional medical therapy; ARB, angiotensin II receptor blocker; ARNI, angiotensin receptor–neprilysin inhibitor; b.i.d., bis in die (twice daily); CR, controlled release; CV, cardiovascular; eGFR, estimated glomerular filtration rate; FMT, foundational medical therapy; MI, myocardial infarction; MRA, mineralocorticoid receptor antagonist; o.d., omne in die (once daily); SGLT2-I, sodium–glucose co-transporter 2 inhibitor; t.i.d., ter in die (three times a day); XL, extended release. aIndicates an ACE-I where the dosing target is derived from post-MI trials. bIndicates drugs where a higher dose has been shown to reduce morbidity/mortality compared with a lower dose of the same drug, but there is no substantive randomized, placebo-controlled trial and the optimal dose is uncertain. cSacubitril–valsartan may have an optional lower starting dose of 24/26 mg twice daily for those with a history of symptomatic hypotension, ACE-I naïve patients and patients with eGFR 30–60 mL/min/1.73 m2. dA maximum dose of 50 mg twice daily can be administered to patients weighing over 85 kg. eIndicates a treatment not shown to reduce CV or all-cause death in patients with heart failure (or shown to be non-inferior to a treatment that does). fSpironolactone has an optional starting dose of 12.5 mg in patients where kidney status or hyperkalaemia warrant caution. gFinerenone has a different starting and target dose according to eGFR (10–20 mg, if eGFR  ≤60 mL/min/1.73 m2; 20–40 mg, if eGFR >60 mL/min/1.73 m2). hDigoxin/digitoxin should be titrated according to plasma levels.

Recommendation Table 5 — Recommendations for pharmacological management of chronic heart failure (see Evidence Tables 29–41)

Recommendations Classa Levelb

All patients with HF, independent of LVEF An SGLT2-I (dapagliflozin or empagliflozin) is recommended in patients with symptomatic HF independent of LVEF to reduce the risk of HFH or CV death.241–245,326 I A An MRA (sMRA for HFrEF and sMRA/nsMRA for HFpEF) is recommended in patients with symptomatic HF independent of LVEF to reduce the risk of HFH or CV death.c43,254–257 I A Dynamic individualized dosing of loop diuretics according to volume status is recommended in patients with HF and signs and/ or symptoms of congestion to alleviate HF symptoms, improve exercise capacity, and reduce the risk of HFH.d 327–329 I A Uptitration of FMT at least every 1–2 weeks in patients with HF, guided by symptoms, vital signs, and laboratory findings, to achieve optimal target doses shown to be efficacious in RCTs is recommended to reduce the risk of HFH or death.274,311 I C Continuation of FMT at the highest tolerated doses is recommended in all patients with HF, including those who become asymptomatic or with LVEF improvement, in order to reduce the risk of HFH and death.321 I C HFrEF A beta-blocker is recommended in stable patients with symptomatic HFrEF to reduce the risk of HFH and death.e 36,287–293,330 I A An ACE-I or ARNI is recommended in patients with symptomatic HFrEF to reduce the risk of HFH and death.e 274–278 I A Switching from an ACE-I or ARB to an ARNI is recommended in patients with symptomatic HFrEF to reduce the risk of HFH and death.e 278 I B1 An ARB is recommended in patients with symptomatic HFrEF to reduce the risk of HFH and CV death if they are unable to tolerate an ACE-I or ARNI.e 284–286,331 I A A cardiac glycoside (digoxin or digitoxin) should be considered in patients with symptomatic HFrEF with LVEF ≤40%, despite optimal FMT, to reduce the risk of HFH.303,304 IIa B1

Continued Downloaded from academic.oup.com/eurheartj/advance-article/doi/10.1093/eurheartj/ehag100/8766302 by guest on 31 August 2026