p.13 抽出テキスト
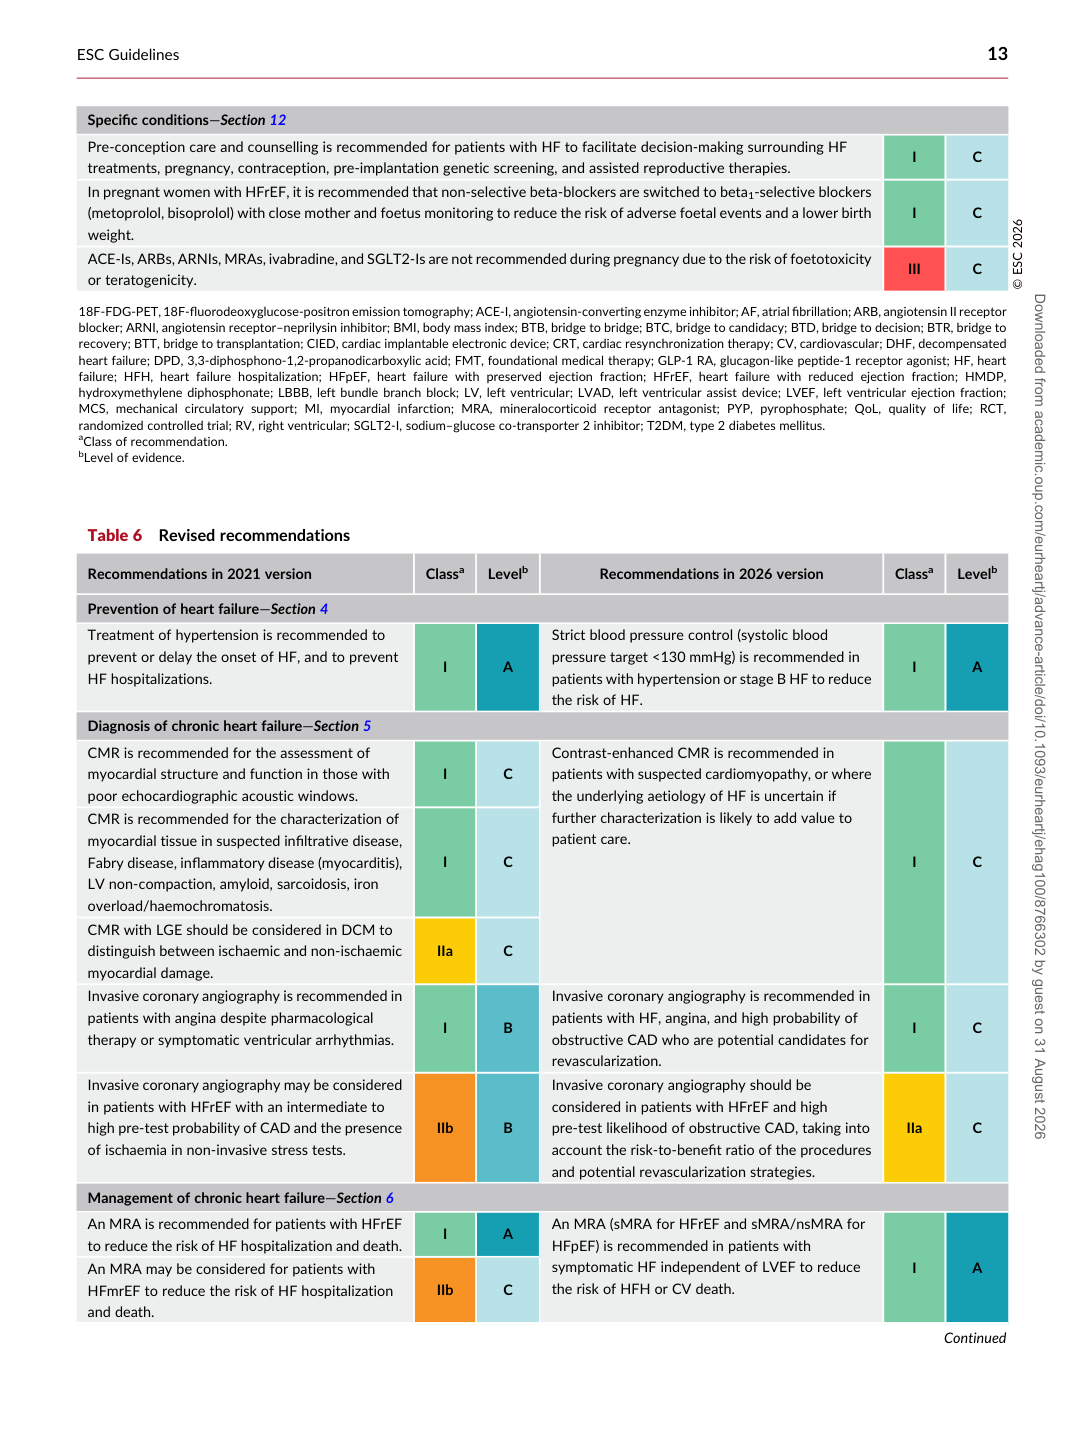
Specific conditions—Section 12 Pre-conception care and counselling is recommended for patients with HF to facilitate decision-making surrounding HF treatments, pregnancy, contraception, pre-implantation genetic screening, and assisted reproductive therapies. I C In pregnant women with HFrEF, it is recommended that non-selective beta-blockers are switched to beta1-selective blockers (metoprolol, bisoprolol) with close mother and foetus monitoring to reduce the risk of adverse foetal events and a lower birth weight. I C ACE-Is, ARBs, ARNIs, MRAs, ivabradine, and SGLT2-Is are not recommended during pregnancy due to the risk of foetotoxicity or teratogenicity. III C © ESC 2026 18F-FDG-PET, 18F-fluorodeoxyglucose-positron emission tomography; ACE-I, angiotensin-converting enzyme inhibitor; AF, atrial fibrillation; ARB, angiotensin II receptor blocker; ARNI, angiotensin receptor–neprilysin inhibitor; BMI, body mass index; BTB, bridge to bridge; BTC, bridge to candidacy; BTD, bridge to decision; BTR, bridge to recovery; BTT, bridge to transplantation; CIED, cardiac implantable electronic device; CRT, cardiac resynchronization therapy; CV, cardiovascular; DHF, decompensated heart failure; DPD, 3,3-diphosphono-1,2-propanodicarboxylic acid; FMT, foundational medical therapy; GLP-1 RA, glucagon-like peptide-1 receptor agonist; HF, heart failure; HFH, heart failure hospitalization; HFpEF, heart failure with preserved ejection fraction; HFrEF, heart failure with reduced ejection fraction; HMDP, hydroxymethylene diphosphonate; LBBB, left bundle branch block; LV, left ventricular; LVAD, left ventricular assist device; LVEF, left ventricular ejection fraction; MCS, mechanical circulatory support; MI, myocardial infarction; MRA, mineralocorticoid receptor antagonist; PYP, pyrophosphate; QoL, quality of life; RCT, randomized controlled trial; RV, right ventricular; SGLT2-I, sodium–glucose co-transporter 2 inhibitor; T2DM, type 2 diabetes mellitus. aClass of recommendation. bLevel of evidence.

Table 6 Revised recommendations

Recommendations in 2021 version Classa Levelb Recommendations in 2026 version Classa Levelb

Prevention of heart failure—Section 4 Treatment of hypertension is recommended to prevent or delay the onset of HF, and to prevent HF hospitalizations. I A Strict blood pressure control (systolic blood

pressure target <130 mmHg) is recommended in patients with hypertension or stage B HF to reduce the risk of HF. I A

Diagnosis of chronic heart failure—Section 5 CMR is recommended for the assessment of myocardial structure and function in those with poor echocardiographic acoustic windows. I C Contrast-enhanced CMR is recommended in patients with suspected cardiomyopathy, or where

the underlying aetiology of HF is uncertain if further characterization is likely to add value to patient care.

I C

CMR is recommended for the characterization of myocardial tissue in suspected infiltrative disease, Fabry disease, inflammatory disease (myocarditis), LV non-compaction, amyloid, sarcoidosis, iron overload/haemochromatosis. I C CMR with LGE should be considered in DCM to distinguish between ischaemic and non-ischaemic myocardial damage. IIa C Invasive coronary angiography is recommended in patients with angina despite pharmacological therapy or symptomatic ventricular arrhythmias. I B Invasive coronary angiography is recommended in

patients with HF, angina, and high probability of obstructive CAD who are potential candidates for revascularization. I C

Invasive coronary angiography may be considered in patients with HFrEF with an intermediate to high pre-test probability of CAD and the presence of ischaemia in non-invasive stress tests. IIb B Invasive coronary angiography should be

considered in patients with HFrEF and high pre-test likelihood of obstructive CAD, taking into account the risk-to-benefit ratio of the procedures and potential revascularization strategies. IIa C

Management of chronic heart failure—Section 6 An MRA is recommended for patients with HFrEF

to reduce the risk of HF hospitalization and death. I A An MRA (sMRA for HFrEF and sMRA/nsMRA for

HFpEF) is recommended in patients with symptomatic HF independent of LVEF to reduce the risk of HFH or CV death.

I A An MRA may be considered for patients with HFmrEF to reduce the risk of HF hospitalization and death. IIb C

Continued Downloaded from academic.oup.com/eurheartj/advance-article/doi/10.1093/eurheartj/ehag100/8766302 by guest on 31 August 2026