p.75 抽出テキスト
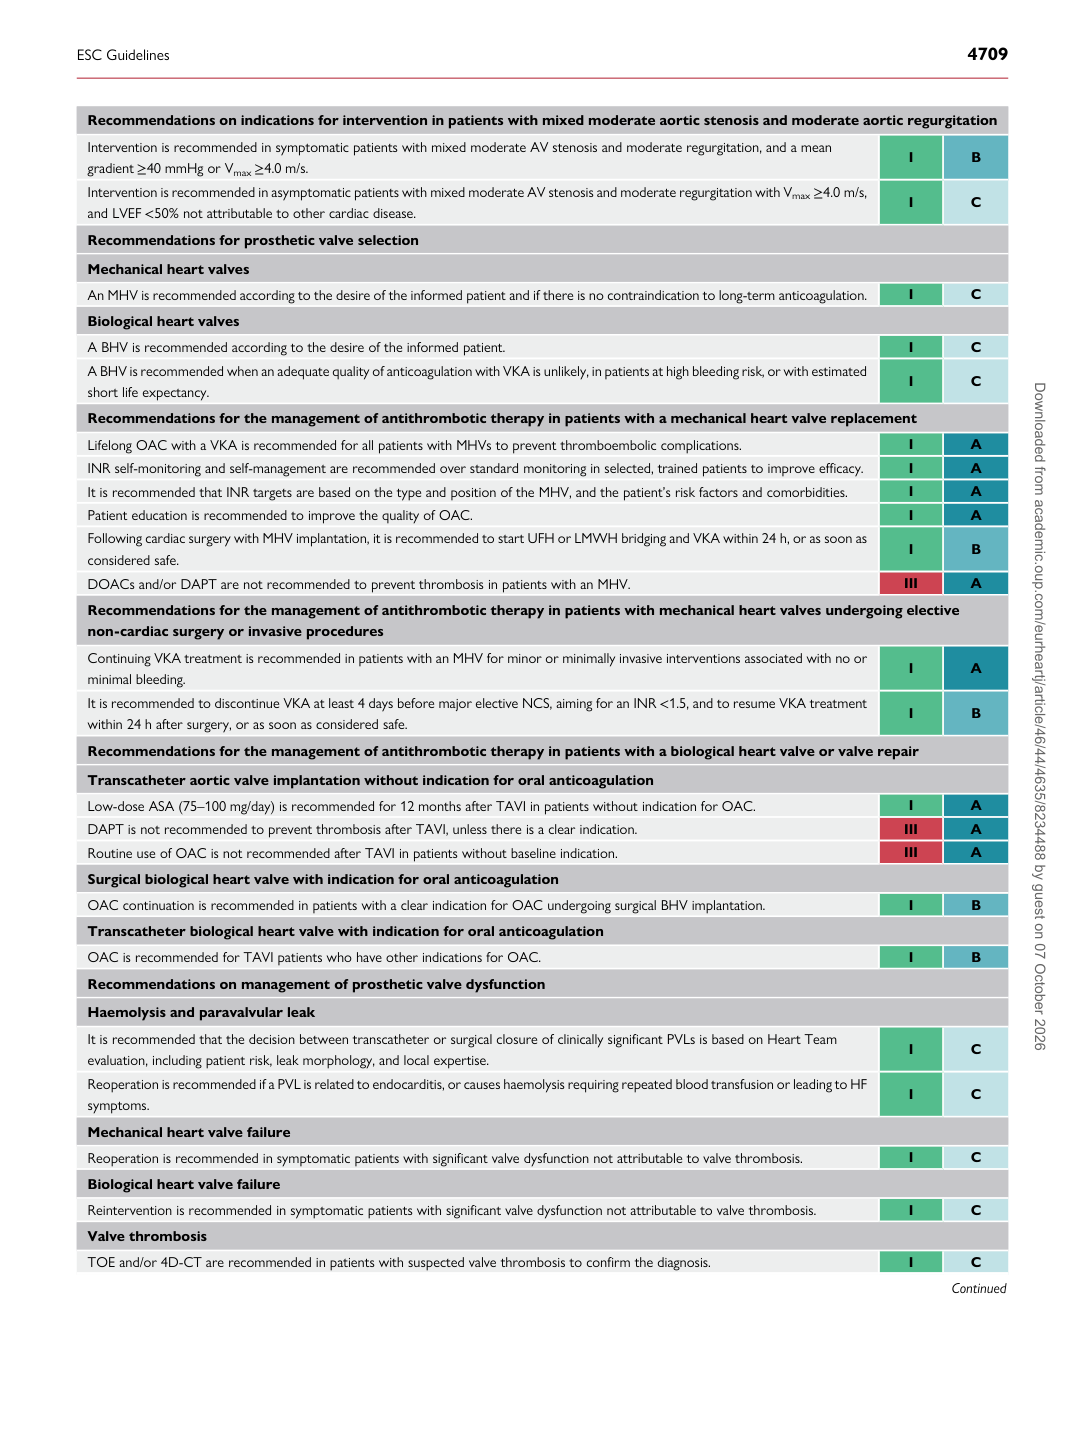
Recommendations on indications for intervention in patients with mixed moderate aortic stenosis and moderate aortic regurgitation Intervention is recommended in symptomatic patients with mixed moderate AV stenosis and moderate regurgitation, and a mean gradient ≥40 mmHg or Vmax ≥4.0 m/s. I B Intervention is recommended in asymptomatic patients with mixed moderate AV stenosis and moderate regurgitation with Vmax ≥4.0 m/s, and LVEF <50% not attributable to other cardiac disease. I C Recommendations for prosthetic valve selection Mechanical heart valves An MHV is recommended according to the desire of the informed patient and if there is no contraindication to long-term anticoagulation. I C Biological heart valves A BHV is recommended according to the desire of the informed patient. I C A BHV is recommended when an adequate quality of anticoagulation with VKA is unlikely, in patients at high bleeding risk, or with estimated short life expectancy. I C Recommendations for the management of antithrombotic therapy in patients with a mechanical heart valve replacement Lifelong OAC with a VKA is recommended for all patients with MHVs to prevent thromboembolic complications. I A INR self-monitoring and self-management are recommended over standard monitoring in selected, trained patients to improve efficacy. I A It is recommended that INR targets are based on the type and position of the MHV, and the patient’s risk factors and comorbidities. I A Patient education is recommended to improve the quality of OAC. I A Following cardiac surgery with MHV implantation, it is recommended to start UFH or LMWH bridging and VKA within 24 h, or as soon as considered safe. I B DOACs and/or DAPT are not recommended to prevent thrombosis in patients with an MHV. III A Recommendations for the management of antithrombotic therapy in patients with mechanical heart valves undergoing elective non-cardiac surgery or invasive procedures Continuing VKA treatment is recommended in patients with an MHV for minor or minimally invasive interventions associated with no or minimal bleeding. I A It is recommended to discontinue VKA at least 4 days before major elective NCS, aiming for an INR <1.5, and to resume VKA treatment within 24 h after surgery, or as soon as considered safe. I B Recommendations for the management of antithrombotic therapy in patients with a biological heart valve or valve repair Transcatheter aortic valve implantation without indication for oral anticoagulation Low-dose ASA (75–100 mg/day) is recommended for 12 months after TAVI in patients without indication for OAC. I A DAPT is not recommended to prevent thrombosis after TAVI, unless there is a clear indication. III A Routine use of OAC is not recommended after TAVI in patients without baseline indication. III A Surgical biological heart valve with indication for oral anticoagulation OAC continuation is recommended in patients with a clear indication for OAC undergoing surgical BHV implantation. I B Transcatheter biological heart valve with indication for oral anticoagulation OAC is recommended for TAVI patients who have other indications for OAC. I B Recommendations on management of prosthetic valve dysfunction Haemolysis and paravalvular leak It is recommended that the decision between transcatheter or surgical closure of clinically significant PVLs is based on Heart Team evaluation, including patient risk, leak morphology, and local expertise. I C Reoperation is recommended if a PVL is related to endocarditis, or causes haemolysis requiring repeated blood transfusion or leading to HF symptoms. I C Mechanical heart valve failure Reoperation is recommended in symptomatic patients with significant valve dysfunction not attributable to valve thrombosis. I C Biological heart valve failure Reintervention is recommended in symptomatic patients with significant valve dysfunction not attributable to valve thrombosis. I C Valve thrombosis TOE and/or 4D-CT are recommended in patients with suspected valve thrombosis to confirm the diagnosis. I C

Continued

ESC Guidelines                                                                                                                                                                                          4709

Downloaded from academic.oup.com/eurheartj/article/46/44/4635/8234488 by guest on 07 October 2026