p.74 抽出テキスト
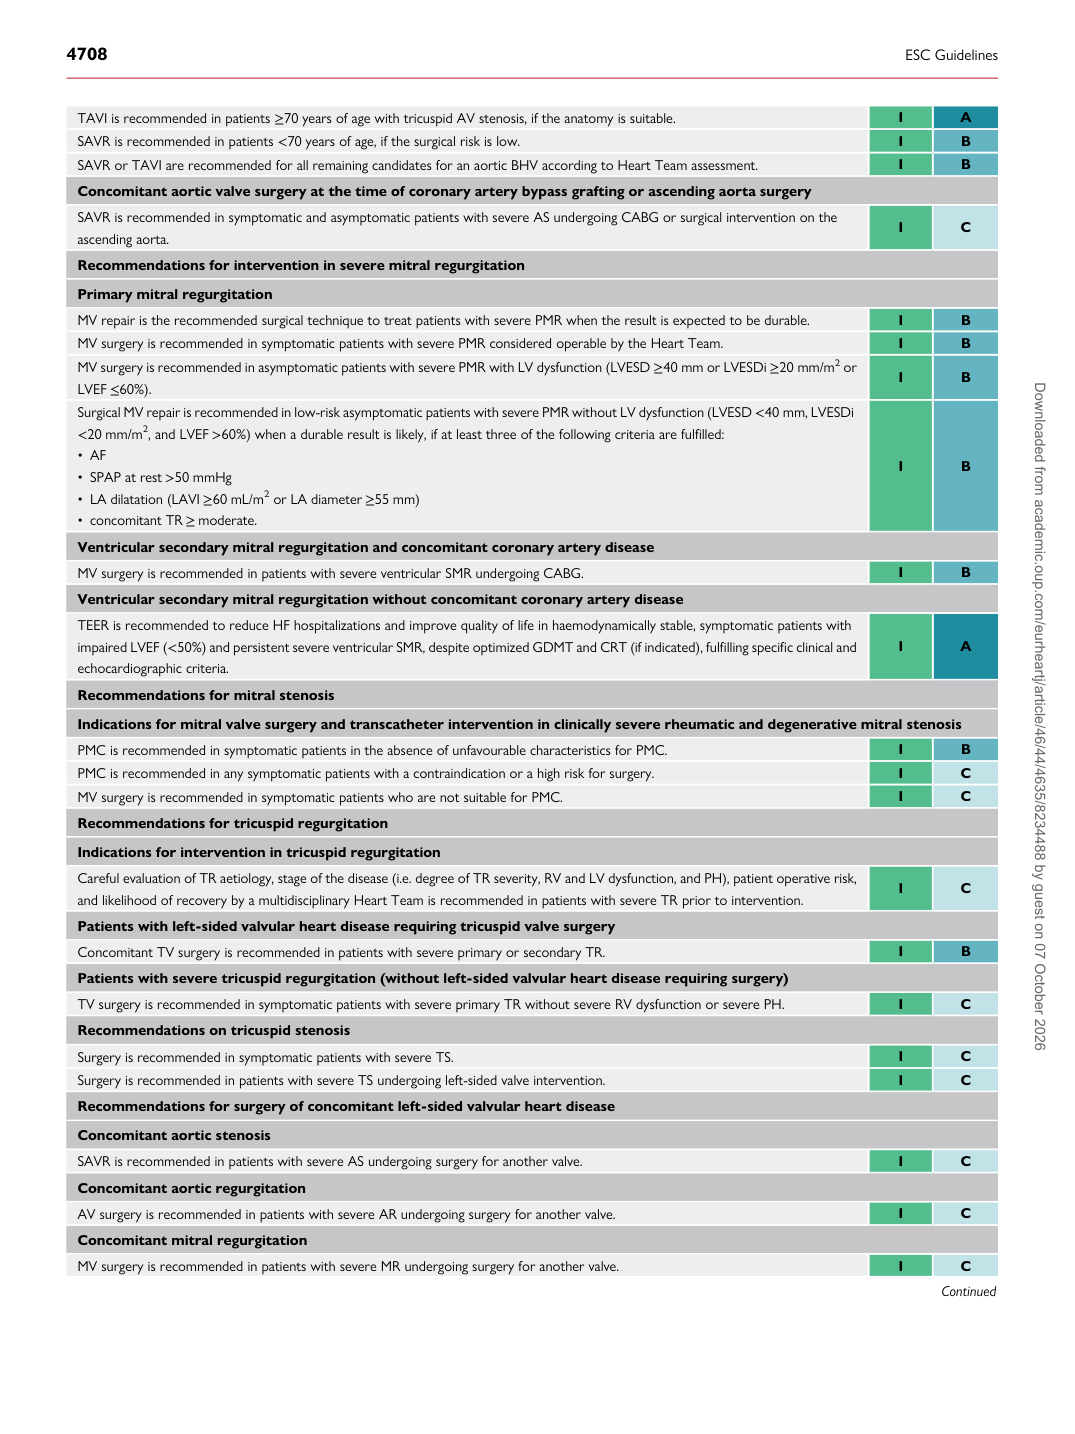
TAVI is recommended in patients ≥70 years of age with tricuspid AV stenosis, if the anatomy is suitable. I A SAVR is recommended in patients <70 years of age, if the surgical risk is low. I B SAVR or TAVI are recommended for all remaining candidates for an aortic BHV according to Heart Team assessment. I B Concomitant aortic valve surgery at the time of coronary artery bypass grafting or ascending aorta surgery SAVR is recommended in symptomatic and asymptomatic patients with severe AS undergoing CABG or surgical intervention on the ascending aorta. I C Recommendations for intervention in severe mitral regurgitation Primary mitral regurgitation MV repair is the recommended surgical technique to treat patients with severe PMR when the result is expected to be durable. I B MV surgery is recommended in symptomatic patients with severe PMR considered operable by the Heart Team. I B MV surgery is recommended in asymptomatic patients with severe PMR with LV dysfunction (LVESD ≥40 mm or LVESDi ≥20 mm/m2 or LVEF ≤60%). I B Surgical MV repair is recommended in low-risk asymptomatic patients with severe PMR without LV dysfunction (LVESD <40 mm, LVESDi <20 mm/m2, and LVEF >60%) when a durable result is likely, if at least three of the following criteria are fulfilled: • AF • SPAP at rest >50 mmHg • LA dilatation (LAVI ≥60 mL/m2 or LA diameter ≥55 mm) • concomitant TR ≥ moderate. I B Ventricular secondary mitral regurgitation and concomitant coronary artery disease MV surgery is recommended in patients with severe ventricular SMR undergoing CABG. I B Ventricular secondary mitral regurgitation without concomitant coronary artery disease TEER is recommended to reduce HF hospitalizations and improve quality of life in haemodynamically stable, symptomatic patients with impaired LVEF (<50%) and persistent severe ventricular SMR, despite optimized GDMT and CRT (if indicated), fulfilling specific clinical and echocardiographic criteria. I A Recommendations for mitral stenosis Indications for mitral valve surgery and transcatheter intervention in clinically severe rheumatic and degenerative mitral stenosis PMC is recommended in symptomatic patients in the absence of unfavourable characteristics for PMC. I B PMC is recommended in any symptomatic patients with a contraindication or a high risk for surgery. I C MV surgery is recommended in symptomatic patients who are not suitable for PMC. I C Recommendations for tricuspid regurgitation Indications for intervention in tricuspid regurgitation Careful evaluation of TR aetiology, stage of the disease (i.e. degree of TR severity, RV and LV dysfunction, and PH), patient operative risk, and likelihood of recovery by a multidisciplinary Heart Team is recommended in patients with severe TR prior to intervention. I C Patients with left-sided valvular heart disease requiring tricuspid valve surgery Concomitant TV surgery is recommended in patients with severe primary or secondary TR. I B Patients with severe tricuspid regurgitation (without left-sided valvular heart disease requiring surgery) TV surgery is recommended in symptomatic patients with severe primary TR without severe RV dysfunction or severe PH. I C Recommendations on tricuspid stenosis Surgery is recommended in symptomatic patients with severe TS. I C Surgery is recommended in patients with severe TS undergoing left-sided valve intervention. I C Recommendations for surgery of concomitant left-sided valvular heart disease Concomitant aortic stenosis SAVR is recommended in patients with severe AS undergoing surgery for another valve. I C Concomitant aortic regurgitation AV surgery is recommended in patients with severe AR undergoing surgery for another valve. I C Concomitant mitral regurgitation MV surgery is recommended in patients with severe MR undergoing surgery for another valve. I C

Continued Downloaded from academic.oup.com/eurheartj/article/46/44/4635/8234488 by guest on 07 October 2026