p.55 抽出テキスト
Transcatheter treatment options are established for severe AS (TAVI), rheumatic MS (PMC), and primary MR and TR (TEER or transcatheter replacement) in patients with MVHD at high surgical risk, if anatomy is suitable.401,783 In the context of a transcatheter strategy, a staged approach—typically beginning with the downstream lesion (aortic, followed by mitral and tricuspid)—is generally preferred to avoid potential haemodynamic deterioration.784,785

MVHD with severe secondary regurgitation of both atrioventricular valves is usually the consequence of either HFrEF with ventricular SMR and secondary TR, or atrial dilatation leading to both atrial MR and TR

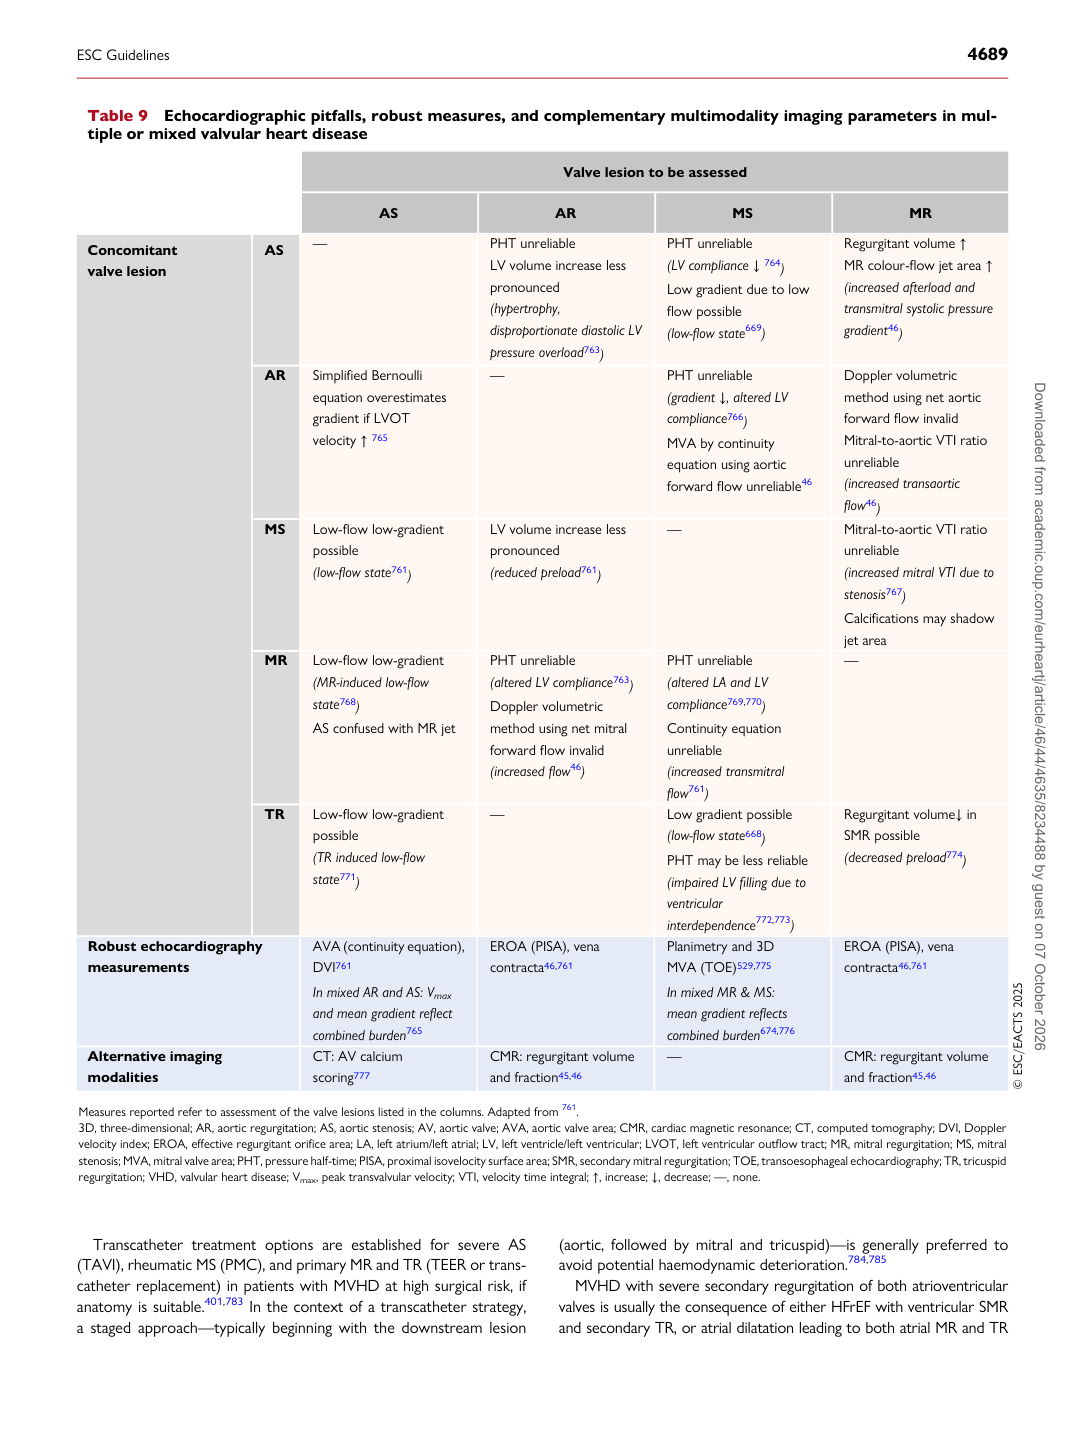
Table 9 Echocardiographic pitfalls, robust measures, and complementary multimodality imaging parameters in multiple or mixed valvular heart disease

Valve lesion to be assessed

AS AR MS MR

Concomitant valve lesion AS — PHT unreliable

LV volume increase less pronounced (hypertrophy, disproportionate diastolic LV pressure overload763) PHT unreliable

(LV compliance ↓ 764) Low gradient due to low flow possible (low-flow state669) Regurgitant volume ↑

MR colour-flow jet area ↑ (increased afterload and transmitral systolic pressure gradient46)

AR Simplified Bernoulli

equation overestimates gradient if LVOT velocity ↑ 765 — PHT unreliable

(gradient ↓, altered LV compliance766) MVA by continuity equation using aortic forward flow unreliable46 Doppler volumetric

method using net aortic forward flow invalid Mitral-to-aortic VTI ratio unreliable (increased transaortic

flow46) MS Low-flow low-gradient

possible (low-flow state761) LV volume increase less

pronounced (reduced preload761) — Mitral-to-aortic VTI ratio

unreliable (increased mitral VTI due to stenosis767) Calcifications may shadow

jet area MR Low-flow low-gradient

(MR-induced low-flow state768) AS confused with MR jet PHT unreliable

(altered LV compliance763) Doppler volumetric method using net mitral forward flow invalid (increased flow46) PHT unreliable

(altered LA and LV compliance769,770) Continuity equation unreliable (increased transmitral flow761) —

TR Low-flow low-gradient

possible (TR induced low-flow state771) — Low gradient possible

(low-flow state668) PHT may be less reliable (impaired LV filling due to ventricular interdependence772,773) Regurgitant volume↓ in

SMR possible (decreased preload774)

Robust echocardiography measurements AVA (continuity equation), DVI761

In mixed AR and AS: Vmax and mean gradient reflect combined burden765 EROA (PISA), vena contracta46,761 Planimetry and 3D MVA (TOE)529,775

In mixed MR & MS: mean gradient reflects combined burden674,776 EROA (PISA), vena contracta46,761

Alternative imaging modalities CT: AV calcium scoring777 CMR: regurgitant volume and fraction45,46 — CMR: regurgitant volume and fraction45,46 © ESC/EACTS 2025 Measures reported refer to assessment of the valve lesions listed in the columns. Adapted from 761. 3D, three-dimensional; AR, aortic regurgitation; AS, aortic stenosis; AV, aortic valve; AVA, aortic valve area; CMR, cardiac magnetic resonance; CT, computed tomography; DVI, Doppler velocity index; EROA, effective regurgitant orifice area; LA, left atrium/left atrial; LV, left ventricle/left ventricular; LVOT, left ventricular outflow tract; MR, mitral regurgitation; MS, mitral stenosis; MVA, mitral valve area; PHT, pressure half-time; PISA, proximal isovelocity surface area; SMR, secondary mitral regurgitation; TOE, transoesophageal echocardiography; TR, tricuspid regurgitation; VHD, valvular heart disease; Vmax, peak transvalvular velocity; VTI, velocity time integral; ↑, increase; ↓, decrease; —, none.

ESC Guidelines                                                                                                                                                                                          4689

Downloaded from academic.oup.com/eurheartj/article/46/44/4635/8234488 by guest on 07 October 2026