p.27 抽出テキスト
4.5.6 Transient constrictive pericarditis

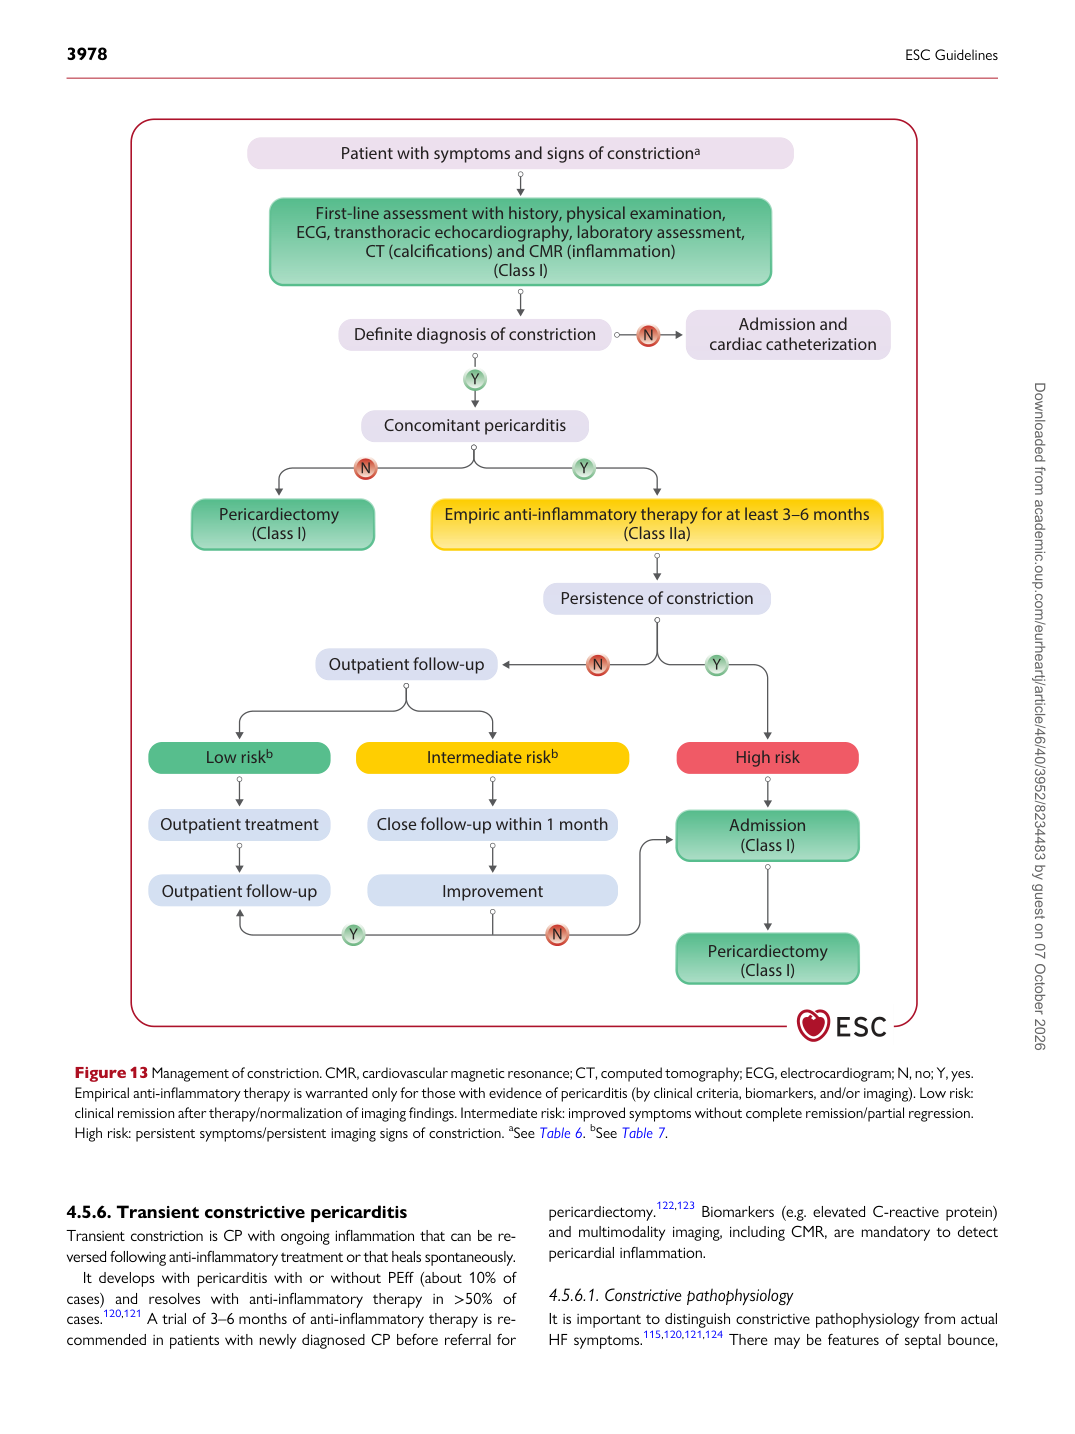
Transient constriction is CP with ongoing inflammation that can be reversed following anti-inflammatory treatment or that heals spontaneously. It develops with pericarditis with or without PEff (about 10% of cases) and resolves with anti-inflammatory therapy in >50% of cases.120,121 A trial of 3–6 months of anti-inflammatory therapy is recommended in patients with newly diagnosed CP before referral for pericardiectomy.122,123 Biomarkers (e.g. elevated C-reactive protein) and multimodality imaging, including CMR, are mandatory to detect pericardial inflammation.

4.5.6.1 Constrictive pathophysiology

It is important to distinguish constrictive pathophysiology from actual HF symptoms.115,120,121,124 There may be features of septal bounce,

Concomitant pericarditis

Pericardiectomy

(Class I)

Persistence of constriction

Outpatient follow-up

Close follow-up within 1 month

Pericardiectomy

(Class I)

Patient with symptoms and signs of constrictiona

First-line assessment with history, physical examination, ECG, transthoracic echocardiography, laboratory assessment,

CT (calcifications) and CMR (inflammation)

(Class I)

Definite diagnosis of constriction Admission and cardiac catheterization

Low riskb Intermediate riskb High risk

Outpatient treatment

Improvement Outpatient follow-up Admission

(Class I)

Empiric anti-inflammatory therapy for at least 3–6 months

(Class IIa)

Figure 13 Management of constriction. CMR, cardiovascular magnetic resonance; CT, computed tomography; ECG, electrocardiogram; N, no; Y, yes. Empirical anti-inflammatory therapy is warranted only for those with evidence of pericarditis (by clinical criteria, biomarkers, and/or imaging). Low risk: clinical remission after therapy/normalization of imaging findings. Intermediate risk: improved symptoms without complete remission/partial regression. High risk: persistent symptoms/persistent imaging signs of constriction. aSee Table 6. bSee Table 7. Downloaded from academic.oup.com/eurheartj/article/46/40/3952/8234483 by guest on 07 October 2026