p.84 抽出テキスト
BAV, and previous cardiac surgery,1188 but diabetes mellitus is more common in women than in men. In-hospital surgical mortality does not differ between sexes, although 10 year survival appears to be higher in men. Among only medically treated acute TAAD patients, prohibitive high in-hospital mortality has been equally registered for both sexes (men 58.6% vs. women 53.8%).1188 However, further studies are needed to explore AAD sex differences to design appropriate diagnostic and therapeutic interventions and preventive strategies.1189 Pregnancy increases the risk of AAS, more often in the last trimester (50%) or post-partum (33%).1190 9.3.1.1.2 Chronobiology. Acute aortic dissection presents chrono-

biological patterns, with a higher incidence in morning hours (peak between 8 am and 9 am) and winter (peak in January in the Northern Hemisphere).24,1175

9.3.1.1.3 Outcomes. For acute TAAD, in-hospital mortality has de-

creased from 31% to 22% due to better surgical outcomes; for acute type B aortic dissection (acute TBAD), in-hospital mortality has remained stable over the years (14%).1175,1182 Including deaths before admission, 30 day mortality for AAD ranges from 23% to 55.8% in Western Europe.1181

D-dimer and

chest X-Ray D-dimer Chest X-Ray POCUS

High risk: ADD-RS ≥2

AAS confirmed AAS excluded

+ + + –

Low risk: ADD-RS <2

Clinical suspicion of AAS: determine ADD-RSa

ECG: exclude STEMI (2023 ESC ACS Guidelines)

Chest X-Ray and laboratory test and POCUS (if available)

Consider alternative diagnosis

CCT neck-pelvis without delay

and/or focused TTEa + ECG

CCT

Aortic dissection detection-risk score (ADD-RS)a

High-risk examination feature High-risk pain feature High-risk condition

If one present = 1 ADD-RS point If present = 1 ADD-RS point If one present = 1 ADD-RS point

Marfan syndrome Family history of aortic disease Known aortic valve disease Recent aortic manipulation Known aortic aneurysm Haemodynamic instability (hypotension/shock) Perfusion deficit (pulse deficit, differential systolic blood pressure) Focal neurological deficit New AR murmur

Chest, back, or abdominal pain described as abrupt onset,  severe intensity, or ripping/tearing

+ –

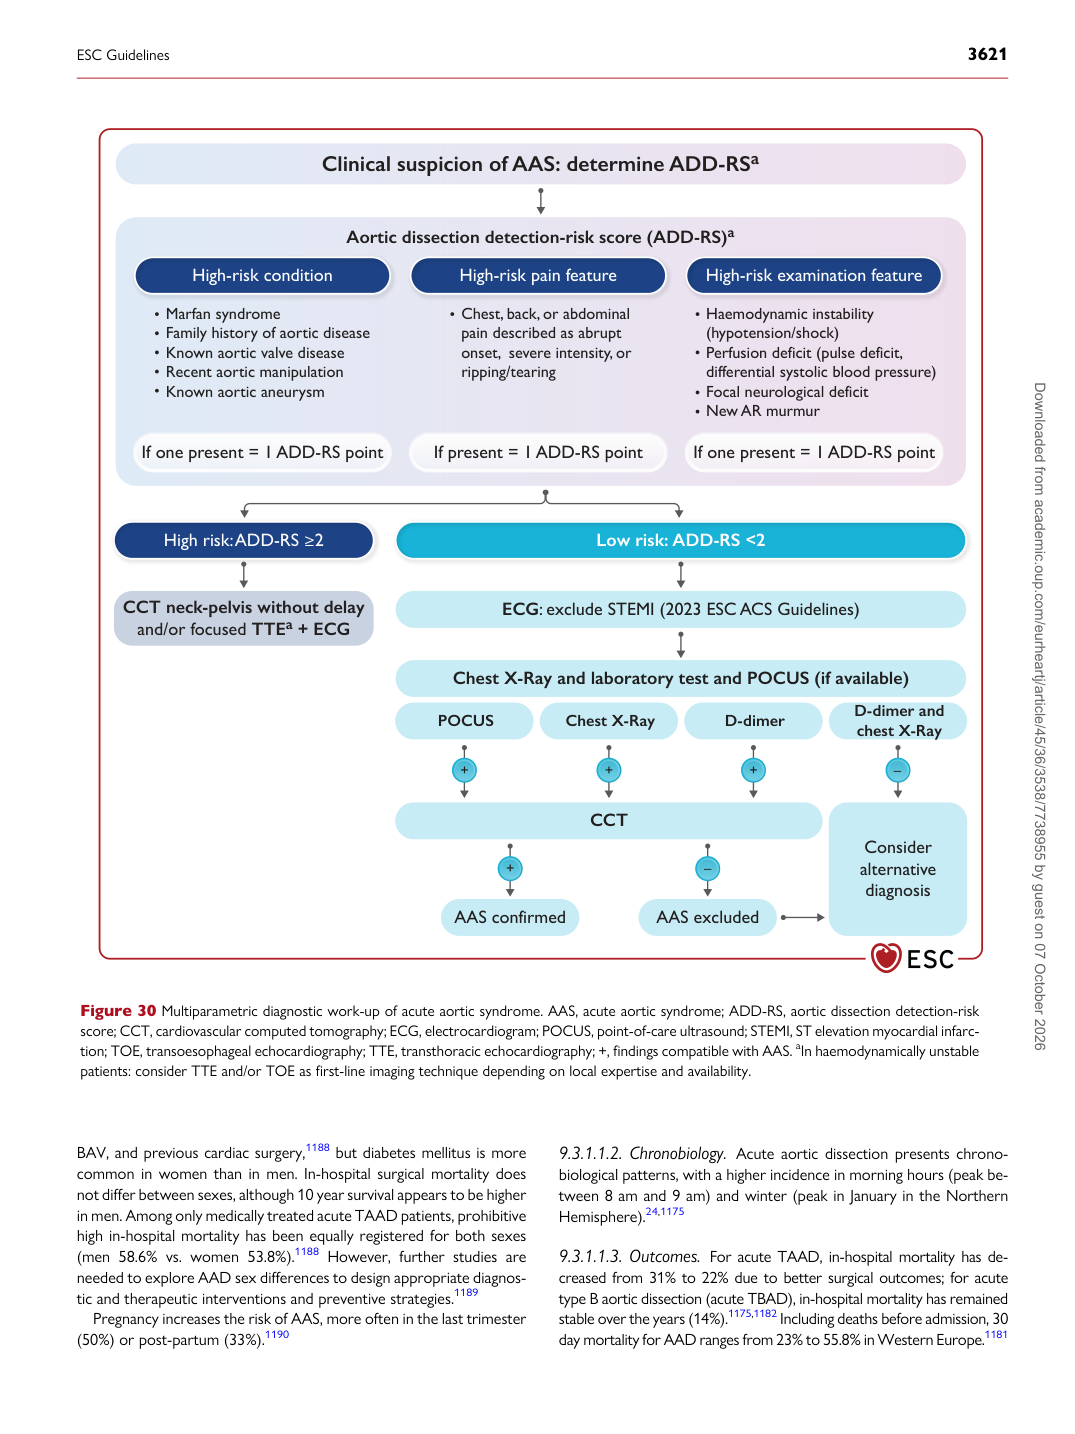
Figure 30 Multiparametric diagnostic work-up of acute aortic syndrome. AAS, acute aortic syndrome; ADD-RS, aortic dissection detection-risk score; CCT, cardiovascular computed tomography; ECG, electrocardiogram; POCUS, point-of-care ultrasound; STEMI, ST elevation myocardial infarction; TOE, transoesophageal echocardiography; TTE, transthoracic echocardiography; +, findings compatible with AAS. aIn haemodynamically unstable patients: consider TTE and/or TOE as first-line imaging technique depending on local expertise and availability.

ESC Guidelines                                                                                                                                                                                          3621

Downloaded from academic.oup.com/eurheartj/article/45/36/3538/7738955 by guest on 07 October 2026