p.17 抽出テキスト
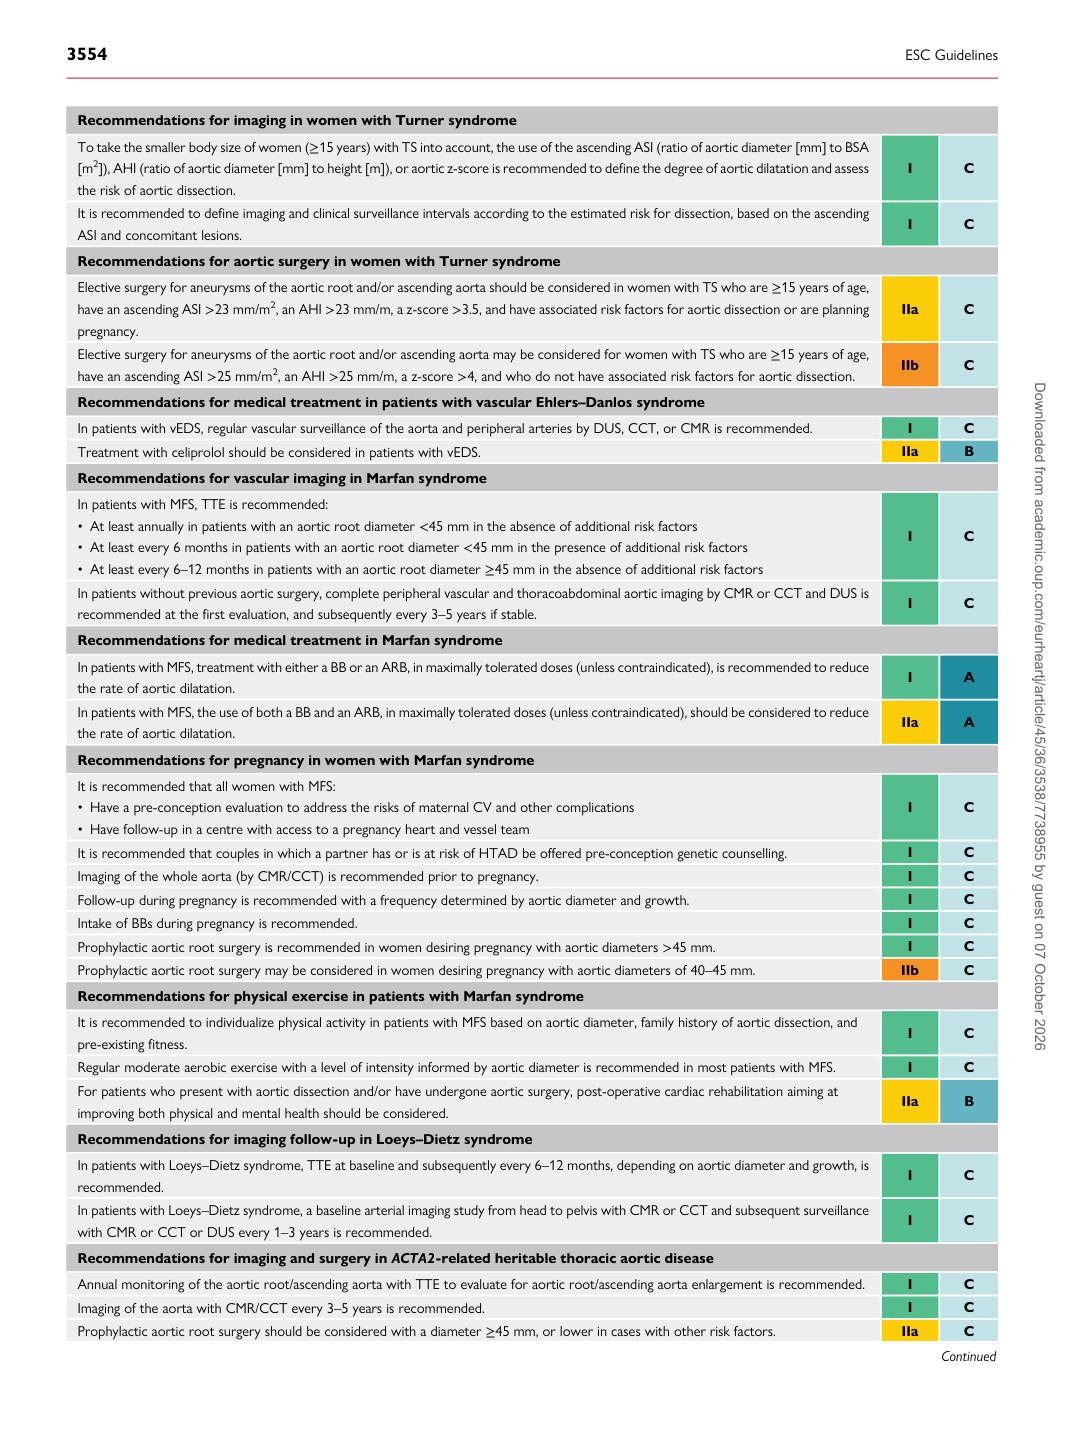
Recommendations for imaging in women with Turner syndrome To take the smaller body size of women (≥15 years) with TS into account, the use of the ascending ASI (ratio of aortic diameter [mm] to BSA [m2]), AHI (ratio of aortic diameter [mm] to height [m]), or aortic z-score is recommended to define the degree of aortic dilatation and assess the risk of aortic dissection. I C It is recommended to define imaging and clinical surveillance intervals according to the estimated risk for dissection, based on the ascending ASI and concomitant lesions. I C Recommendations for aortic surgery in women with Turner syndrome Elective surgery for aneurysms of the aortic root and/or ascending aorta should be considered in women with TS who are ≥15 years of age, have an ascending ASI >23 mm/m2, an AHI >23 mm/m, a z-score >3.5, and have associated risk factors for aortic dissection or are planning pregnancy. IIa C Elective surgery for aneurysms of the aortic root and/or ascending aorta may be considered for women with TS who are ≥15 years of age, have an ascending ASI >25 mm/m2, an AHI >25 mm/m, a z-score >4, and who do not have associated risk factors for aortic dissection. IIb C Recommendations for medical treatment in patients with vascular Ehlers–Danlos syndrome In patients with vEDS, regular vascular surveillance of the aorta and peripheral arteries by DUS, CCT, or CMR is recommended. I C Treatment with celiprolol should be considered in patients with vEDS. IIa B Recommendations for vascular imaging in Marfan syndrome In patients with MFS, TTE is recommended: • At least annually in patients with an aortic root diameter <45 mm in the absence of additional risk factors • At least every 6 months in patients with an aortic root diameter <45 mm in the presence of additional risk factors • At least every 6–12 months in patients with an aortic root diameter ≥45 mm in the absence of additional risk factors I C In patients without previous aortic surgery, complete peripheral vascular and thoracoabdominal aortic imaging by CMR or CCT and DUS is recommended at the first evaluation, and subsequently every 3–5 years if stable. I C Recommendations for medical treatment in Marfan syndrome In patients with MFS, treatment with either a BB or an ARB, in maximally tolerated doses (unless contraindicated), is recommended to reduce the rate of aortic dilatation. I A In patients with MFS, the use of both a BB and an ARB, in maximally tolerated doses (unless contraindicated), should be considered to reduce the rate of aortic dilatation. IIa A Recommendations for pregnancy in women with Marfan syndrome It is recommended that all women with MFS: • Have a pre-conception evaluation to address the risks of maternal CV and other complications • Have follow-up in a centre with access to a pregnancy heart and vessel team I C It is recommended that couples in which a partner has or is at risk of HTAD be offered pre-conception genetic counselling. I C Imaging of the whole aorta (by CMR/CCT) is recommended prior to pregnancy. I C Follow-up during pregnancy is recommended with a frequency determined by aortic diameter and growth. I C Intake of BBs during pregnancy is recommended. I C Prophylactic aortic root surgery is recommended in women desiring pregnancy with aortic diameters >45 mm. I C Prophylactic aortic root surgery may be considered in women desiring pregnancy with aortic diameters of 40–45 mm. IIb C Recommendations for physical exercise in patients with Marfan syndrome It is recommended to individualize physical activity in patients with MFS based on aortic diameter, family history of aortic dissection, and pre-existing fitness. I C Regular moderate aerobic exercise with a level of intensity informed by aortic diameter is recommended in most patients with MFS. I C For patients who present with aortic dissection and/or have undergone aortic surgery, post-operative cardiac rehabilitation aiming at improving both physical and mental health should be considered. IIa B Recommendations for imaging follow-up in Loeys–Dietz syndrome In patients with Loeys–Dietz syndrome, TTE at baseline and subsequently every 6–12 months, depending on aortic diameter and growth, is recommended. I C In patients with Loeys–Dietz syndrome, a baseline arterial imaging study from head to pelvis with CMR or CCT and subsequent surveillance with CMR or CCT or DUS every 1–3 years is recommended. I C Recommendations for imaging and surgery in ACTA2-related heritable thoracic aortic disease Annual monitoring of the aortic root/ascending aorta with TTE to evaluate for aortic root/ascending aorta enlargement is recommended. I C Imaging of the aorta with CMR/CCT every 3–5 years is recommended. I C Prophylactic aortic root surgery should be considered with a diameter ≥45 mm, or lower in cases with other risk factors. IIa C

Continued Downloaded from academic.oup.com/eurheartj/article/45/36/3538/7738955 by guest on 07 October 2026