p.122 抽出テキスト
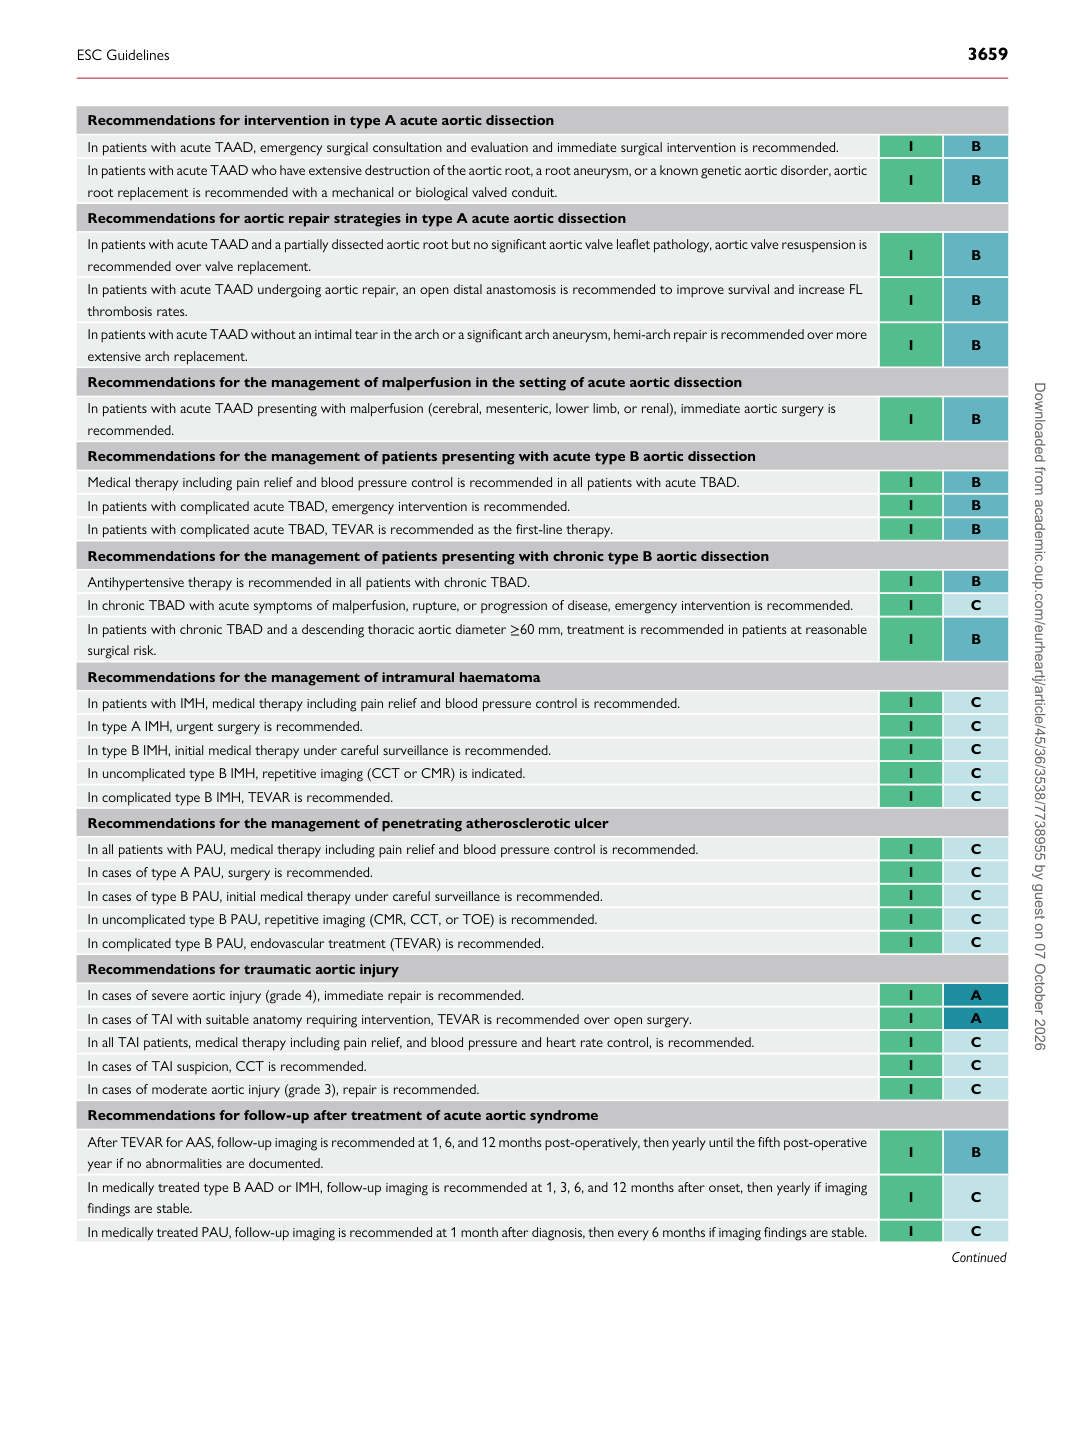
Recommendations for intervention in type A acute aortic dissection In patients with acute TAAD, emergency surgical consultation and evaluation and immediate surgical intervention is recommended. I B In patients with acute TAAD who have extensive destruction of the aortic root, a root aneurysm, or a known genetic aortic disorder, aortic root replacement is recommended with a mechanical or biological valved conduit. I B Recommendations for aortic repair strategies in type A acute aortic dissection In patients with acute TAAD and a partially dissected aortic root but no significant aortic valve leaflet pathology, aortic valve resuspension is recommended over valve replacement. I B In patients with acute TAAD undergoing aortic repair, an open distal anastomosis is recommended to improve survival and increase FL thrombosis rates. I B In patients with acute TAAD without an intimal tear in the arch or a significant arch aneurysm, hemi-arch repair is recommended over more extensive arch replacement. I B Recommendations for the management of malperfusion in the setting of acute aortic dissection In patients with acute TAAD presenting with malperfusion (cerebral, mesenteric, lower limb, or renal), immediate aortic surgery is recommended. I B Recommendations for the management of patients presenting with acute type B aortic dissection Medical therapy including pain relief and blood pressure control is recommended in all patients with acute TBAD. I B In patients with complicated acute TBAD, emergency intervention is recommended. I B In patients with complicated acute TBAD, TEVAR is recommended as the first-line therapy. I B Recommendations for the management of patients presenting with chronic type B aortic dissection Antihypertensive therapy is recommended in all patients with chronic TBAD. I B In chronic TBAD with acute symptoms of malperfusion, rupture, or progression of disease, emergency intervention is recommended. I C In patients with chronic TBAD and a descending thoracic aortic diameter ≥60 mm, treatment is recommended in patients at reasonable surgical risk. I B Recommendations for the management of intramural haematoma In patients with IMH, medical therapy including pain relief and blood pressure control is recommended. I C In type A IMH, urgent surgery is recommended. I C In type B IMH, initial medical therapy under careful surveillance is recommended. I C In uncomplicated type B IMH, repetitive imaging (CCT or CMR) is indicated. I C In complicated type B IMH, TEVAR is recommended. I C Recommendations for the management of penetrating atherosclerotic ulcer In all patients with PAU, medical therapy including pain relief and blood pressure control is recommended. I C In cases of type A PAU, surgery is recommended. I C In cases of type B PAU, initial medical therapy under careful surveillance is recommended. I C In uncomplicated type B PAU, repetitive imaging (CMR, CCT, or TOE) is recommended. I C In complicated type B PAU, endovascular treatment (TEVAR) is recommended. I C Recommendations for traumatic aortic injury In cases of severe aortic injury (grade 4), immediate repair is recommended. I A In cases of TAI with suitable anatomy requiring intervention, TEVAR is recommended over open surgery. I A In all TAI patients, medical therapy including pain relief, and blood pressure and heart rate control, is recommended. I C In cases of TAI suspicion, CCT is recommended. I C In cases of moderate aortic injury (grade 3), repair is recommended. I C Recommendations for follow-up after treatment of acute aortic syndrome After TEVAR for AAS, follow-up imaging is recommended at 1, 6, and 12 months post-operatively, then yearly until the fifth post-operative year if no abnormalities are documented. I B In medically treated type B AAD or IMH, follow-up imaging is recommended at 1, 3, 6, and 12 months after onset, then yearly if imaging findings are stable. I C In medically treated PAU, follow-up imaging is recommended at 1 month after diagnosis, then every 6 months if imaging findings are stable. I C

Continued

ESC Guidelines                                                                                                                                                                                          3659

Downloaded from academic.oup.com/eurheartj/article/45/36/3538/7738955 by guest on 07 October 2026