p.107 抽出テキスト
CCTa Surgery if risk factorsb

(Class IIa)

Aortic root/ ascending diameter (mm)

Marfan/FBN1

Loeys-Dietz/ TGF-ß genes

ACTA2/ SMC genes

TTE Follow-up Every 6–12 months Surgery (Class I)

CMR/CCT head-to-pelvis every 1–3 years

Baseline CMR/CCT

Baseline CMR/CCT

Baseline CMR/CCT

TTE yearly

TTE yearly CMR/CCT every 3–5 years

CMR/CCT every 3–5 years CCTa

CCTa

CCTa

35 mm 40 mm

42 mm 45 mm 50 mm

CCTa Surgery if risk factorsb

(Class IIb)

Every 6–12 months

TTE yearly

Surgery (Class IIa)

Surgery (Class IIa)

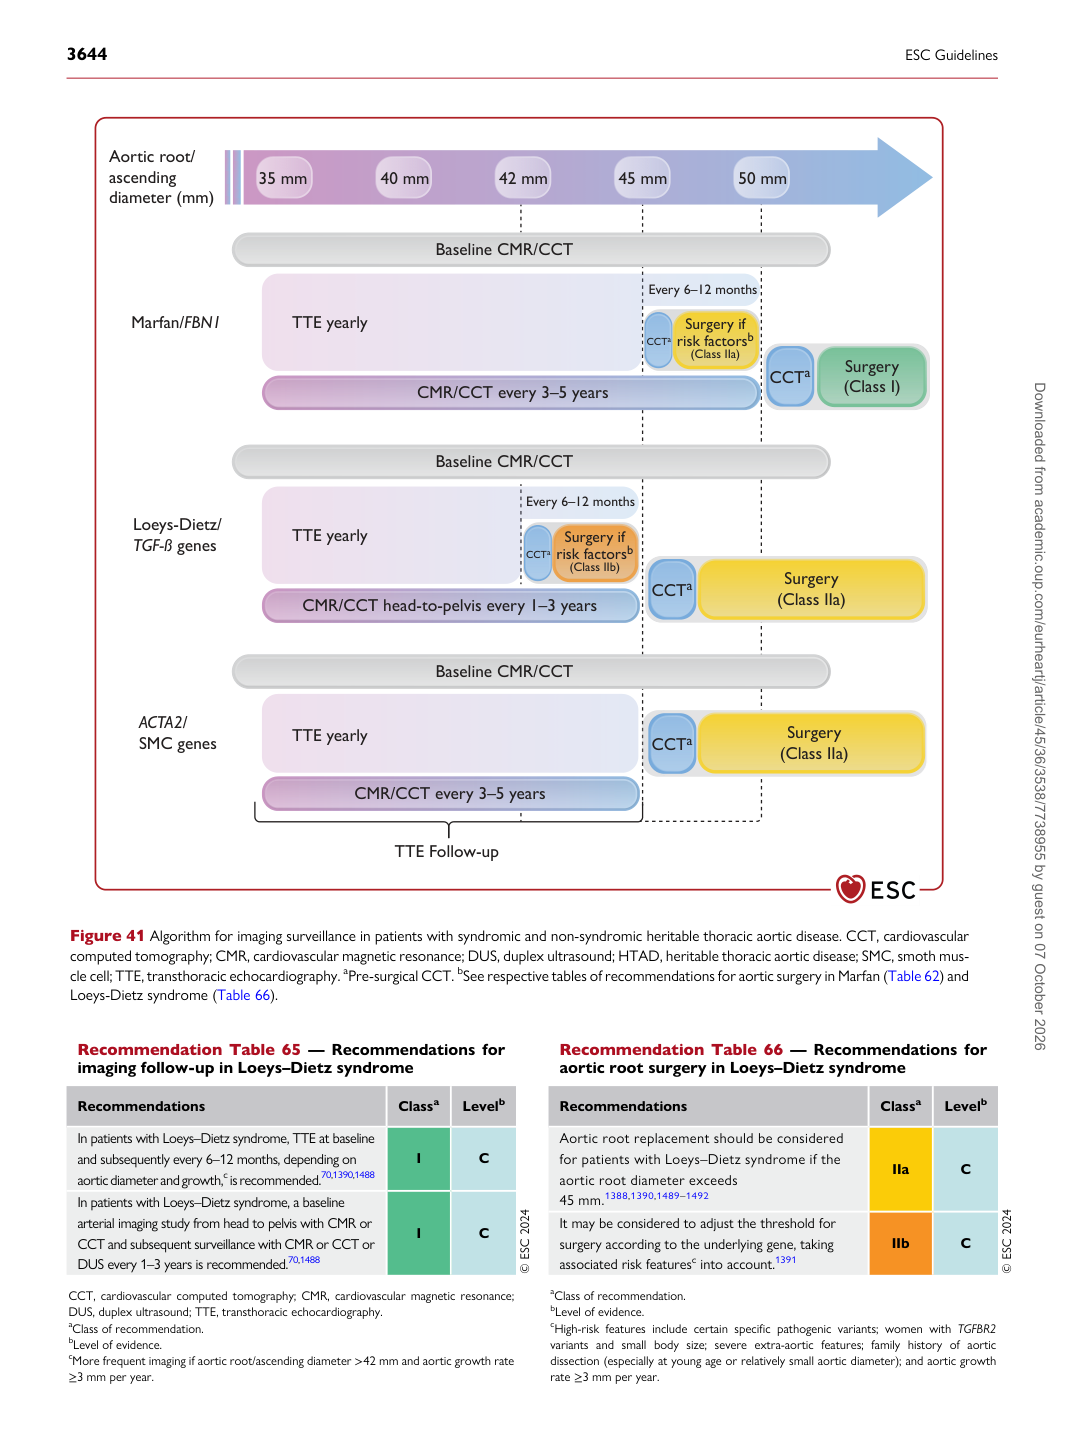
Figure 41 Algorithm for imaging surveillance in patients with syndromic and non-syndromic heritable thoracic aortic disease. CCT, cardiovascular computed tomography; CMR, cardiovascular magnetic resonance; DUS, duplex ultrasound; HTAD, heritable thoracic aortic disease; SMC, smoth muscle cell; TTE, transthoracic echocardiography. aPre-surgical CCT. bSee respective tables of recommendations for aortic surgery in Marfan (Table 62) and Loeys-Dietz syndrome (Table 66).

Recommendation Table 66 — Recommendations for aortic root surgery in Loeys–Dietz syndrome

Recommendations Classa Levelb

Aortic root replacement should be considered for patients with Loeys–Dietz syndrome if the aortic root diameter exceeds 45 mm.1388,1390,1489–1492 IIa C It may be considered to adjust the threshold for surgery according to the underlying gene, taking associated risk featuresc into account.1391 IIb C © ESC 2024 aClass of recommendation. bLevel of evidence. cHigh-risk features include certain specific pathogenic variants; women with TGFBR2 variants and small body size; severe extra-aortic features; family history of aortic dissection (especially at young age or relatively small aortic diameter); and aortic growth rate ≥3 mm per year.

Recommendation Table 65 — Recommendations for imaging follow-up in Loeys–Dietz syndrome

Recommendations Classa Levelb

In patients with Loeys–Dietz syndrome, TTE at baseline and subsequently every 6–12 months, depending on aortic diameter and growth,c is recommended.70,1390,1488 I C In patients with Loeys–Dietz syndrome, a baseline arterial imaging study from head to pelvis with CMR or CCT and subsequent surveillance with CMR or CCT or DUS every 1–3 years is recommended.70,1488 I C © ESC 2024

CCT, cardiovascular computed tomography; CMR, cardiovascular magnetic resonance; DUS, duplex ultrasound; TTE, transthoracic echocardiography. aClass of recommendation. bLevel of evidence. cMore frequent imaging if aortic root/ascending diameter >42 mm and aortic growth rate ≥3 mm per year. Downloaded from academic.oup.com/eurheartj/article/45/36/3538/7738955 by guest on 07 October 2026