p.59 抽出テキスト
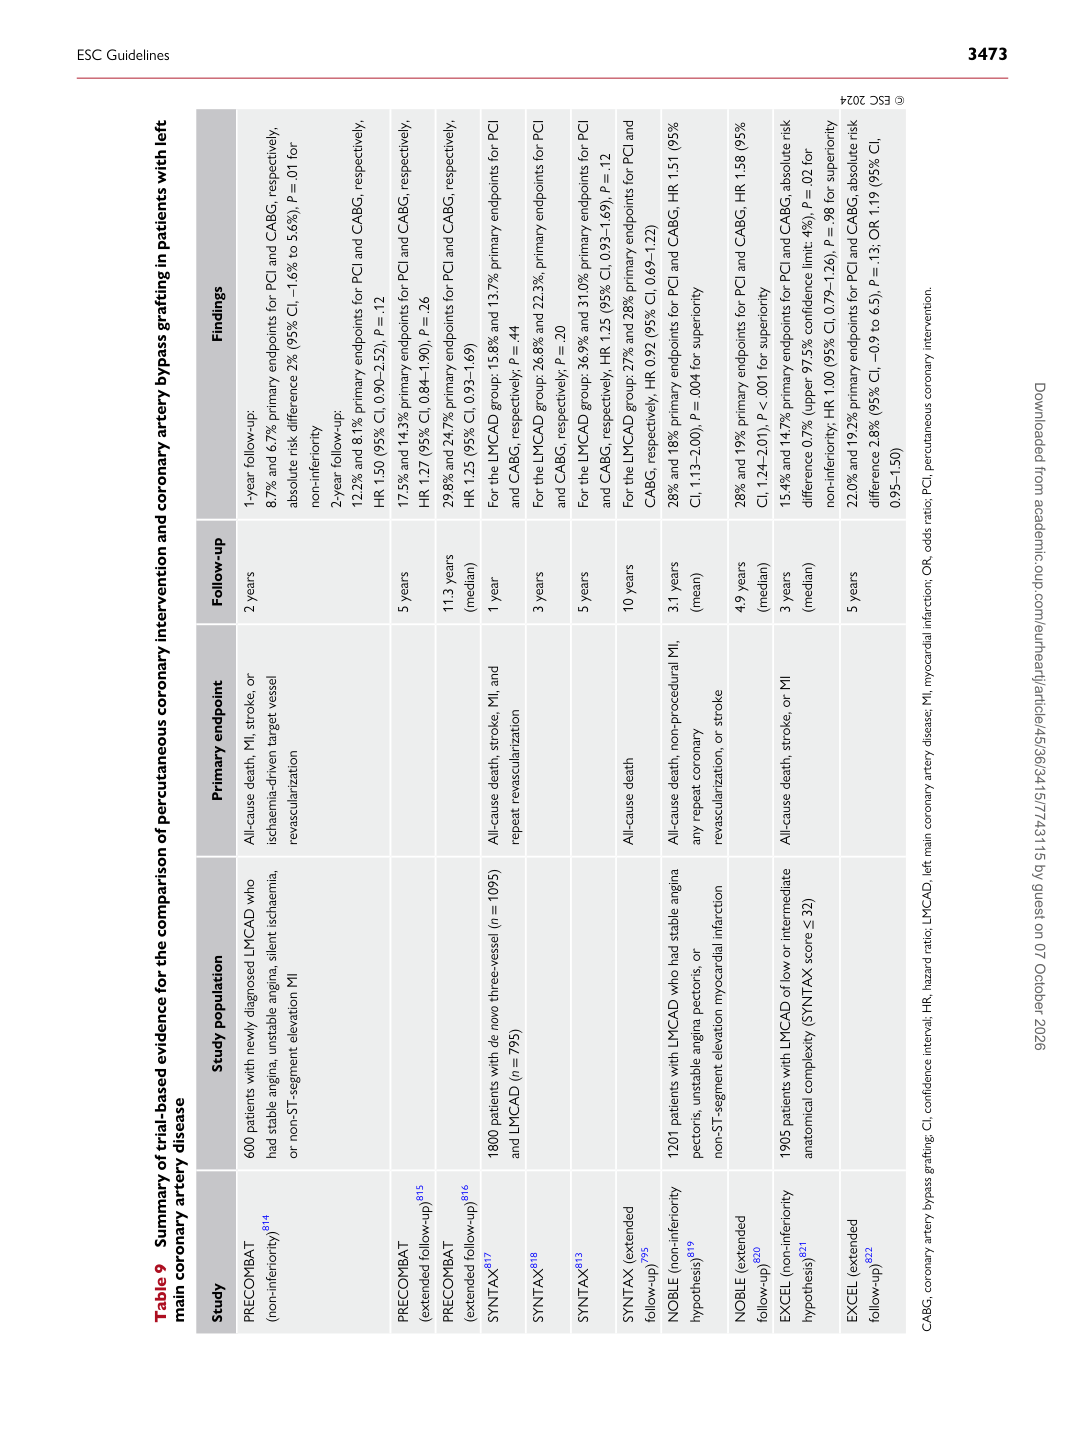
Table 9 Summary of trial-based evidence for the comparison of percutaneous coronary intervention and coronary artery bypass grafting in patients with left main coronary artery disease Study Study population Primary endpoint Follow-up Findings PRECOMBAT

(non-inferiority)814 600 patients with newly diagnosed LMCAD who

had stable angina, unstable angina, silent ischaemia, or non-ST-segment elevation MI

All-cause death, MI, stroke, or ischaemia-driven target vessel revascularization

2 years 1-year follow-up: 8.7% and 6.7% primary endpoints for PCI and CABG, respectively, absolute risk difference 2% (95% CI, –1.6% to 5.6%), P = .01 for non-inferiority 2-year follow-up: 12.2% and 8.1% primary endpoints for PCI and CABG, respectively, HR 1.50 (95% CI, 0.90–2.52), P = .12

PRECOMBAT

(extended follow-up)815 5 years 17.5% and 14.3% primary endpoints for PCI and CABG, respectively, HR 1.27 (95% CI, 0.84–1.90), P = .26 PRECOMBAT

(extended follow-up)816 11.3 years

(median)

29.8% and 24.7% primary endpoints for PCI and CABG, respectively, HR 1.25 (95% CI, 0.93–1.69)

SYNTAX817 1800 patients with de novo three-vessel (n = 1095) and LMCAD (n = 795)

All-cause death, stroke, MI, and repeat revascularization

1 year For the LMCAD group: 15.8% and 13.7% primary endpoints for PCI and CABG, respectively; P = .44 SYNTAX818 3 years For the LMCAD group: 26.8% and 22.3%, primary endpoints for PCI and CABG, respectively; P = .20 SYNTAX813 5 years For the LMCAD group: 36.9% and 31.0% primary endpoints for PCI and CABG, respectively, HR 1.25 (95% CI, 0.93–1.69), P = .12 SYNTAX (extended

follow-up)795 All-cause death 10 years For the LMCAD group: 27% and 28% primary endpoints for PCI and

CABG, respectively, HR 0.92 (95% CI, 0.69–1.22)

NOBLE (non-inferiority

hypothesis)819 1201 patients with LMCAD who had stable angina

pectoris, unstable angina pectoris, or non-ST-segment elevation myocardial infarction

All-cause death, non-procedural MI, any repeat coronary revascularization, or stroke

3.1 years (mean)

28% and 18% primary endpoints for PCI and CABG, HR 1.51 (95% CI, 1.13–2.00), P = .004 for superiority

NOBLE (extended

follow-up)820 4.9 years

(median)

28% and 19% primary endpoints for PCI and CABG, HR 1.58 (95% CI, 1.24–2.01), P < .001 for superiority

EXCEL (non-inferiority

hypothesis)821 1905 patients with LMCAD of low or intermediate

anatomical complexity (SYNTAX score ≤ 32)

All-cause death, stroke, or MI 3 years (median)

15.4% and 14.7% primary endpoints for PCI and CABG, absolute risk difference 0.7% (upper 97.5% confidence limit: 4%), P = .02 for non-inferiority; HR 1.00 (95% CI, 0.79–1.26), P = .98 for superiority

EXCEL (extended

follow-up)822 5 years 22.0% and 19.2% primary endpoints for PCI and CABG, absolute risk difference 2.8% (95% CI, −0.9 to 6.5), P = .13; OR 1.19 (95% CI, 0.95–1.50) CABG, coronary artery bypass grafting; CI, confidence interval; HR, hazard ratio; LMCAD, left main coronary artery disease; MI, myocardial infarction; OR, odds ratio; PCI, percutaneous coronary intervention.

ESC Guidelines                                                                                                                                                                                          3473

Downloaded from academic.oup.com/eurheartj/article/45/36/3415/7743115 by guest on 07 October 2026