p.49 抽出テキスト
4.3.1.1.5 Genotype- and phenotype-guided dual antiplatelet

therapy. There is high laboratory interindividual variability in patients treated with clopidogrel, with patients who carry a cytochrome P450 2C19 (CYP2C19) loss-of-function allele having less platelet inhibition and a higher risk of ischaemic events post-PCI compared with non-carriers.599,600 In ST-segment elevation myocardial infarction (STEMI) patients, early de-escalation from aspirin plus ticagrelor or aspirin plus prasugrel to aspirin plus clopidogrel based on genotyping or platelet function testing was non-inferior for net adverse clinical events (ischaemic endpoints and bleeding combined) compared with routine

Patients with CCS without indication for OAC undergoing PCI

Assess bleeding risk

Non-high bleeding risk High bleeding risk

Default Non-high ischaemic risk High ischaemic risk Default

1 month

3 months

6 months

Long term A

A C

C A C A C

A R A

A P

A C

T

T P

A C

6 mo. DAPT (Class I) A C 1–3 mo. DAPT (Class I)

(Class I) 1–3 mo. DAPT (Class IIb)

OR A C

(Class I)

OR A C

(Class I)

OR OR

OR OR

1–6 mo. DAPTa

(Class IIb)

(Class IIa)

R (Class IIb)

Aspirin 100 mg o.d. T

Clopidogrel 75 mg o.d.

Ticagrelor 90 mg b.i.d. Prasugrel 10 mg o.d.b

Rivaroxaban 2.5 mg b.i.d.

T Ticagrelor 60 mg b.i.d.

A T

A P

OR

6 mo. DAPT (Class I)

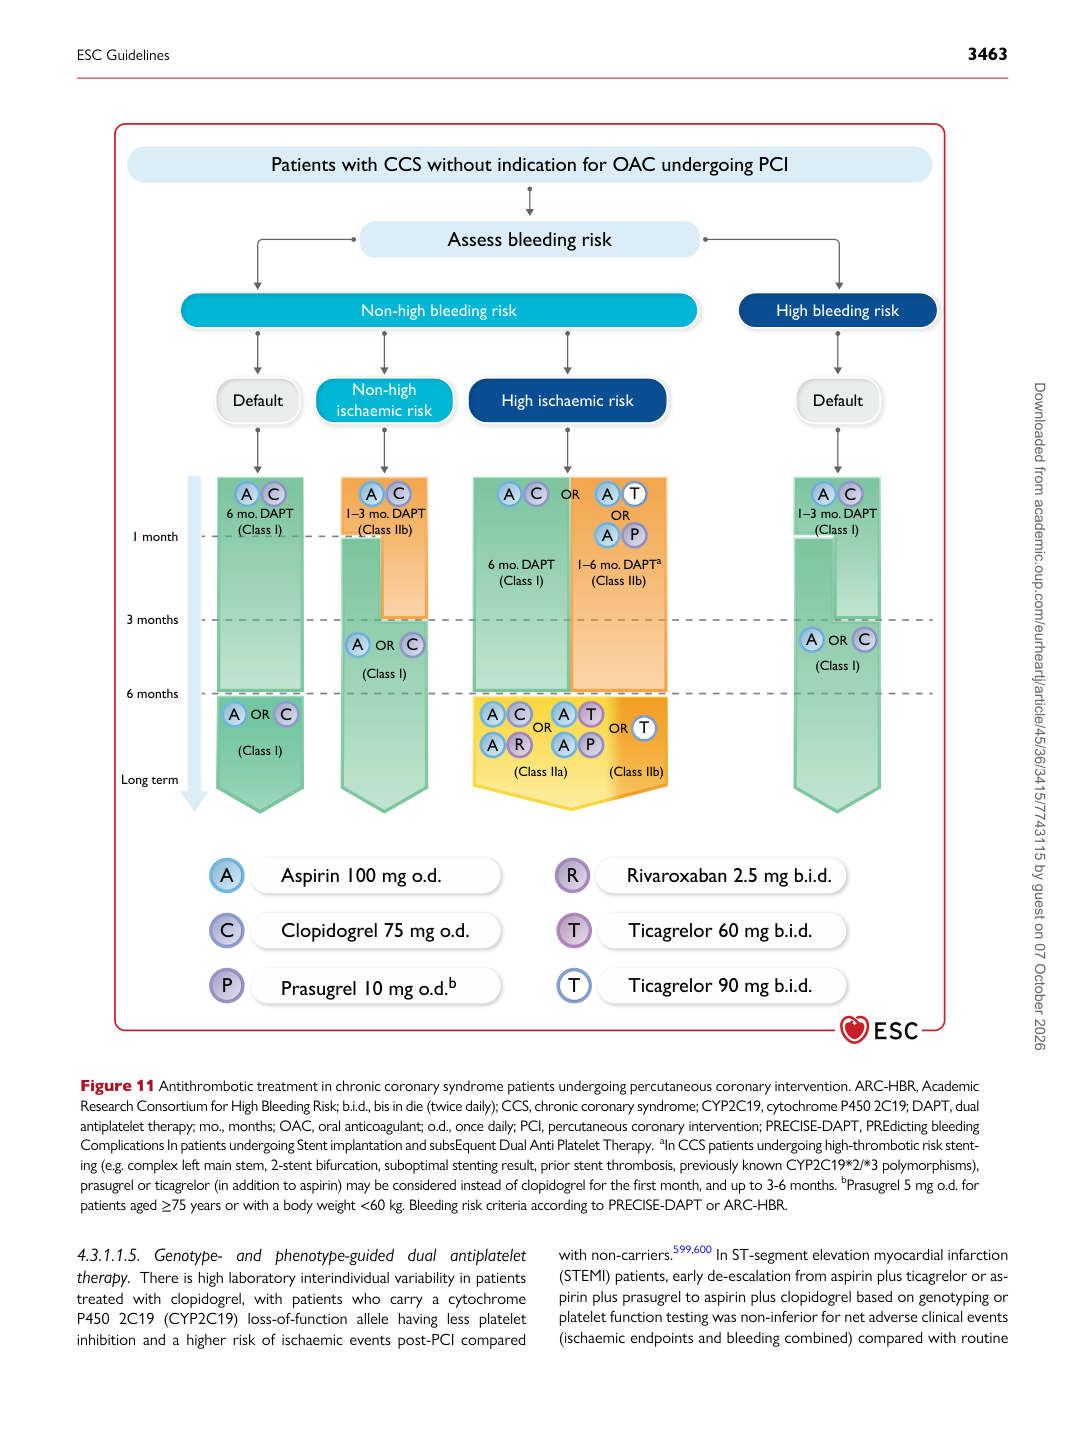
Figure 11 Antithrombotic treatment in chronic coronary syndrome patients undergoing percutaneous coronary intervention. ARC-HBR, Academic Research Consortium for High Bleeding Risk; b.i.d., bis in die (twice daily); CCS, chronic coronary syndrome; CYP2C19, cytochrome P450 2C19; DAPT, dual antiplatelet therapy; mo., months; OAC, oral anticoagulant; o.d., once daily; PCI, percutaneous coronary intervention; PRECISE-DAPT, PREdicting bleeding Complications In patients undergoing Stent implantation and subsEquent Dual Anti Platelet Therapy.  aIn CCS patients undergoing high-thrombotic risk stenting (e.g. complex left main stem, 2-stent bifurcation, suboptimal stenting result, prior stent thrombosis, previously known CYP2C19*2/*3 polymorphisms), prasugrel or ticagrelor (in addition to aspirin) may be considered instead of clopidogrel for the first month, and up to 3-6 months. bPrasugrel 5 mg o.d. for patients aged ≥75 years or with a body weight <60 kg. Bleeding risk criteria according to PRECISE-DAPT or ARC-HBR.

ESC Guidelines                                                                                                                                                                                          3463

Downloaded from academic.oup.com/eurheartj/article/45/36/3415/7743115 by guest on 07 October 2026