p.52 抽出テキスト
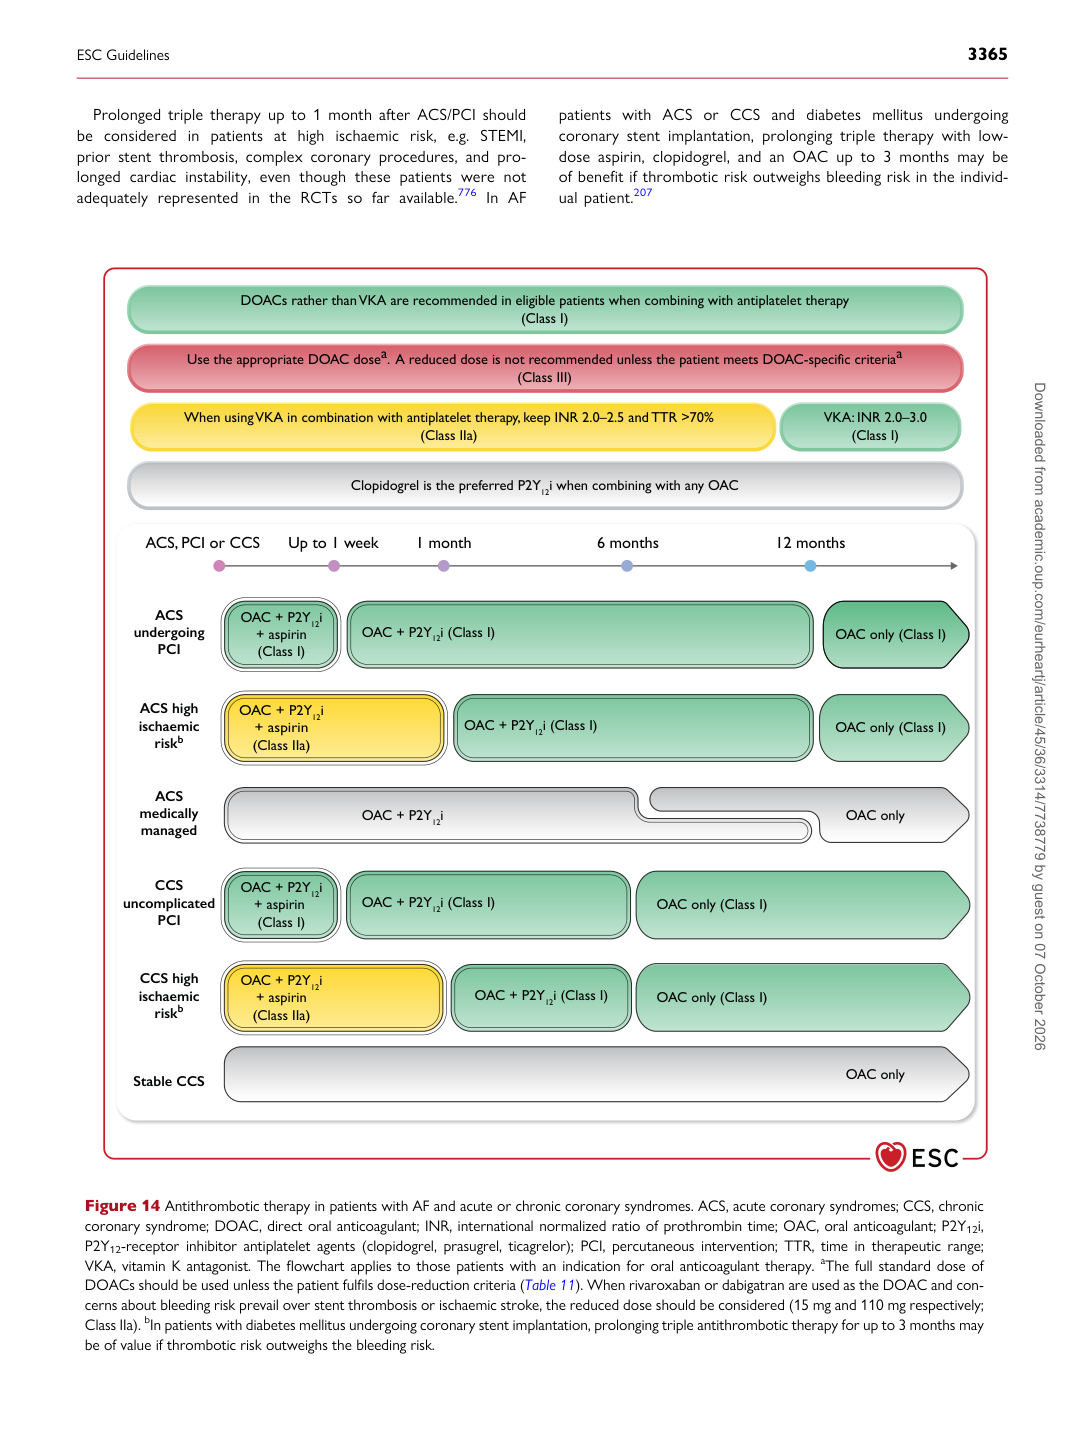
Prolonged triple therapy up to 1 month after ACS/PCI should be considered in patients at high ischaemic risk, e.g. STEMI, prior stent thrombosis, complex coronary procedures, and prolonged cardiac instability, even though these patients were not adequately represented in the RCTs so far available.776 In AF patients with ACS or CCS and diabetes mellitus undergoing coronary stent implantation, prolonging triple therapy with lowdose aspirin, clopidogrel, and an OAC up to 3 months may be of benefit if thrombotic risk outweighs bleeding risk in the individual patient.207

When using VKA in combination with antiplatelet therapy, keep INR 2.0–2.5 and TTR >70%

(Class IIa) VKA: INR 2.0–3.0

(Class I)

Clopidogrel is the preferred P2Y12i when combining with any OAC

Use the appropriate DOAC dosea.  A reduced dose is not recommended unless the patient meets DOAC-specific criteriaa

(Class III)

DOACs rather than VKA are recommended in eligible patients when combining with antiplatelet therapy

(Class I)

ACS, PCI or CCS Up to 1 week 1 month 6 months 12 months

CCS uncomplicated

PCI

CCS high ischaemic

riskb OAC + P2Y12i

+ aspirin (Class I)

OAC only (Class I) ACS undergoing

PCI OAC + P2Y12i (Class I)

OAC + P2Y12i

+ aspirin (Class I) OAC only (Class I) OAC + P2Y12i (Class I)

Stable CCS OAC + P2Y12i

+ aspirin (Class IIa) OAC only (Class I) OAC + P2Y12i (Class I)

ACS high ischaemic

riskb OAC + P2Y12i

+ aspirin (Class IIa) OAC only (Class I) OAC + P2Y12i (Class I)

ACS medically managed OAC only

OAC only

OAC + P2Y12i

Figure 14 Antithrombotic therapy in patients with AF and acute or chronic coronary syndromes. ACS, acute coronary syndromes; CCS, chronic coronary syndrome; DOAC, direct oral anticoagulant; INR, international normalized ratio of prothrombin time; OAC, oral anticoagulant; P2Y12i, P2Y12-receptor inhibitor antiplatelet agents (clopidogrel, prasugrel, ticagrelor); PCI, percutaneous intervention; TTR, time in therapeutic range; VKA, vitamin K antagonist. The flowchart applies to those patients with an indication for oral anticoagulant therapy. aThe full standard dose of DOACs should be used unless the patient fulfils dose-reduction criteria (Table 11). When rivaroxaban or dabigatran are used as the DOAC and concerns about bleeding risk prevail over stent thrombosis or ischaemic stroke, the reduced dose should be considered (15 mg and 110 mg respectively; Class IIa). bIn patients with diabetes mellitus undergoing coronary stent implantation, prolonging triple antithrombotic therapy for up to 3 months may be of value if thrombotic risk outweighs the bleeding risk.

ESC Guidelines                                                                                                                                                                                          3365

Downloaded from academic.oup.com/eurheartj/article/45/36/3314/7738779 by guest on 07 October 2026