p.68 抽出テキスト
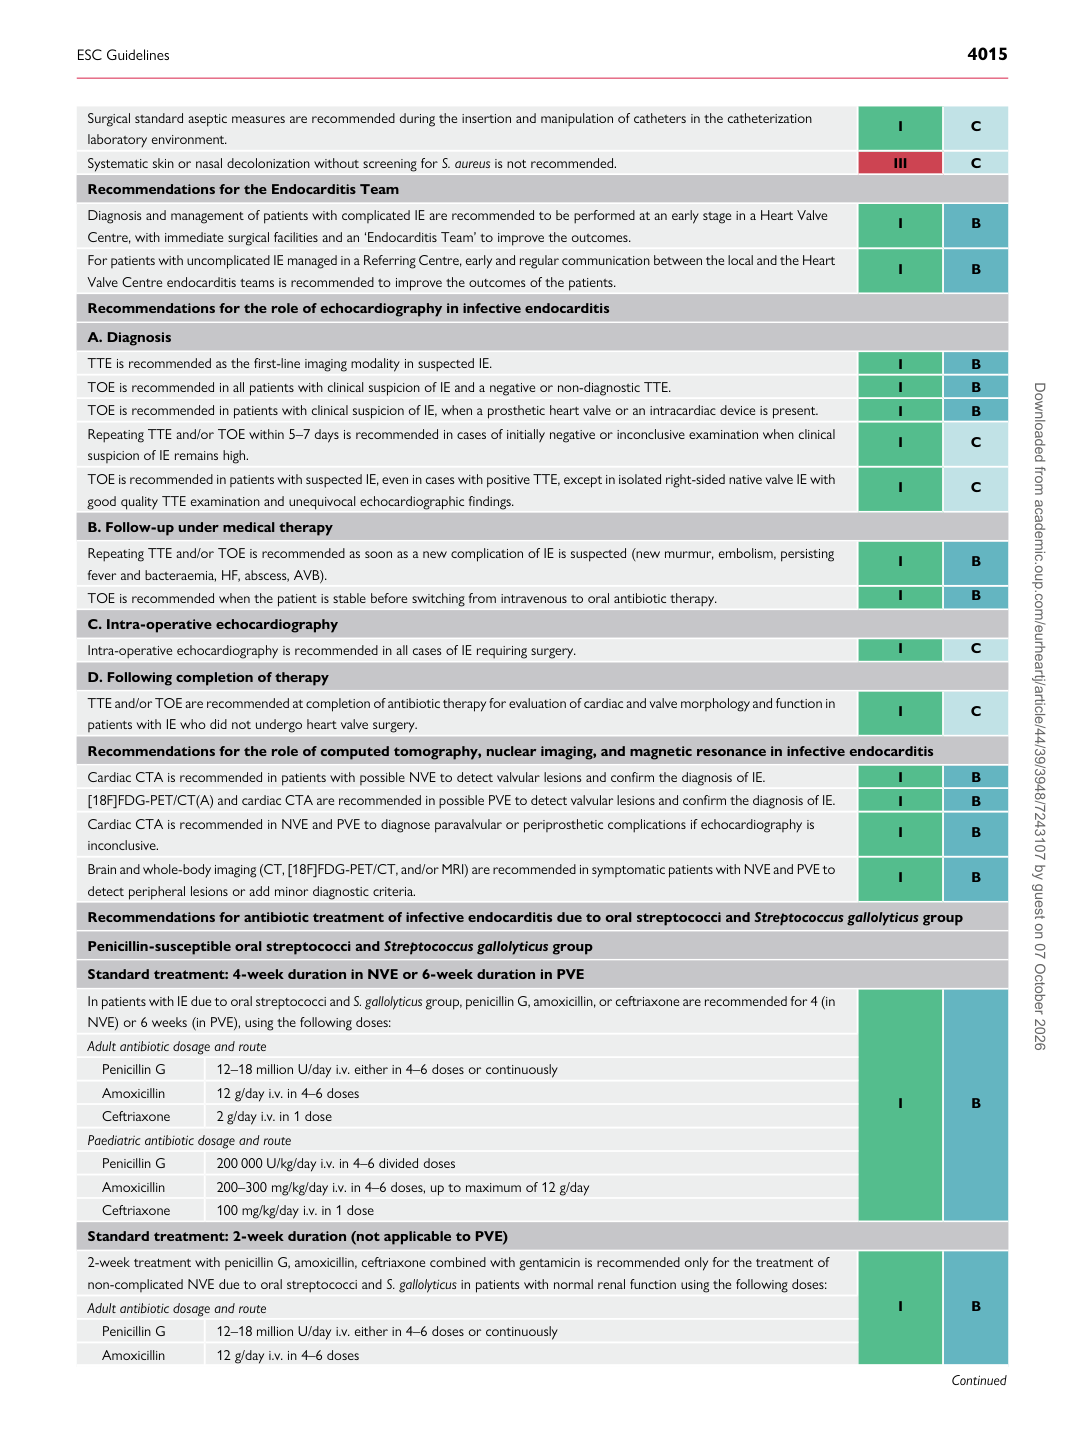
Surgical standard aseptic measures are recommended during the insertion and manipulation of catheters in the catheterization laboratory environment. I C Systematic skin or nasal decolonization without screening for S. aureus is not recommended. III C Recommendations for the Endocarditis Team Diagnosis and management of patients with complicated IE are recommended to be performed at an early stage in a Heart Valve Centre, with immediate surgical facilities and an ‘Endocarditis Team’ to improve the outcomes. I B For patients with uncomplicated IE managed in a Referring Centre, early and regular communication between the local and the Heart Valve Centre endocarditis teams is recommended to improve the outcomes of the patients. I B Recommendations for the role of echocardiography in infective endocarditis A. Diagnosis TTE is recommended as the first-line imaging modality in suspected IE. I B TOE is recommended in all patients with clinical suspicion of IE and a negative or non-diagnostic TTE. I B TOE is recommended in patients with clinical suspicion of IE, when a prosthetic heart valve or an intracardiac device is present. I B Repeating TTE and/or TOE within 5–7 days is recommended in cases of initially negative or inconclusive examination when clinical suspicion of IE remains high. I C TOE is recommended in patients with suspected IE, even in cases with positive TTE, except in isolated right-sided native valve IE with good quality TTE examination and unequivocal echocardiographic findings. I C B. Follow-up under medical therapy Repeating TTE and/or TOE is recommended as soon as a new complication of IE is suspected (new murmur, embolism, persisting fever and bacteraemia, HF, abscess, AVB). I B TOE is recommended when the patient is stable before switching from intravenous to oral antibiotic therapy. I B C. Intra-operative echocardiography Intra-operative echocardiography is recommended in all cases of IE requiring surgery. I C D. Following completion of therapy TTE and/or TOE are recommended at completion of antibiotic therapy for evaluation of cardiac and valve morphology and function in patients with IE who did not undergo heart valve surgery. I C Recommendations for the role of computed tomography, nuclear imaging, and magnetic resonance in infective endocarditis Cardiac CTA is recommended in patients with possible NVE to detect valvular lesions and confirm the diagnosis of IE. I B [18F]FDG-PET/CT(A) and cardiac CTA are recommended in possible PVE to detect valvular lesions and confirm the diagnosis of IE. I B Cardiac CTA is recommended in NVE and PVE to diagnose paravalvular or periprosthetic complications if echocardiography is inconclusive. I B Brain and whole-body imaging (CT, [18F]FDG-PET/CT, and/or MRI) are recommended in symptomatic patients with NVE and PVE to detect peripheral lesions or add minor diagnostic criteria. I B Recommendations for antibiotic treatment of infective endocarditis due to oral streptococci and Streptococcus gallolyticus group Penicillin-susceptible oral streptococci and Streptococcus gallolyticus group Standard treatment: 4-week duration in NVE or 6-week duration in PVE In patients with IE due to oral streptococci and S. gallolyticus group, penicillin G, amoxicillin, or ceftriaxone are recommended for 4 (in NVE) or 6 weeks (in PVE), using the following doses:

I B

Adult antibiotic dosage and route

Penicillin G 12–18 million U/day i.v. either in 4–6 doses or continuously Amoxicillin 12 g/day i.v. in 4–6 doses Ceftriaxone 2 g/day i.v. in 1 dose Paediatric antibiotic dosage and route

Penicillin G 200 000 U/kg/day i.v. in 4–6 divided doses Amoxicillin 200–300 mg/kg/day i.v. in 4–6 doses, up to maximum of 12 g/day Ceftriaxone 100 mg/kg/day i.v. in 1 dose Standard treatment: 2-week duration (not applicable to PVE) 2-week treatment with penicillin G, amoxicillin, ceftriaxone combined with gentamicin is recommended only for the treatment of non-complicated NVE due to oral streptococci and S. gallolyticus in patients with normal renal function using the following doses: I B Adult antibiotic dosage and route

Penicillin G 12–18 million U/day i.v. either in 4–6 doses or continuously Amoxicillin 12 g/day i.v. in 4–6 doses

ESC Guidelines                                                                                                                                                                                          4015

Downloaded from academic.oup.com/eurheartj/article/44/39/3948/7243107 by guest on 07 October 2026