p.36 抽出テキスト
7.9 Gram-negative bacteria

7.9.1. Haemophilus, Aggregatibacter, Cardiobacterium, Eikenella, and Kingella-related species Haemophilus, Aggregatibacter (previously Actinobacillus), Cardiobacterium, Eikenella, and Kingella (HACEK) Gram-negative bacilli are fastidious organisms that require special investigations when they are the suspected cause of IE (see also Section 5). Because they grow slowly, standard MIC tests may be difficult to interpret. Some HACEK group bacilli produce betalactamases, and therefore ampicillin is no longer the first-line option. Conversely, they are susceptible to ceftriaxone, other third-generation cephalosporins, and fluoroquinolones. The standard treatment is ceftriaxone 2 g/day for 4 weeks in NVE and for 6 weeks in PVE. If they do not produce beta-lactamase, ampicillin (12 g/day i.v. in 4 or 6 doses) for 4–6 weeks plus gentamicin (3 mg/kg/day divided into 2 or 3 doses) for 2 weeks is an

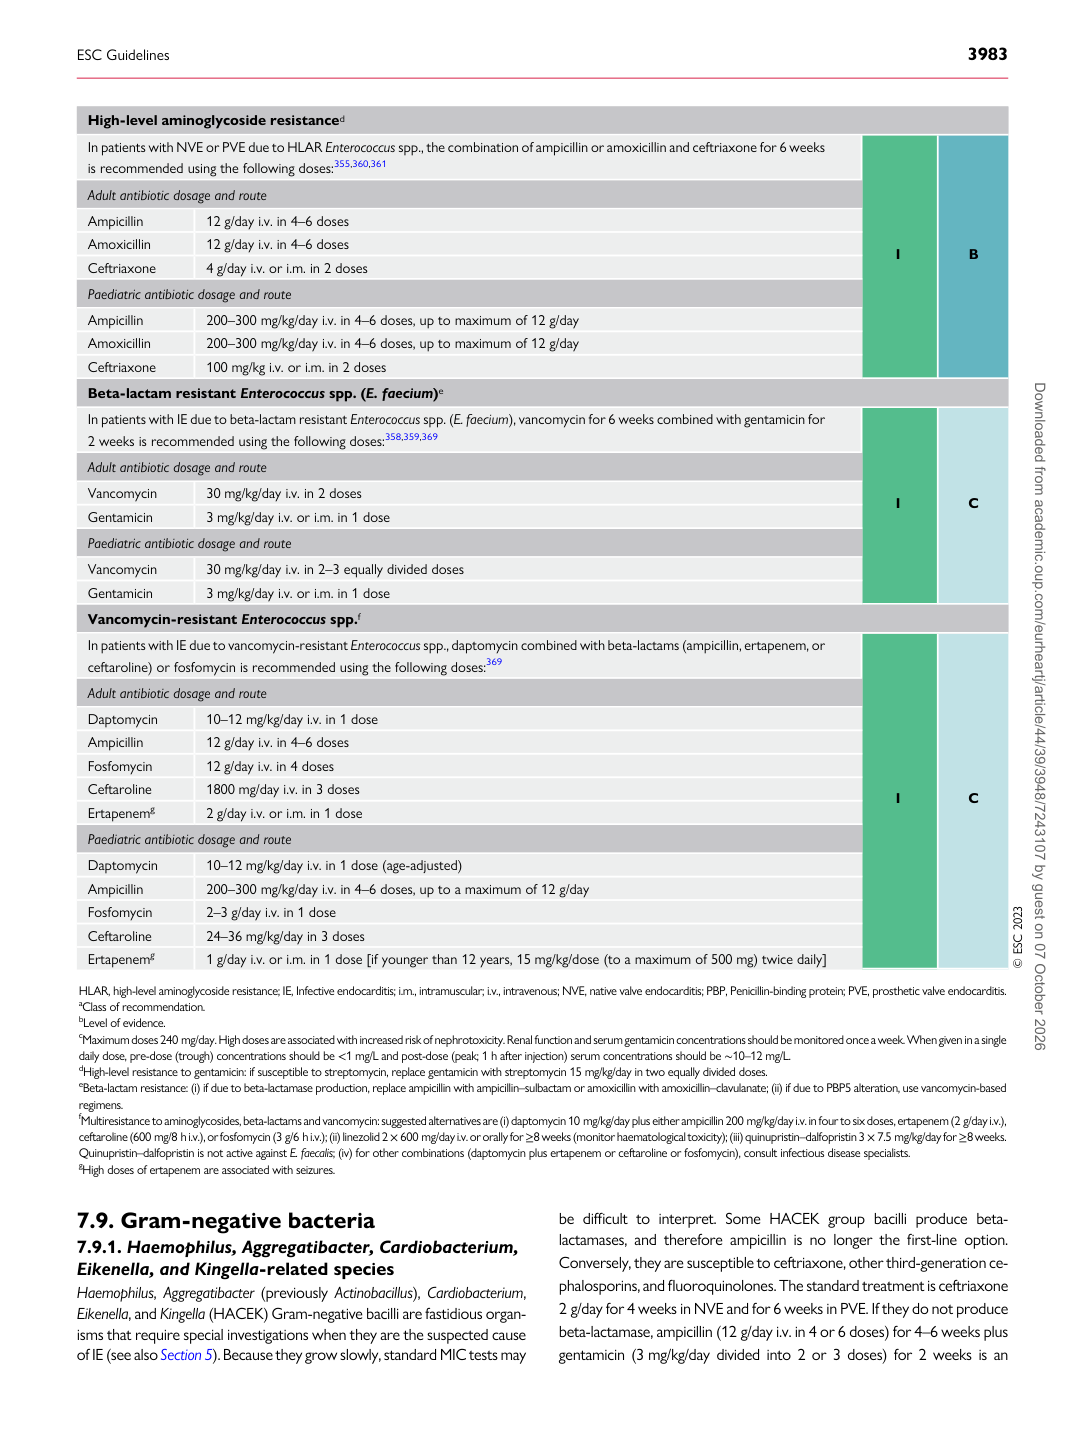
High-level aminoglycoside resistanced In patients with NVE or PVE due to HLAR Enterococcus spp., the combination of ampicillin or amoxicillin and ceftriaxone for 6 weeks is recommended using the following doses:355,360,361

I B

Adult antibiotic dosage and route Ampicillin 12 g/day i.v. in 4–6 doses Amoxicillin 12 g/day i.v. in 4–6 doses Ceftriaxone 4 g/day i.v. or i.m. in 2 doses Paediatric antibiotic dosage and route Ampicillin 200–300 mg/kg/day i.v. in 4–6 doses, up to maximum of 12 g/day Amoxicillin 200–300 mg/kg/day i.v. in 4–6 doses, up to maximum of 12 g/day Ceftriaxone 100 mg/kg i.v. or i.m. in 2 doses Beta-lactam resistant Enterococcus spp. (E. faecium)e In patients with IE due to beta-lactam resistant Enterococcus spp. (E. faecium), vancomycin for 6 weeks combined with gentamicin for 2 weeks is recommended using the following doses:358,359,369

I C

Adult antibiotic dosage and route Vancomycin 30 mg/kg/day i.v. in 2 doses Gentamicin 3 mg/kg/day i.v. or i.m. in 1 dose Paediatric antibiotic dosage and route Vancomycin 30 mg/kg/day i.v. in 2–3 equally divided doses Gentamicin 3 mg/kg/day i.v. or i.m. in 1 dose Vancomycin-resistant Enterococcus spp.f In patients with IE due to vancomycin-resistant Enterococcus spp., daptomycin combined with beta-lactams (ampicillin, ertapenem, or ceftaroline) or fosfomycin is recommended using the following doses:369

I C

Adult antibiotic dosage and route Daptomycin 10–12 mg/kg/day i.v. in 1 dose Ampicillin 12 g/day i.v. in 4–6 doses Fosfomycin 12 g/day i.v. in 4 doses Ceftaroline 1800 mg/day i.v. in 3 doses Ertapenemg 2 g/day i.v. or i.m. in 1 dose Paediatric antibiotic dosage and route Daptomycin 10–12 mg/kg/day i.v. in 1 dose (age-adjusted) Ampicillin 200–300 mg/kg/day i.v. in 4–6 doses, up to a maximum of 12 g/day Fosfomycin 2–3 g/day i.v. in 1 dose Ceftaroline 24–36 mg/kg/day in 3 doses Ertapenemg 1 g/day i.v. or i.m. in 1 dose [if younger than 12 years, 15 mg/kg/dose (to a maximum of 500 mg) twice daily] © ESC 2023

HLAR, high-level aminoglycoside resistance; IE, Infective endocarditis; i.m., intramuscular; i.v., intravenous; NVE, native valve endocarditis; PBP, Penicillin-binding protein; PVE, prosthetic valve endocarditis. aClass of recommendation. bLevel of evidence. cMaximum doses 240 mg/day. High doses are associated with increased risk of nephrotoxicity. Renal function and serum gentamicin concentrations should be monitored once a week. When given in a single daily dose, pre-dose (trough) concentrations should be <1 mg/L and post-dose (peak; 1 h after injection) serum concentrations should be ∼10–12 mg/L. dHigh-level resistance to gentamicin: if susceptible to streptomycin, replace gentamicin with streptomycin 15 mg/kg/day in two equally divided doses. eBeta-lactam resistance: (i) if due to beta-lactamase production, replace ampicillin with ampicillin–sulbactam or amoxicillin with amoxicillin–clavulanate; (ii) if due to PBP5 alteration, use vancomycin-based regimens. fMultiresistance to aminoglycosides, beta-lactams and vancomycin: suggested alternatives are (i) daptomycin 10 mg/kg/day plus either ampicillin 200 mg/kg/day i.v. in four to six doses, ertapenem (2 g/day i.v.), ceftaroline (600 mg/8 h i.v.), or fosfomycin (3 g/6 h i.v.); (ii) linezolid 2 × 600 mg/day i.v. or orally for ≥8 weeks (monitor haematological toxicity); (iii) quinupristin–dalfopristin 3 × 7.5 mg/kg/day for ≥8 weeks. Quinupristin–dalfopristin is not active against E. faecalis; (iv) for other combinations (daptomycin plus ertapenem or ceftaroline or fosfomycin), consult infectious disease specialists. gHigh doses of ertapenem are associated with seizures.

ESC Guidelines                                                                                                                                                                                          3983

Downloaded from academic.oup.com/eurheartj/article/44/39/3948/7243107 by guest on 07 October 2026