p.34 抽出テキスト
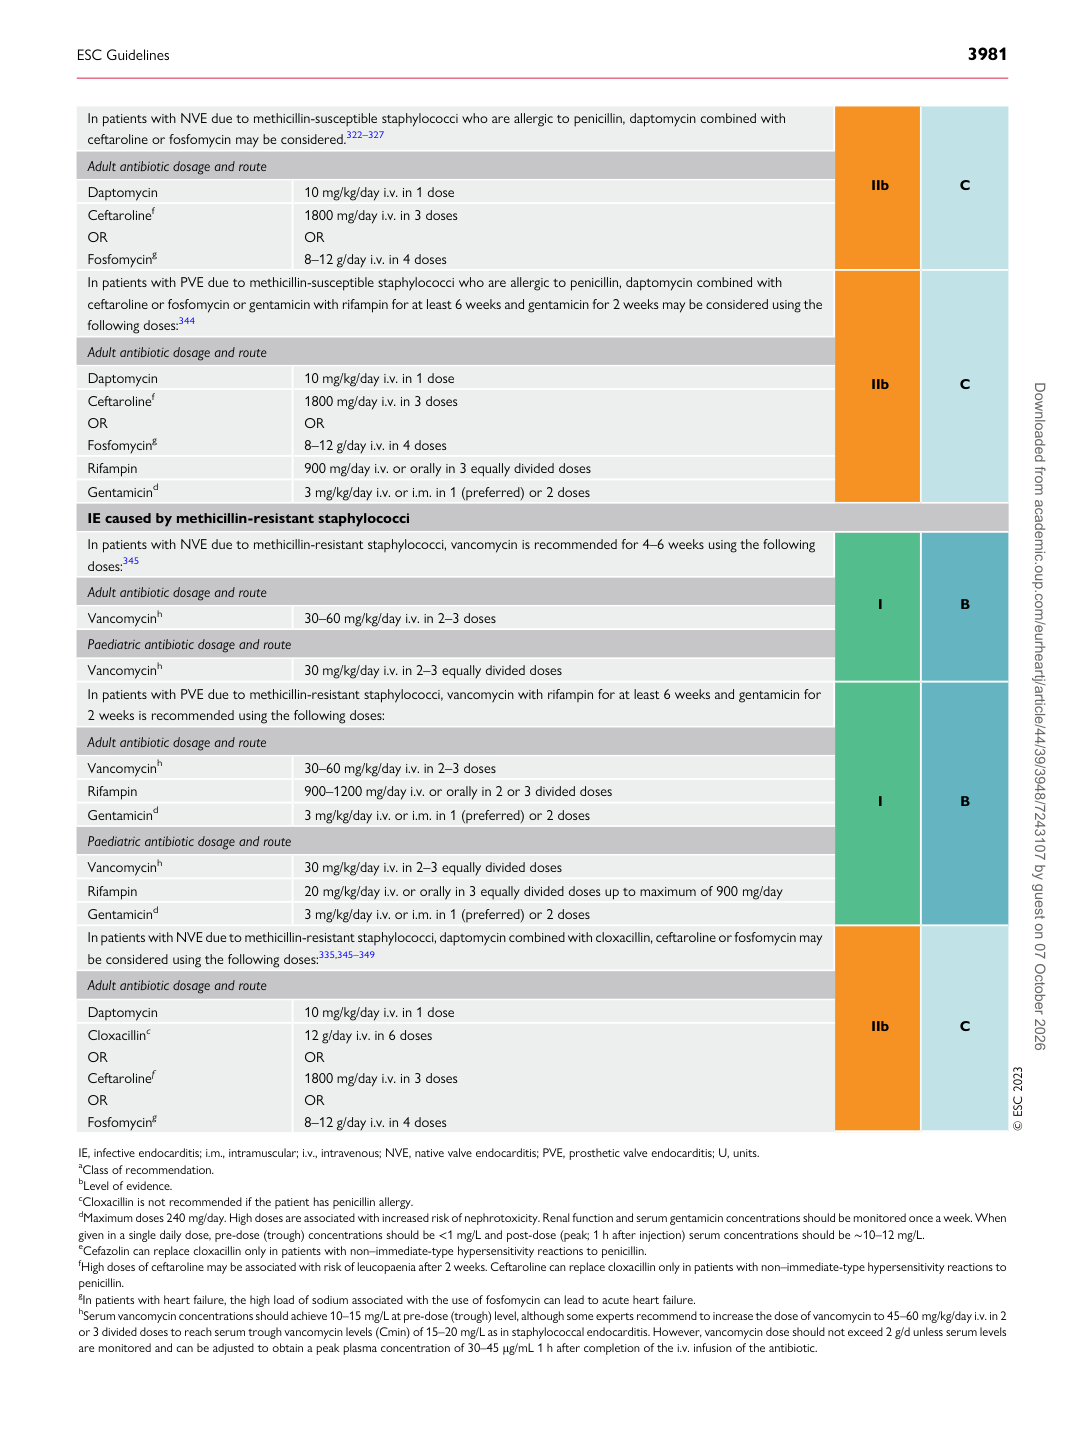
In patients with NVE due to methicillin-susceptible staphylococci who are allergic to penicillin, daptomycin combined with ceftaroline or fosfomycin may be considered.322–327 IIb C Adult antibiotic dosage and route Daptomycin 10 mg/kg/day i.v. in 1 dose Ceftarolinef OR Fosfomycing 1800 mg/day i.v. in 3 doses

OR 8–12 g/day i.v. in 4 doses

In patients with PVE due to methicillin-susceptible staphylococci who are allergic to penicillin, daptomycin combined with ceftaroline or fosfomycin or gentamicin with rifampin for at least 6 weeks and gentamicin for 2 weeks may be considered using the following doses:344

IIb C

Adult antibiotic dosage and route Daptomycin 10 mg/kg/day i.v. in 1 dose Ceftarolinef OR Fosfomycing 1800 mg/day i.v. in 3 doses OR

8–12 g/day i.v. in 4 doses

Rifampin 900 mg/day i.v. or orally in 3 equally divided doses Gentamicind 3 mg/kg/day i.v. or i.m. in 1 (preferred) or 2 doses IE caused by methicillin-resistant staphylococci In patients with NVE due to methicillin-resistant staphylococci, vancomycin is recommended for 4–6 weeks using the following doses:345 I B Adult antibiotic dosage and route Vancomycinh 30–60 mg/kg/day i.v. in 2–3 doses Paediatric antibiotic dosage and route Vancomycinh 30 mg/kg/day i.v. in 2–3 equally divided doses In patients with PVE due to methicillin-resistant staphylococci, vancomycin with rifampin for at least 6 weeks and gentamicin for 2 weeks is recommended using the following doses:

I B

Adult antibiotic dosage and route Vancomycinh 30–60 mg/kg/day i.v. in 2–3 doses Rifampin 900–1200 mg/day i.v. or orally in 2 or 3 divided doses Gentamicind 3 mg/kg/day i.v. or i.m. in 1 (preferred) or 2 doses Paediatric antibiotic dosage and route Vancomycinh 30 mg/kg/day i.v. in 2–3 equally divided doses Rifampin 20 mg/kg/day i.v. or orally in 3 equally divided doses up to maximum of 900 mg/day Gentamicind 3 mg/kg/day i.v. or i.m. in 1 (preferred) or 2 doses In patients with NVE due to methicillin-resistant staphylococci, daptomycin combined with cloxacillin, ceftaroline or fosfomycin may be considered using the following doses:335,345–349

IIb C

Adult antibiotic dosage and route Daptomycin 10 mg/kg/day i.v. in 1 dose Cloxacillinc OR Ceftarolinef OR Fosfomycing 12 g/day i.v. in 6 doses

OR 1800 mg/day i.v. in 3 doses OR 8–12 g/day i.v. in 4 doses © ESC 2023

IE, infective endocarditis; i.m., intramuscular; i.v., intravenous; NVE, native valve endocarditis; PVE, prosthetic valve endocarditis; U, units. aClass of recommendation. bLevel of evidence. cCloxacillin is not recommended if the patient has penicillin allergy. dMaximum doses 240 mg/day. High doses are associated with increased risk of nephrotoxicity. Renal function and serum gentamicin concentrations should be monitored once a week. When given in a single daily dose, pre-dose (trough) concentrations should be <1 mg/L and post-dose (peak; 1 h after injection) serum concentrations should be ∼10–12 mg/L. eCefazolin can replace cloxacillin only in patients with non–immediate-type hypersensitivity reactions to penicillin. fHigh doses of ceftaroline may be associated with risk of leucopaenia after 2 weeks. Ceftaroline can replace cloxacillin only in patients with non–immediate-type hypersensitivity reactions to penicillin. gIn patients with heart failure, the high load of sodium associated with the use of fosfomycin can lead to acute heart failure. hSerum vancomycin concentrations should achieve 10–15 mg/L at pre-dose (trough) level, although some experts recommend to increase the dose of vancomycin to 45–60 mg/kg/day i.v. in 2 or 3 divided doses to reach serum trough vancomycin levels (Cmin) of 15–20 mg/L as in staphylococcal endocarditis. However, vancomycin dose should not exceed 2 g/d unless serum levels are monitored and can be adjusted to obtain a peak plasma concentration of 30–45 μg/mL 1 h after completion of the i.v. infusion of the antibiotic.

ESC Guidelines                                                                                                                                                                                          3981

Downloaded from academic.oup.com/eurheartj/article/44/39/3948/7243107 by guest on 07 October 2026