p.10 抽出テキスト
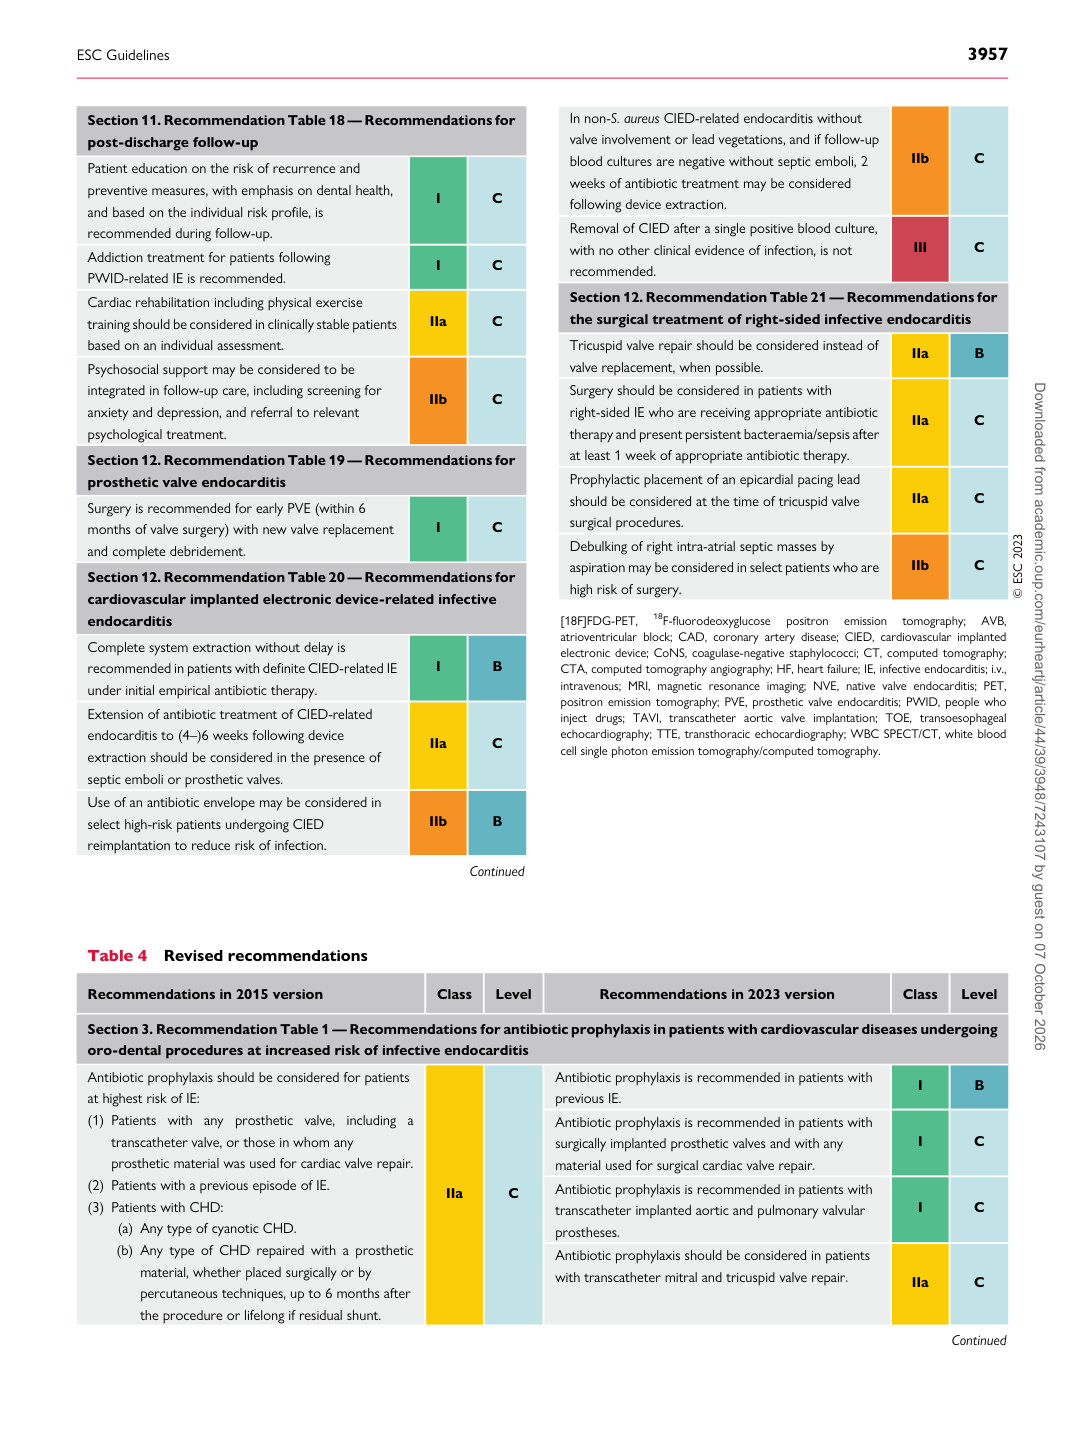
Section 11. Recommendation Table 18 — Recommendations for post-discharge follow-up Patient education on the risk of recurrence and preventive measures, with emphasis on dental health, and based on the individual risk profile, is recommended during follow-up. I C Addiction treatment for patients following PWID-related IE is recommended. I C Cardiac rehabilitation including physical exercise training should be considered in clinically stable patients based on an individual assessment. IIa C Psychosocial support may be considered to be integrated in follow-up care, including screening for anxiety and depression, and referral to relevant psychological treatment. IIb C Section 12. Recommendation Table 19 — Recommendations for prosthetic valve endocarditis Surgery is recommended for early PVE (within 6 months of valve surgery) with new valve replacement and complete debridement. I C Section 12. Recommendation Table 20 — Recommendations for cardiovascular implanted electronic device-related infective endocarditis Complete system extraction without delay is recommended in patients with definite CIED-related IE under initial empirical antibiotic therapy. I B Extension of antibiotic treatment of CIED-related endocarditis to (4–)6 weeks following device extraction should be considered in the presence of septic emboli or prosthetic valves. IIa C Use of an antibiotic envelope may be considered in select high-risk patients undergoing CIED reimplantation to reduce risk of infection. IIb B

Continued

Table 4 Revised recommendations

Recommendations in 2015 version Class Level Recommendations in 2023 version Class Level

Section 3. Recommendation Table 1 — Recommendations for antibiotic prophylaxis in patients with cardiovascular diseases undergoing oro-dental procedures at increased risk of infective endocarditis Antibiotic prophylaxis should be considered for patients at highest risk of IE: (1) Patients with any prosthetic valve, including a

transcatheter valve, or those in whom any prosthetic material was used for cardiac valve repair. (2) Patients with a previous episode of IE. (3) Patients with CHD:

(a) Any type of cyanotic CHD. (b) Any type of CHD repaired with a prosthetic

material, whether placed surgically or by percutaneous techniques, up to 6 months after the procedure or lifelong if residual shunt. IIa C Antibiotic prophylaxis is recommended in patients with

previous IE. I B Antibiotic prophylaxis is recommended in patients with surgically implanted prosthetic valves and with any material used for surgical cardiac valve repair. I C Antibiotic prophylaxis is recommended in patients with transcatheter implanted aortic and pulmonary valvular prostheses. I C Antibiotic prophylaxis should be considered in patients with transcatheter mitral and tricuspid valve repair. IIa C

Continued

In non-S. aureus CIED-related endocarditis without valve involvement or lead vegetations, and if follow-up blood cultures are negative without septic emboli, 2 weeks of antibiotic treatment may be considered following device extraction. IIb C Removal of CIED after a single positive blood culture, with no other clinical evidence of infection, is not recommended. III C Section 12. Recommendation Table 21 — Recommendations for the surgical treatment of right-sided infective endocarditis Tricuspid valve repair should be considered instead of valve replacement, when possible. IIa B Surgery should be considered in patients with right-sided IE who are receiving appropriate antibiotic therapy and present persistent bacteraemia/sepsis after at least 1 week of appropriate antibiotic therapy. IIa C Prophylactic placement of an epicardial pacing lead should be considered at the time of tricuspid valve surgical procedures. IIa C Debulking of right intra-atrial septic masses by aspiration may be considered in select patients who are high risk of surgery. IIb C © ESC 2023 [18F]FDG-PET, 18F-fluorodeoxyglucose positron emission tomography; AVB, atrioventricular block; CAD, coronary artery disease; CIED, cardiovascular implanted electronic device; CoNS, coagulase-negative staphylococci; CT, computed tomography; CTA, computed tomography angiography; HF, heart failure; IE, infective endocarditis; i.v., intravenous; MRI, magnetic resonance imaging; NVE, native valve endocarditis; PET, positron emission tomography; PVE, prosthetic valve endocarditis; PWID, people who inject drugs; TAVI, transcatheter aortic valve implantation; TOE, transoesophageal echocardiography; TTE, transthoracic echocardiography; WBC SPECT/CT, white blood cell single photon emission tomography/computed tomography.

ESC Guidelines                                                                                                                                                                                          3957

Downloaded from academic.oup.com/eurheartj/article/44/39/3948/7243107 by guest on 07 October 2026