p.73 抽出テキスト
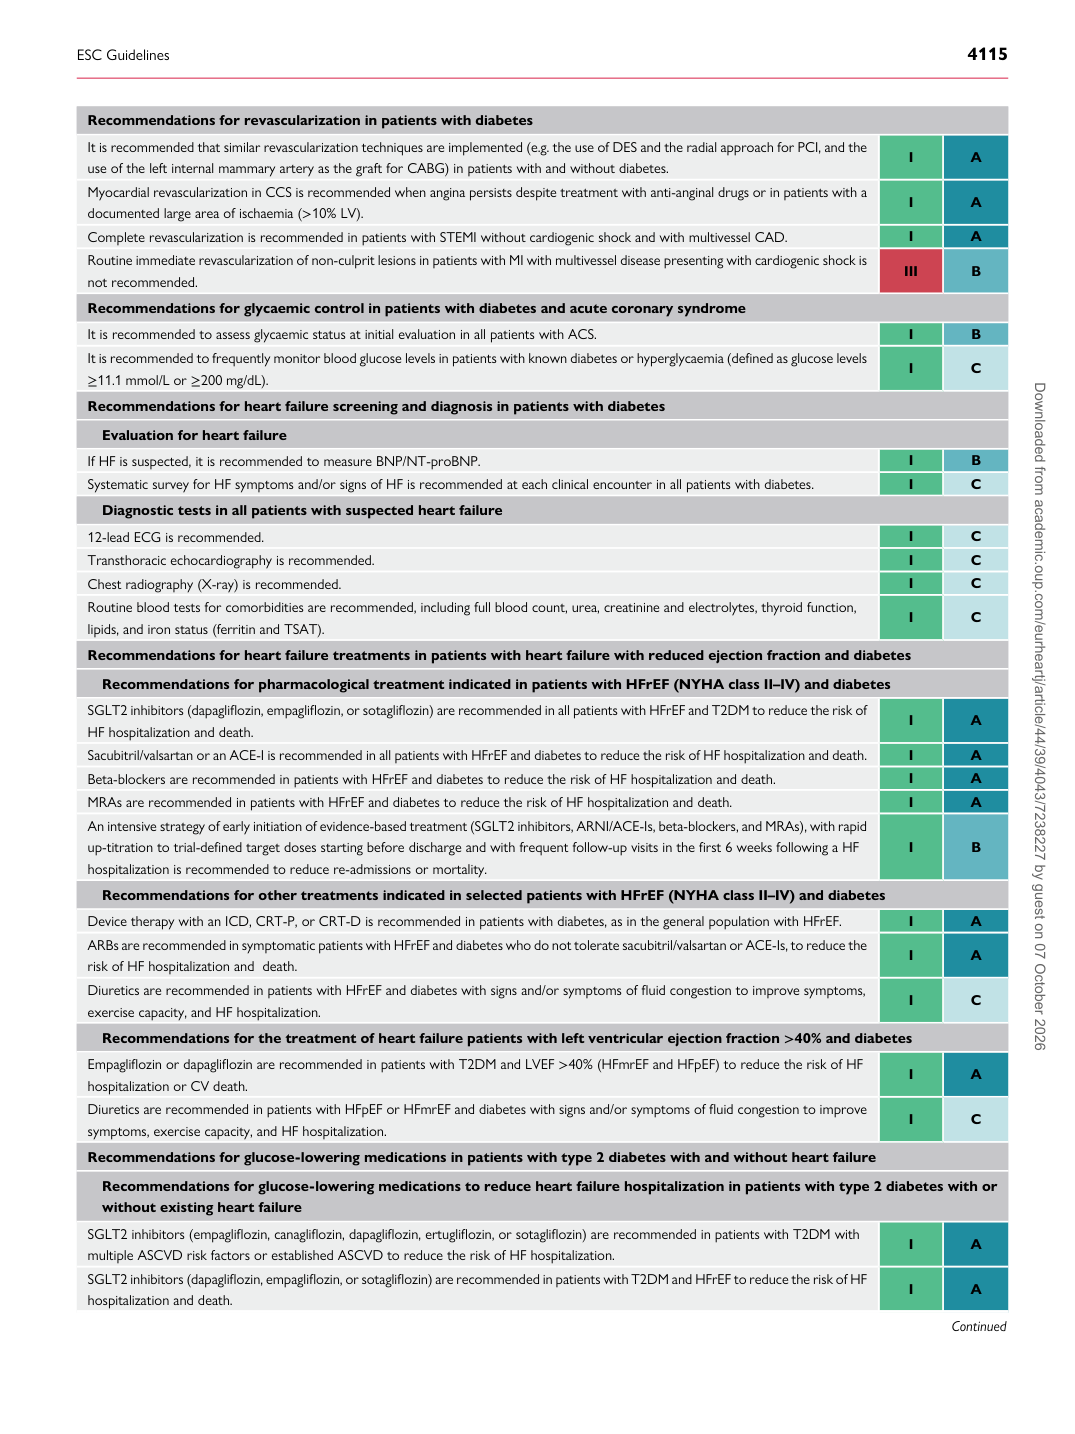
Recommendations for revascularization in patients with diabetes It is recommended that similar revascularization techniques are implemented (e.g. the use of DES and the radial approach for PCI, and the use of the left internal mammary artery as the graft for CABG) in patients with and without diabetes. I A Myocardial revascularization in CCS is recommended when angina persists despite treatment with anti-anginal drugs or in patients with a documented large area of ischaemia (>10% LV). I A Complete revascularization is recommended in patients with STEMI without cardiogenic shock and with multivessel CAD. I A Routine immediate revascularization of non-culprit lesions in patients with MI with multivessel disease presenting with cardiogenic shock is not recommended. III B Recommendations for glycaemic control in patients with diabetes and acute coronary syndrome It is recommended to assess glycaemic status at initial evaluation in all patients with ACS. I B It is recommended to frequently monitor blood glucose levels in patients with known diabetes or hyperglycaemia (defined as glucose levels ≥11.1 mmol/L or ≥200 mg/dL). I C Recommendations for heart failure screening and diagnosis in patients with diabetes

Evaluation for heart failure If HF is suspected, it is recommended to measure BNP/NT-proBNP. I B Systematic survey for HF symptoms and/or signs of HF is recommended at each clinical encounter in all patients with diabetes. I C

Diagnostic tests in all patients with suspected heart failure 12-lead ECG is recommended. I C Transthoracic echocardiography is recommended. I C Chest radiography (X-ray) is recommended. I C Routine blood tests for comorbidities are recommended, including full blood count, urea, creatinine and electrolytes, thyroid function, lipids, and iron status (ferritin and TSAT). I C Recommendations for heart failure treatments in patients with heart failure with reduced ejection fraction and diabetes

Recommendations for pharmacological treatment indicated in patients with HFrEF (NYHA class II–IV) and diabetes SGLT2 inhibitors (dapagliflozin, empagliflozin, or sotagliflozin) are recommended in all patients with HFrEF and T2DM to reduce the risk of HF hospitalization and death. I A Sacubitril/valsartan or an ACE-I is recommended in all patients with HFrEF and diabetes to reduce the risk of HF hospitalization and death. I A Beta-blockers are recommended in patients with HFrEF and diabetes to reduce the risk of HF hospitalization and death. I A MRAs are recommended in patients with HFrEF and diabetes to reduce the risk of HF hospitalization and death. I A An intensive strategy of early initiation of evidence-based treatment (SGLT2 inhibitors, ARNI/ACE-Is, beta-blockers, and MRAs), with rapid up-titration to trial-defined target doses starting before discharge and with frequent follow-up visits in the first 6 weeks following a HF hospitalization is recommended to reduce re-admissions or mortality. I B

Recommendations for other treatments indicated in selected patients with HFrEF (NYHA class II–IV) and diabetes Device therapy with an ICD, CRT-P, or CRT-D is recommended in patients with diabetes, as in the general population with HFrEF. I A ARBs are recommended in symptomatic patients with HFrEF and diabetes who do not tolerate sacubitril/valsartan or ACE-Is, to reduce the risk of HF hospitalization and  death. I A Diuretics are recommended in patients with HFrEF and diabetes with signs and/or symptoms of fluid congestion to improve symptoms, exercise capacity, and HF hospitalization. I C

Recommendations for the treatment of heart failure patients with left ventricular ejection fraction >40% and diabetes Empagliflozin or dapagliflozin are recommended in patients with T2DM and LVEF >40% (HFmrEF and HFpEF) to reduce the risk of HF hospitalization or CV death. I A Diuretics are recommended in patients with HFpEF or HFmrEF and diabetes with signs and/or symptoms of fluid congestion to improve symptoms, exercise capacity, and HF hospitalization. I C Recommendations for glucose-lowering medications in patients with type 2 diabetes with and without heart failure

Recommendations for glucose-lowering medications to reduce heart failure hospitalization in patients with type 2 diabetes with or without existing heart failure SGLT2 inhibitors (empagliflozin, canagliflozin, dapagliflozin, ertugliflozin, or sotagliflozin) are recommended in patients with T2DM with multiple ASCVD risk factors or established ASCVD to reduce the risk of HF hospitalization. I A SGLT2 inhibitors (dapagliflozin, empagliflozin, or sotagliflozin) are recommended in patients with T2DM and HFrEF to reduce the risk of HF hospitalization and death. I A

Continued

ESC Guidelines                                                                                                                                                                                          4115

Downloaded from academic.oup.com/eurheartj/article/44/39/4043/7238227 by guest on 07 October 2026