p.59 抽出テキスト
Information on the safety and efficacy of combining MRAs with SGLT2 inhibitors in CKD is limited as only ∼4% of FIDELIO-DKD, ∼8% of FIGARO-DKD, ∼5% of DAPA-CKD, and no CREDENCE participants were prescribed such a combination.153,718,719,721 Sub-group analyses considering those co-prescribed MRA and SGLT2 inhibitors suggest their combined use does not modify safety findings from the key trials.150,189,722–726 FIDELIO-DKD and FIGARO-DKD excluded patients with a potassium of >4.8 mmol/L, as MRAs cause hyperkalaemia.718,719

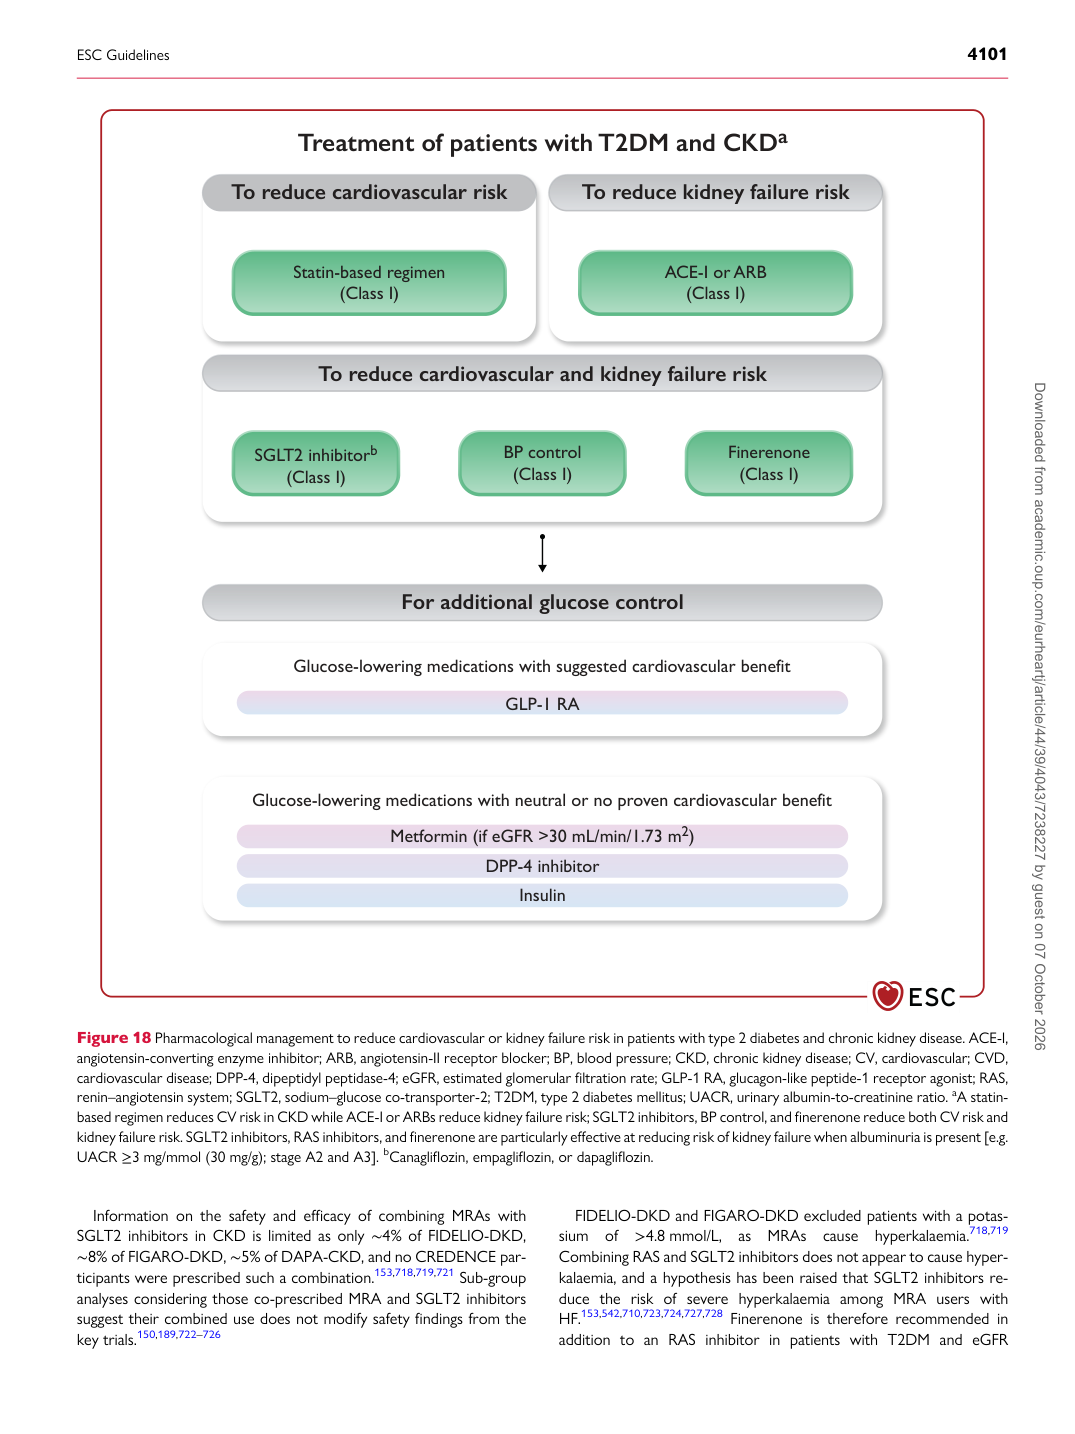
Combining RAS and SGLT2 inhibitors does not appear to cause hyperkalaemia, and a hypothesis has been raised that SGLT2 inhibitors reduce the risk of severe hyperkalaemia among MRA users with HF.153,542,710,723,724,727,728 Finerenone is therefore recommended in addition to an RAS inhibitor in patients with T2DM and eGFR

To reduce cardiovascular risk To reduce kidney failure risk

Statin-based regimen

(Class I)

SGLT2 inhibitorb

(Class I) BP control

(Class I) Finerenone

(Class I)

ACE-I or ARB

(Class I)

For additional glucose control

Glucose-lowering medications with suggested cardiovascular benefit

GLP-1 RA

DPP-4 inhibitor

Insulin

Metformin (if eGFR >30 mL/min/1.73 m2)

Glucose-lowering medications with neutral or no proven cardiovascular benefit

Treatment of patients with T2DM and CKDa

To reduce cardiovascular and kidney failure risk

Figure 18 Pharmacological management to reduce cardiovascular or kidney failure risk in patients with type 2 diabetes and chronic kidney disease. ACE-I, angiotensin-converting enzyme inhibitor; ARB, angiotensin-II receptor blocker; BP, blood pressure; CKD, chronic kidney disease; CV, cardiovascular; CVD, cardiovascular disease; DPP-4, dipeptidyl peptidase-4; eGFR, estimated glomerular filtration rate; GLP-1 RA, glucagon-like peptide-1 receptor agonist; RAS, renin–angiotensin system; SGLT2, sodium–glucose co-transporter-2; T2DM, type 2 diabetes mellitus; UACR, urinary albumin-to-creatinine ratio. aA statinbased regimen reduces CV risk in CKD while ACE-I or ARBs reduce kidney failure risk; SGLT2 inhibitors, BP control, and finerenone reduce both CV risk and kidney failure risk. SGLT2 inhibitors, RAS inhibitors, and finerenone are particularly effective at reducing risk of kidney failure when albuminuria is present [e.g. UACR ≥3 mg/mmol (30 mg/g); stage A2 and A3]. bCanagliflozin, empagliflozin, or dapagliflozin.

ESC Guidelines                                                                                                                                                                                          4101

Downloaded from academic.oup.com/eurheartj/article/44/39/4043/7238227 by guest on 07 October 2026