p.52 抽出テキスト
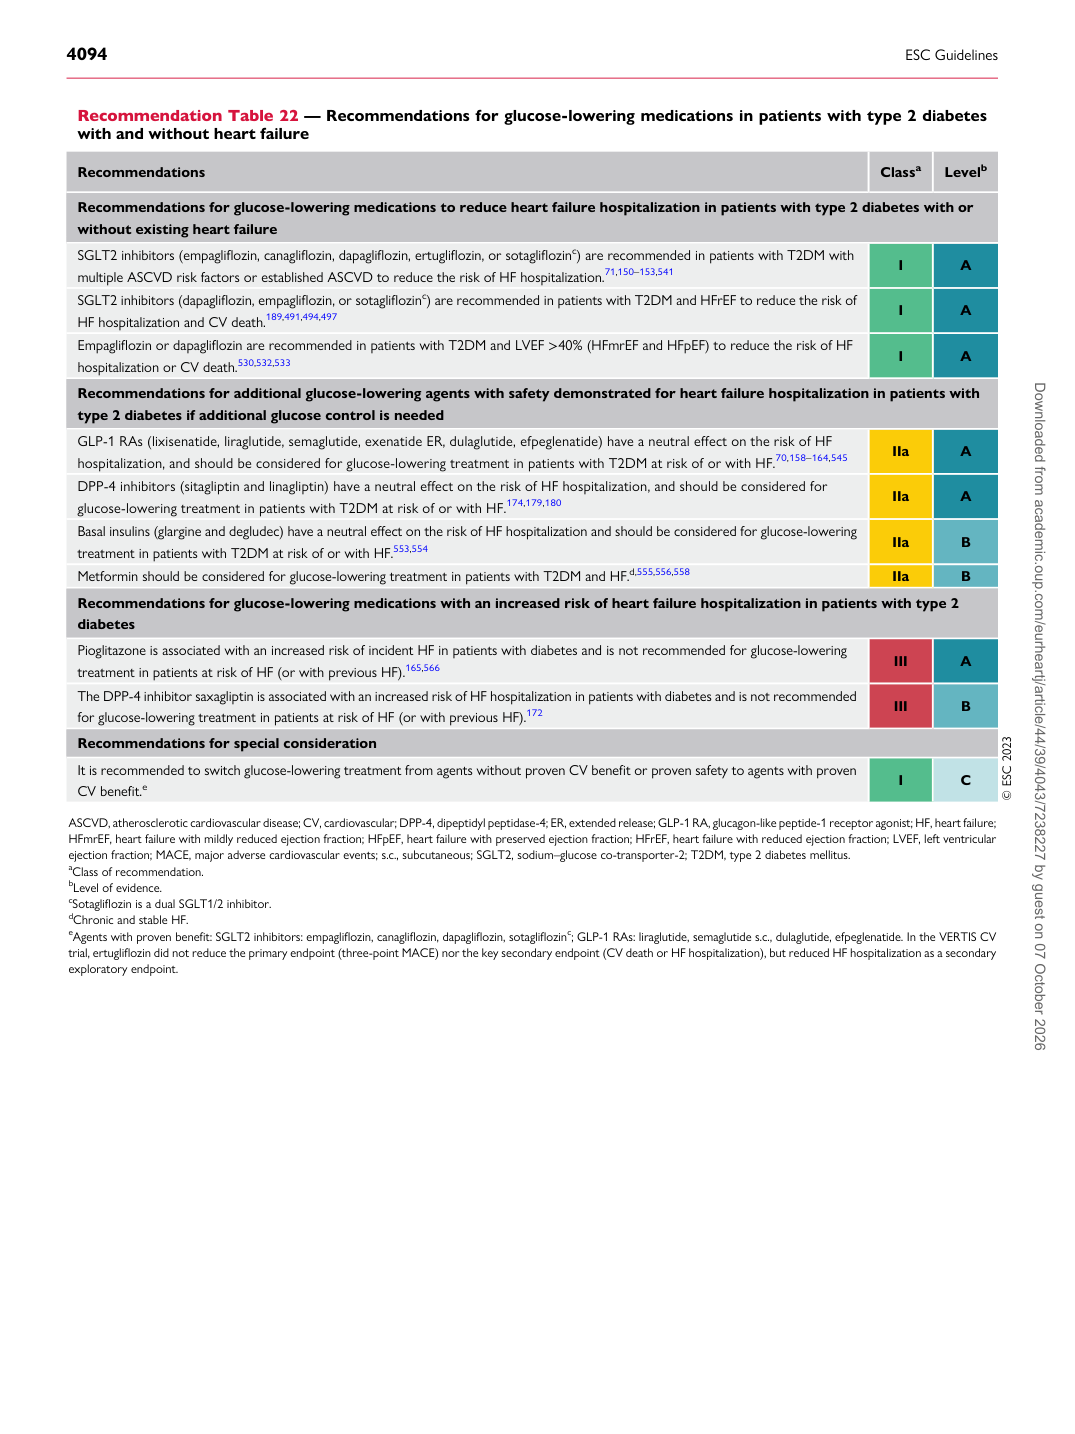
Recommendation Table 22 — Recommendations for glucose-lowering medications in patients with type 2 diabetes with and without heart failure

Recommendations Classa Levelb

Recommendations for glucose-lowering medications to reduce heart failure hospitalization in patients with type 2 diabetes with or without existing heart failure SGLT2 inhibitors (empagliflozin, canagliflozin, dapagliflozin, ertugliflozin, or sotagliflozinc) are recommended in patients with T2DM with multiple ASCVD risk factors or established ASCVD to reduce the risk of HF hospitalization.71,150–153,541 I A SGLT2 inhibitors (dapagliflozin, empagliflozin, or sotagliflozinc) are recommended in patients with T2DM and HFrEF to reduce the risk of HF hospitalization and CV death.189,491,494,497 I A Empagliflozin or dapagliflozin are recommended in patients with T2DM and LVEF >40% (HFmrEF and HFpEF) to reduce the risk of HF hospitalization or CV death.530,532,533 I A Recommendations for additional glucose-lowering agents with safety demonstrated for heart failure hospitalization in patients with type 2 diabetes if additional glucose control is needed GLP-1 RAs (lixisenatide, liraglutide, semaglutide, exenatide ER, dulaglutide, efpeglenatide) have a neutral effect on the risk of HF hospitalization, and should be considered for glucose-lowering treatment in patients with T2DM at risk of or with HF.70,158–164,545 IIa A DPP-4 inhibitors (sitagliptin and linagliptin) have a neutral effect on the risk of HF hospitalization, and should be considered for glucose-lowering treatment in patients with T2DM at risk of or with HF.174,179,180 IIa A Basal insulins (glargine and degludec) have a neutral effect on the risk of HF hospitalization and should be considered for glucose-lowering treatment in patients with T2DM at risk of or with HF.553,554 IIa B Metformin should be considered for glucose-lowering treatment in patients with T2DM and HF.d,555,556,558 IIa B Recommendations for glucose-lowering medications with an increased risk of heart failure hospitalization in patients with type 2 diabetes Pioglitazone is associated with an increased risk of incident HF in patients with diabetes and is not recommended for glucose-lowering treatment in patients at risk of HF (or with previous HF).165,566 III A The DPP-4 inhibitor saxagliptin is associated with an increased risk of HF hospitalization in patients with diabetes and is not recommended for glucose-lowering treatment in patients at risk of HF (or with previous HF).172 III B Recommendations for special consideration It is recommended to switch glucose-lowering treatment from agents without proven CV benefit or proven safety to agents with proven CV benefit.e I C © ESC 2023

ASCVD, atherosclerotic cardiovascular disease; CV, cardiovascular; DPP-4, dipeptidyl peptidase-4; ER, extended release; GLP-1 RA, glucagon-like peptide-1 receptor agonist; HF, heart failure; HFmrEF, heart failure with mildly reduced ejection fraction; HFpEF, heart failure with preserved ejection fraction; HFrEF, heart failure with reduced ejection fraction; LVEF, left ventricular ejection fraction; MACE, major adverse cardiovascular events; s.c., subcutaneous; SGLT2, sodium–glucose co-transporter-2; T2DM, type 2 diabetes mellitus. aClass of recommendation. bLevel of evidence. cSotagliflozin is a dual SGLT1/2 inhibitor. dChronic and stable HF. eAgents with proven benefit: SGLT2 inhibitors: empagliflozin, canagliflozin, dapagliflozin, sotagliflozinc; GLP-1 RAs: liraglutide, semaglutide s.c., dulaglutide, efpeglenatide. In the VERTIS CV trial, ertugliflozin did not reduce the primary endpoint (three-point MACE) nor the key secondary endpoint (CV death or HF hospitalization), but reduced HF hospitalization as a secondary exploratory endpoint. Downloaded from academic.oup.com/eurheartj/article/44/39/4043/7238227 by guest on 07 October 2026