p.38 抽出テキスト
Low dose ASA

(Class I)

Revascularization (PCI, CABG) for ACS and CCS in patients with

diabetes and no indication for anticoagulation

DAPT Low dose ASA and prasugrel or ticagrelor

(Class I) DAPT Low dose ASA and prasugrel or ticagrelor

(Class 1) DAPT Low dose ASA and clopidogrel

(Class I)

Low dose ASA (Class I) Low dose

ASA (Class I)

Low dose ASA (Class I)

Low dose ASA (Class I) DAPT based on

bleeding risk (Class Ila)

PCI CABG

ACS

PCI CABG

CCS

0 months

6 months

12 months

24 months

36 months

Time

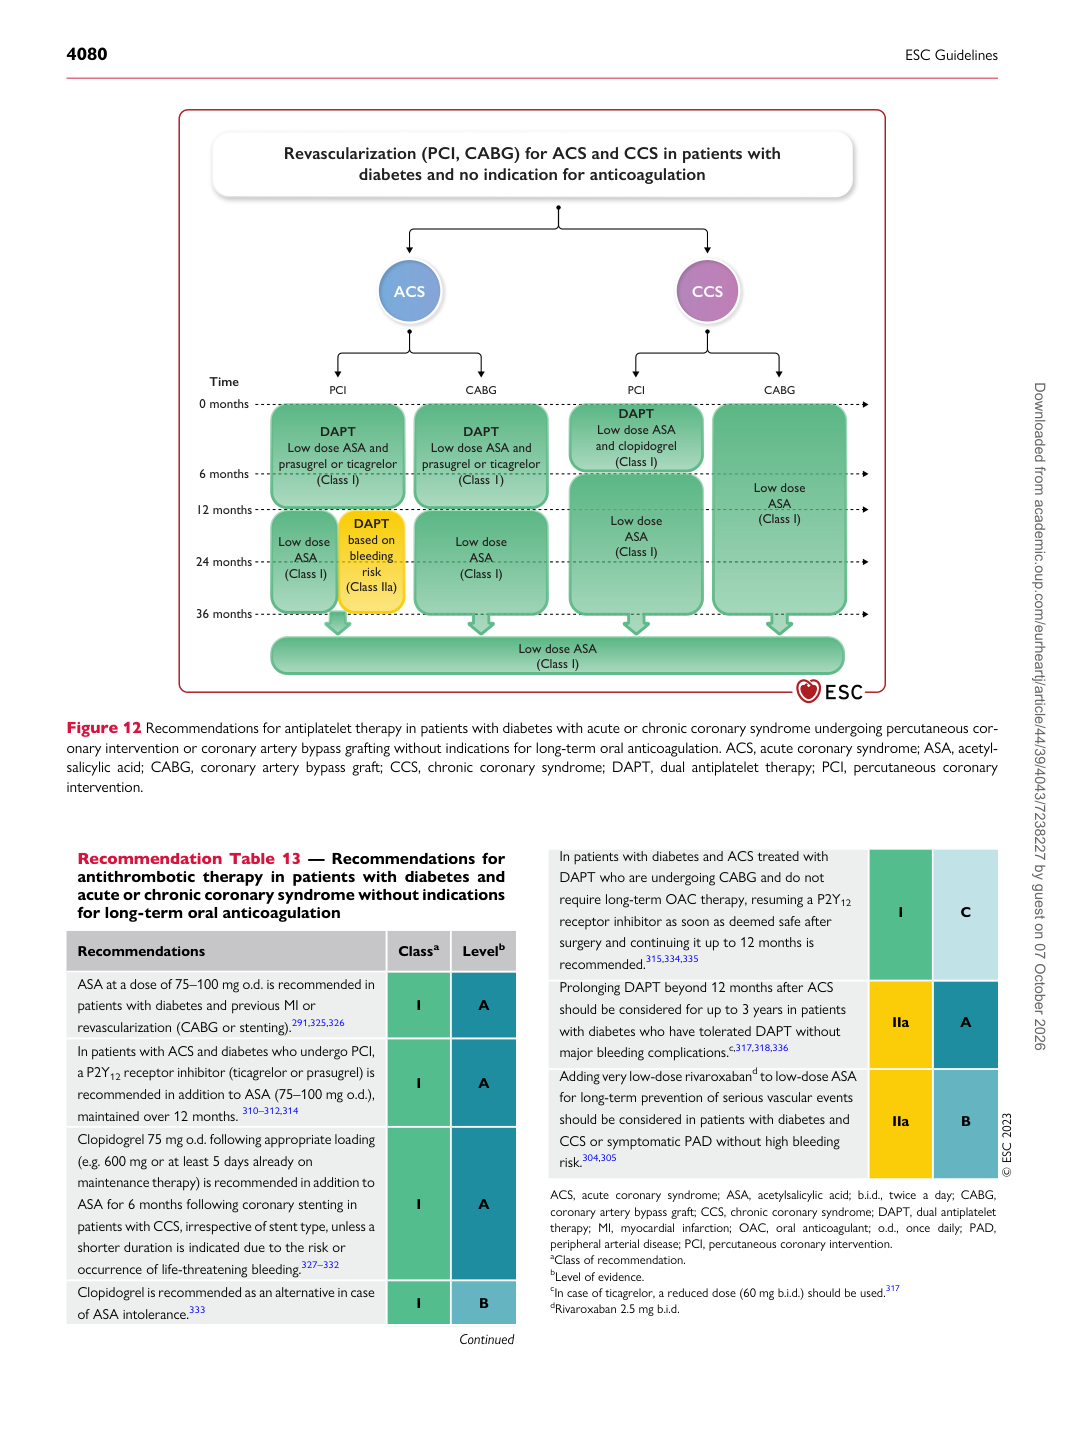
Figure 12 Recommendations for antiplatelet therapy in patients with diabetes with acute or chronic coronary syndrome undergoing percutaneous coronary intervention or coronary artery bypass grafting without indications for long-term oral anticoagulation. ACS, acute coronary syndrome; ASA, acetylsalicylic acid; CABG, coronary artery bypass graft; CCS, chronic coronary syndrome; DAPT, dual antiplatelet therapy; PCI, percutaneous coronary intervention.

Recommendation Table 13 — Recommendations for antithrombotic therapy in patients with diabetes and acute or chronic coronary syndrome without indications for long-term oral anticoagulation

Recommendations Classa Levelb

ASA at a dose of 75–100 mg o.d. is recommended in patients with diabetes and previous MI or revascularization (CABG or stenting).291,325,326 I A In patients with ACS and diabetes who undergo PCI, a P2Y12 receptor inhibitor (ticagrelor or prasugrel) is recommended in addition to ASA (75–100 mg o.d.), maintained over 12 months. 310–312,314 I A Clopidogrel 75 mg o.d. following appropriate loading (e.g. 600 mg or at least 5 days already on maintenance therapy) is recommended in addition to ASA for 6 months following coronary stenting in patients with CCS, irrespective of stent type, unless a shorter duration is indicated due to the risk or occurrence of life-threatening bleeding.327–332 I A Clopidogrel is recommended as an alternative in case of ASA intolerance.333 I B

Continued In patients with diabetes and ACS treated with DAPT who are undergoing CABG and do not

require long-term OAC therapy, resuming a P2Y12 receptor inhibitor as soon as deemed safe after surgery and continuing it up to 12 months is recommended.315,334,335 I C Prolonging DAPT beyond 12 months after ACS should be considered for up to 3 years in patients with diabetes who have tolerated DAPT without major bleeding complications.c,317,318,336 IIa A Adding very low-dose rivaroxaband to low-dose ASA for long-term prevention of serious vascular events should be considered in patients with diabetes and CCS or symptomatic PAD without high bleeding risk.304,305 IIa B © ESC 2023 ACS, acute coronary syndrome; ASA, acetylsalicylic acid; b.i.d., twice a day; CABG, coronary artery bypass graft; CCS, chronic coronary syndrome; DAPT, dual antiplatelet therapy; MI, myocardial infarction; OAC, oral anticoagulant; o.d., once daily; PAD, peripheral arterial disease; PCI, percutaneous coronary intervention. aClass of recommendation. bLevel of evidence. cIn case of ticagrelor, a reduced dose (60 mg b.i.d.) should be used.317 dRivaroxaban 2.5 mg b.i.d. Downloaded from academic.oup.com/eurheartj/article/44/39/4043/7238227 by guest on 07 October 2026