p.93 抽出テキスト
17 Supplementary data

Supplementary material is available at European Heart Journal online.

18 Data availability statement

No new data were generated or analysed in support of this research.

19 Author information

Author/Task Force Member Affiliations: Alexandros Protonotarios, Centre for Heart Muscle Disease, UCL Institute of Cardiovascular Science, London, United Kingdom, Inherited Cardiovascular Disease Unit, St Bartholomew’s Hospital, London, United Kingdom; Juan R. Gimeno, Inherited Heart Diseases Unit (CSUR /ERN), Hospital Universitario Virgen de la Arrixaca- IMIB- Universidad de Murcia, Murcia, Spain, European Reference Networks for rare, low prevalence and complex diseases of the heart, ERN GUARD-Heart, European Commission 6, Amsterdam, Netherlands; Eloisa Arbustini, Centre For Inherited Cardiovascular Diseases, IRCCS Foundation Policlinico San Matteo, Piazzale Golgi, 27100 Pavia, Italy; Roberto Barriales-Villa, Inherited Cardiovascular Diseases Unit, Cardiology Service, Complexo Hospitalario Universitario A Coruña (CHUAC), A Coruña, Spain, Instituto de Investigación Biomédica de A Coruña (INIBIC), Servizo Galego de Saúde (SERGAS), Universidade da Coruña, A Coruña, Spain, Centro de Investigación Biomédica en Red de Enfermedades Cardiovasculares, Instituto de Salud Carlos III, A Coruña, Spain; Cristina Basso, Department of Cardiac, Thoracic, Vascular Sciences and Public Health-University of Padua, Cardiovascular Pathology Unit-Azienda Ospedaliera, Padua, Italy; Connie R. Bezzina, Amsterdam UMC location University of Amsterdam, Department of experimental cardiology, Heart centre, Meibergdreef 9, Amsterdam, Netherlands, Amsterdam cardiovascular sciences, Heart failure and arrhythmias, Amsterdam, Netherlands, European Reference Networks for rare, low prevalence and complex diseases of the heart, ERN GUARD-Heart; Elena Biagini, Cardiology, IRCCS, Azienda Ospedaliero-Universitaria di Bologna, Bologna, Italy, Cardiology, Centro di riferimento europeo delle malattie cardiovascolari, ERN GUARD-Heart, Bologna, Italy; Nico A. Blom, Paediatric Cardiology, Leiden University Medical Center, Leiden, Netherlands, Paediatric Cardiology, Amsterdam University Medical Center, Amsterdam, Netherlands; Rudolf A. de Boer, Erasmus Medical

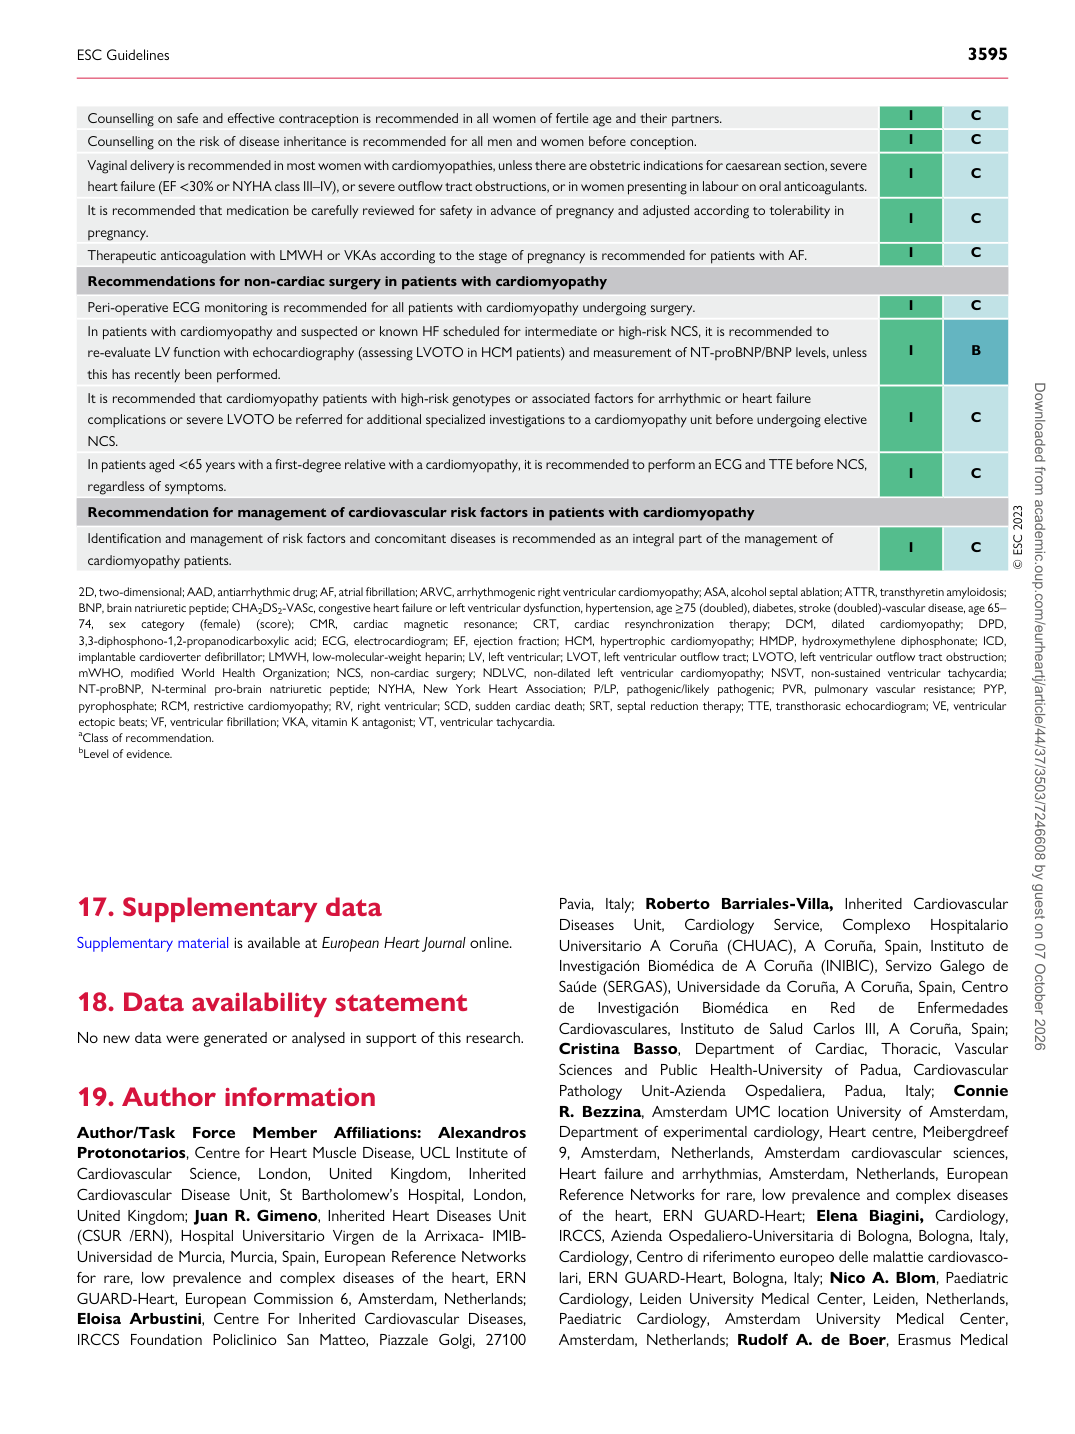
Counselling on safe and effective contraception is recommended in all women of fertile age and their partners. I C Counselling on the risk of disease inheritance is recommended for all men and women before conception. I C Vaginal delivery is recommended in most women with cardiomyopathies, unless there are obstetric indications for caesarean section, severe heart failure (EF <30% or NYHA class III–IV), or severe outflow tract obstructions, or in women presenting in labour on oral anticoagulants. I C It is recommended that medication be carefully reviewed for safety in advance of pregnancy and adjusted according to tolerability in pregnancy. I C Therapeutic anticoagulation with LMWH or VKAs according to the stage of pregnancy is recommended for patients with AF. I C Recommendations for non-cardiac surgery in patients with cardiomyopathy Peri-operative ECG monitoring is recommended for all patients with cardiomyopathy undergoing surgery. I C In patients with cardiomyopathy and suspected or known HF scheduled for intermediate or high-risk NCS, it is recommended to re-evaluate LV function with echocardiography (assessing LVOTO in HCM patients) and measurement of NT-proBNP/BNP levels, unless this has recently been performed. I B It is recommended that cardiomyopathy patients with high-risk genotypes or associated factors for arrhythmic or heart failure complications or severe LVOTO be referred for additional specialized investigations to a cardiomyopathy unit before undergoing elective NCS. I C In patients aged <65 years with a first-degree relative with a cardiomyopathy, it is recommended to perform an ECG and TTE before NCS, regardless of symptoms. I C Recommendation for management of cardiovascular risk factors in patients with cardiomyopathy Identification and management of risk factors and concomitant diseases is recommended as an integral part of the management of cardiomyopathy patients. I C © ESC 2023

2D, two-dimensional; AAD, antiarrhythmic drug; AF, atrial fibrillation; ARVC, arrhythmogenic right ventricular cardiomyopathy; ASA, alcohol septal ablation; ATTR, transthyretin amyloidosis; BNP, brain natriuretic peptide; CHA2DS2-VASc, congestive heart failure or left ventricular dysfunction, hypertension, age ≥75 (doubled), diabetes, stroke (doubled)-vascular disease, age 65– 74, sex category (female) (score); CMR, cardiac magnetic resonance; CRT, cardiac resynchronization therapy; DCM, dilated cardiomyopathy; DPD, 3,3-diphosphono-1,2-propanodicarboxylic acid; ECG, electrocardiogram; EF, ejection fraction; HCM, hypertrophic cardiomyopathy; HMDP, hydroxymethylene diphosphonate; ICD, implantable cardioverter defibrillator; LMWH, low-molecular-weight heparin; LV, left ventricular; LVOT, left ventricular outflow tract; LVOTO, left ventricular outflow tract obstruction; mWHO, modified World Health Organization; NCS, non-cardiac surgery; NDLVC, non-dilated left ventricular cardiomyopathy; NSVT, non-sustained ventricular tachycardia; NT-proBNP, N-terminal pro-brain natriuretic peptide; NYHA, New York Heart Association; P/LP, pathogenic/likely pathogenic; PVR, pulmonary vascular resistance; PYP, pyrophosphate; RCM, restrictive cardiomyopathy; RV, right ventricular; SCD, sudden cardiac death; SRT, septal reduction therapy; TTE, transthorasic echocardiogram; VE, ventricular ectopic beats; VF, ventricular fibrillation; VKA, vitamin K antagonist; VT, ventricular tachycardia. aClass of recommendation. bLevel of evidence.

ESC Guidelines                                                                                                                                                                                          3595

Downloaded from academic.oup.com/eurheartj/article/44/37/3503/7246608 by guest on 07 October 2026