p.92 抽出テキスト
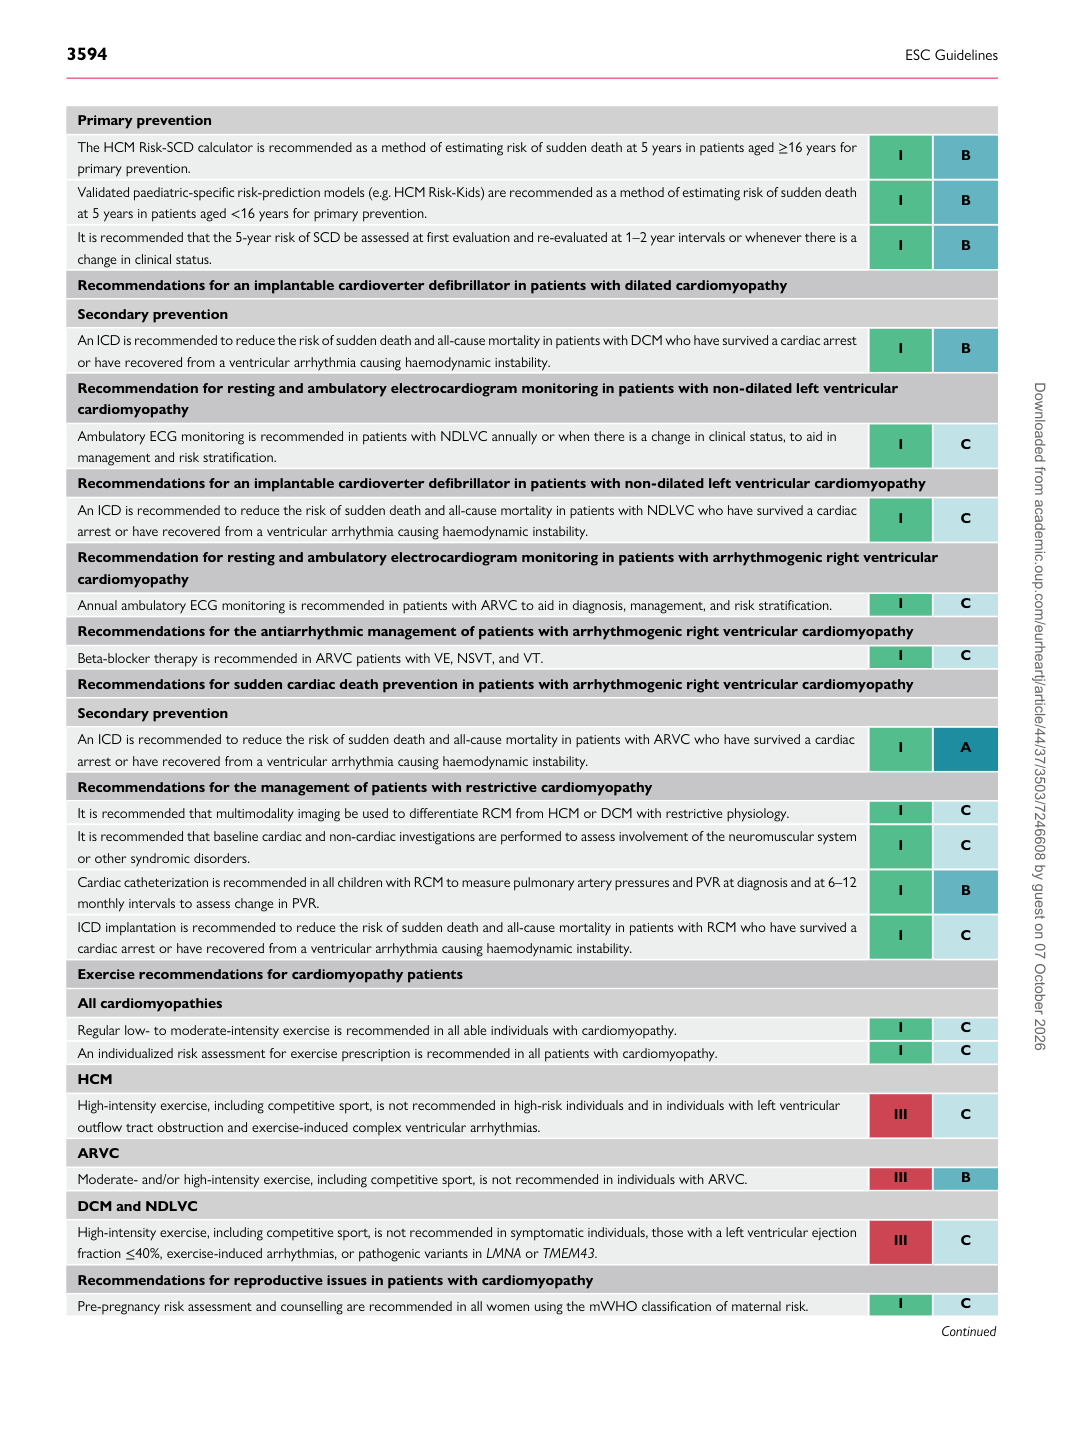
Primary prevention The HCM Risk-SCD calculator is recommended as a method of estimating risk of sudden death at 5 years in patients aged ≥16 years for primary prevention. I B Validated paediatric-specific risk-prediction models (e.g. HCM Risk-Kids) are recommended as a method of estimating risk of sudden death at 5 years in patients aged <16 years for primary prevention. I B It is recommended that the 5-year risk of SCD be assessed at first evaluation and re-evaluated at 1–2 year intervals or whenever there is a change in clinical status. I B Recommendations for an implantable cardioverter defibrillator in patients with dilated cardiomyopathy Secondary prevention An ICD is recommended to reduce the risk of sudden death and all-cause mortality in patients with DCM who have survived a cardiac arrest or have recovered from a ventricular arrhythmia causing haemodynamic instability. I B Recommendation for resting and ambulatory electrocardiogram monitoring in patients with non-dilated left ventricular cardiomyopathy Ambulatory ECG monitoring is recommended in patients with NDLVC annually or when there is a change in clinical status, to aid in management and risk stratification. I C Recommendations for an implantable cardioverter defibrillator in patients with non-dilated left ventricular cardiomyopathy An ICD is recommended to reduce the risk of sudden death and all-cause mortality in patients with NDLVC who have survived a cardiac arrest or have recovered from a ventricular arrhythmia causing haemodynamic instability. I C Recommendation for resting and ambulatory electrocardiogram monitoring in patients with arrhythmogenic right ventricular cardiomyopathy Annual ambulatory ECG monitoring is recommended in patients with ARVC to aid in diagnosis, management, and risk stratification. I C Recommendations for the antiarrhythmic management of patients with arrhythmogenic right ventricular cardiomyopathy Beta-blocker therapy is recommended in ARVC patients with VE, NSVT, and VT. I C Recommendations for sudden cardiac death prevention in patients with arrhythmogenic right ventricular cardiomyopathy Secondary prevention An ICD is recommended to reduce the risk of sudden death and all-cause mortality in patients with ARVC who have survived a cardiac arrest or have recovered from a ventricular arrhythmia causing haemodynamic instability. I A Recommendations for the management of patients with restrictive cardiomyopathy It is recommended that multimodality imaging be used to differentiate RCM from HCM or DCM with restrictive physiology. I C It is recommended that baseline cardiac and non-cardiac investigations are performed to assess involvement of the neuromuscular system or other syndromic disorders. I C Cardiac catheterization is recommended in all children with RCM to measure pulmonary artery pressures and PVR at diagnosis and at 6–12 monthly intervals to assess change in PVR. I B ICD implantation is recommended to reduce the risk of sudden death and all-cause mortality in patients with RCM who have survived a cardiac arrest or have recovered from a ventricular arrhythmia causing haemodynamic instability. I C Exercise recommendations for cardiomyopathy patients All cardiomyopathies Regular low- to moderate-intensity exercise is recommended in all able individuals with cardiomyopathy. I C An individualized risk assessment for exercise prescription is recommended in all patients with cardiomyopathy. I C HCM High-intensity exercise, including competitive sport, is not recommended in high-risk individuals and in individuals with left ventricular outflow tract obstruction and exercise-induced complex ventricular arrhythmias. III C ARVC Moderate- and/or high-intensity exercise, including competitive sport, is not recommended in individuals with ARVC. III B DCM and NDLVC High-intensity exercise, including competitive sport, is not recommended in symptomatic individuals, those with a left ventricular ejection fraction ≤40%, exercise-induced arrhythmias, or pathogenic variants in LMNA or TMEM43. III C Recommendations for reproductive issues in patients with cardiomyopathy Pre-pregnancy risk assessment and counselling are recommended in all women using the mWHO classification of maternal risk. I C

Continued Downloaded from academic.oup.com/eurheartj/article/44/37/3503/7246608 by guest on 07 October 2026