p.40 抽出テキスト
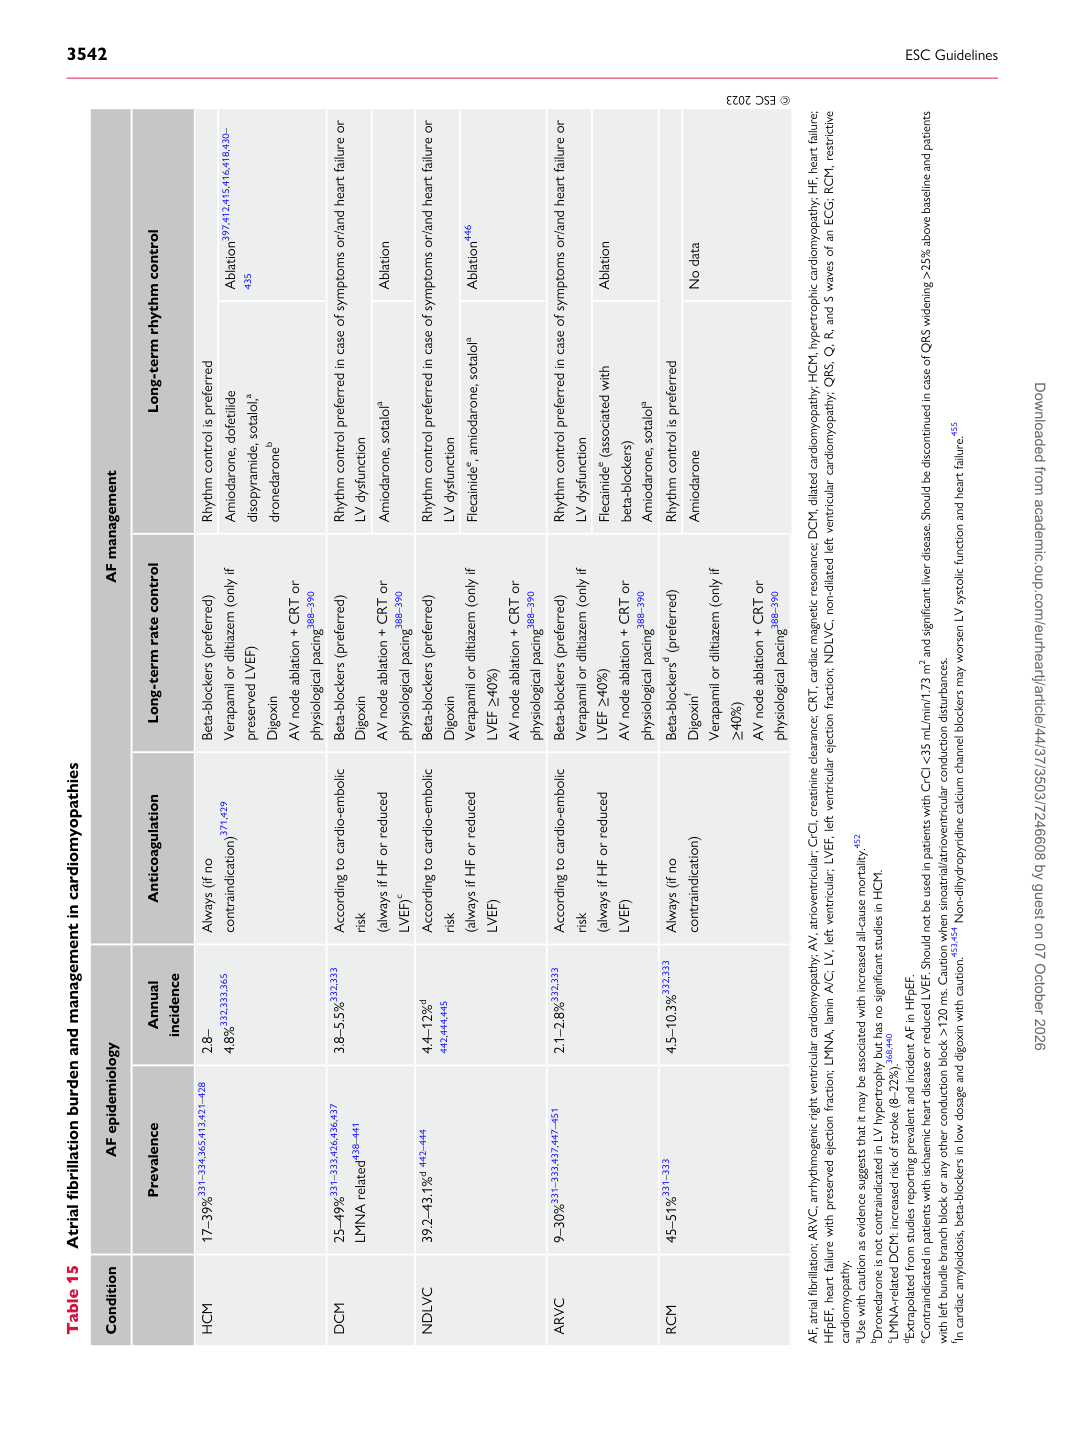
Table 15 Atrial fibrillation burden and management in cardiomyopathies Condition AF epidemiology AF management Prevalence Annual

incidence Anticoagulation Long-term rate control Long-term rhythm control HCM 17–39%331–334,365,413,421–428 2.8–

4.8%332,333,365 Always (if no

contraindication)371,429 Beta-blockers (preferred)

Verapamil or diltiazem (only if preserved LVEF) Digoxin AV node ablation + CRT or physiological pacing388–390

Rhythm control is preferred Amiodarone, dofetilide disopyramide, sotalol,a dronedaroneb

Ablation397,412,415,416,418,430– 435

DCM 25–49%331–333,426,436,437

LMNA related438–441 3.8–5.5%332,333 According to cardio-embolic

risk (always if HF or reduced LVEF)c

Beta-blockers (preferred) Digoxin AV node ablation + CRT or physiological pacing388–390

Rhythm control preferred in case of symptoms or/and heart failure or LV dysfunction Amiodarone, sotalola Ablation

NDLVC 39.2–43.1%d 442–444 4.4–12%d

442,444,445 According to cardio-embolic risk (always if HF or reduced LVEF)

Beta-blockers (preferred) Digoxin Verapamil or diltiazem (only if LVEF ≥40%) AV node ablation + CRT or physiological pacing388–390

Rhythm control preferred in case of symptoms or/and heart failure or LV dysfunction Flecainidee, amiodarone, sotalola Ablation446

ARVC 9–30%331–333,437,447–451 2.1–2.8%332,333 According to cardio-embolic risk (always if HF or reduced LVEF)

Beta-blockers (preferred) Verapamil or diltiazem (only if LVEF ≥40%) AV node ablation + CRT or physiological pacing388–390

Rhythm control preferred in case of symptoms or/and heart failure or LV dysfunction Flecainidee (associated with beta-blockers) Amiodarone, sotalola

Ablation

RCM 45–51%331–333 4.5–10.3%332,333 Always (if no contraindication)

Beta-blockersd (preferred) Digoxinf Verapamil or diltiazem (only if ≥40%) AV node ablation + CRT or physiological pacing388–390

Rhythm control is preferred Amiodarone No data AF, atrial fibrillation; ARVC, arrhythmogenic right ventricular cardiomyopathy; AV, atrioventricular; CrCl, creatinine clearance; CRT, cardiac magnetic resonance; DCM, dilated cardiomyopathy; HCM, hypertrophic cardiomyopathy; HF, heart failure; HFpEF, heart failure with preserved ejection fraction; LMNA, lamin A/C; LV, left ventricular; LVEF, left ventricular ejection fraction; NDLVC, non-dilated left ventricular cardiomyopathy; QRS, Q, R, and S waves of an ECG; RCM, restrictive cardiomyopathy. aUse with caution as evidence suggests that it may be associated with increased all-cause mortality.452 bDronedarone is not contraindicated in LV hypertrophy but has no significant studies in HCM. cLMNA-related DCM: increased risk of stroke (8–22%).368,440 dExtrapolated from studies reporting prevalent and incident AF in HFpEF. eContraindicated in patients with ischaemic heart disease or reduced LVEF. Should not be used in patients with CrCl <35 mL/min/1.73 m2 and significant liver disease. Should be discontinued in case of QRS widening >25% above baseline and patients with left bundle branch block or any other conduction block >120 ms. Caution when sinoatrial/atrioventricular conduction disturbances. fIn cardiac amyloidosis, beta-blockers in low dosage and digoxin with caution.453,454 Non-dihydropyridine calcium channel blockers may worsen LV systolic function and heart failure.455 Downloaded from academic.oup.com/eurheartj/article/44/37/3503/7246608 by guest on 07 October 2026