p.78 抽出テキスト
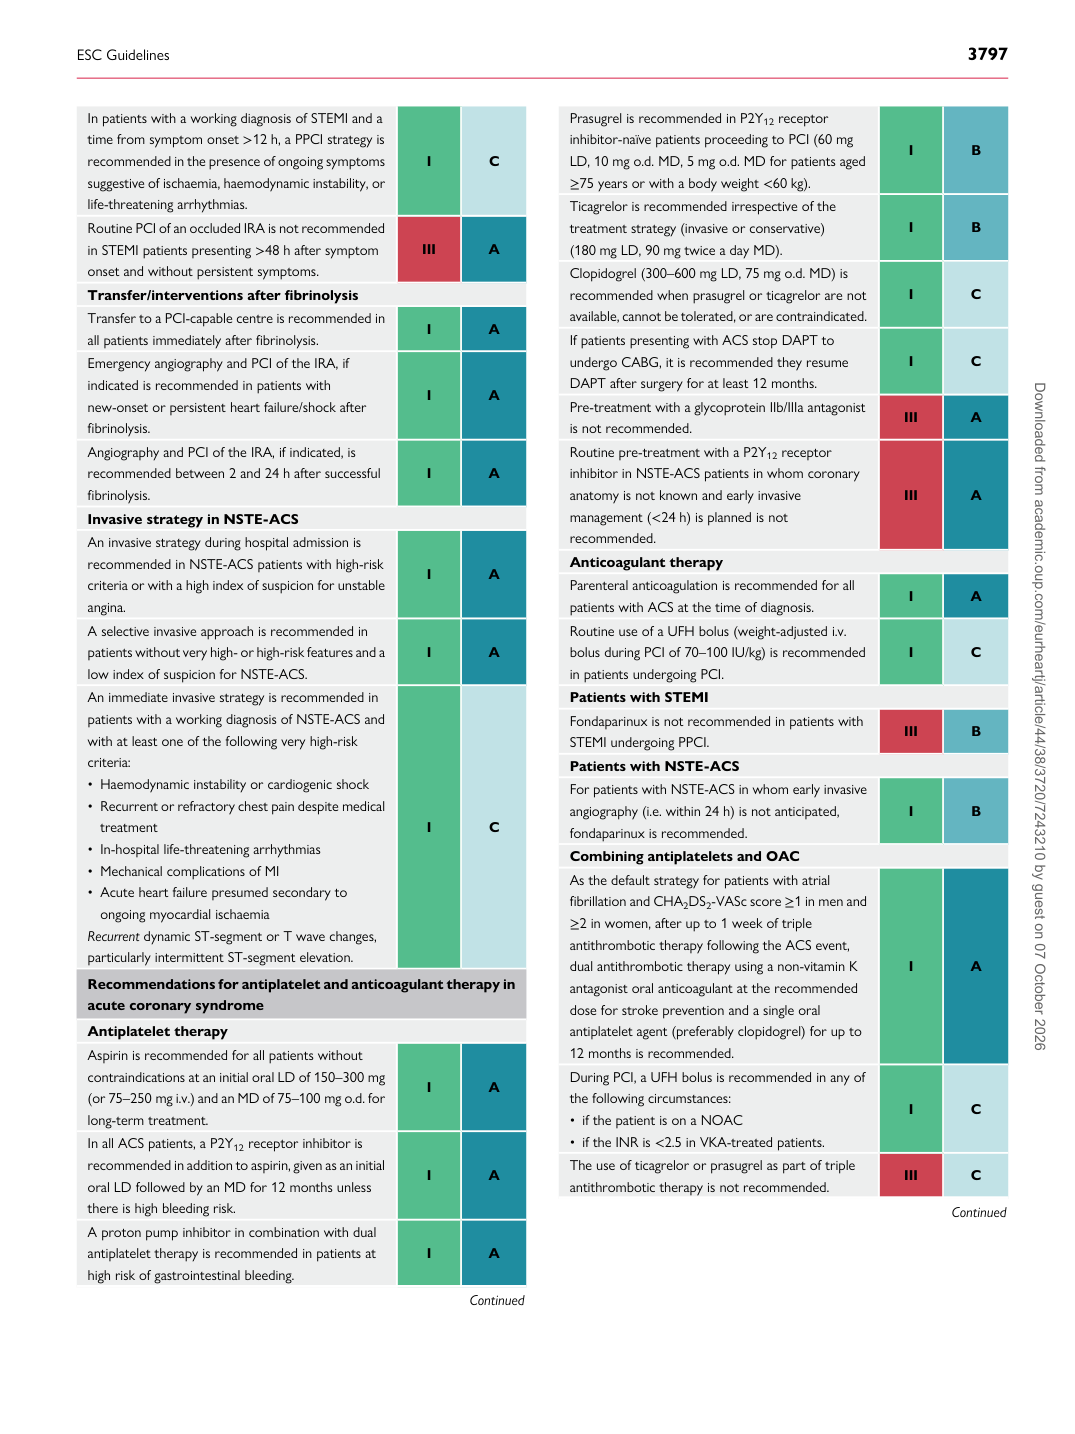
In patients with a working diagnosis of STEMI and a time from symptom onset >12 h, a PPCI strategy is recommended in the presence of ongoing symptoms suggestive of ischaemia, haemodynamic instability, or life-threatening arrhythmias. I C Routine PCI of an occluded IRA is not recommended in STEMI patients presenting >48 h after symptom onset and without persistent symptoms. III A Transfer/interventions after fibrinolysis Transfer to a PCI-capable centre is recommended in all patients immediately after fibrinolysis. I A Emergency angiography and PCI of the IRA, if indicated is recommended in patients with new-onset or persistent heart failure/shock after fibrinolysis. I A Angiography and PCI of the IRA, if indicated, is recommended between 2 and 24 h after successful fibrinolysis. I A Invasive strategy in NSTE-ACS An invasive strategy during hospital admission is recommended in NSTE-ACS patients with high-risk criteria or with a high index of suspicion for unstable angina. I A A selective invasive approach is recommended in patients without very high- or high-risk features and a low index of suspicion for NSTE-ACS. I A An immediate invasive strategy is recommended in patients with a working diagnosis of NSTE-ACS and with at least one of the following very high-risk criteria: • Haemodynamic instability or cardiogenic shock • Recurrent or refractory chest pain despite medical treatment • In-hospital life-threatening arrhythmias • Mechanical complications of MI • Acute heart failure presumed secondary to

ongoing myocardial ischaemia Recurrent dynamic ST-segment or T wave changes, particularly intermittent ST-segment elevation. I C Recommendations for antiplatelet and anticoagulant therapy in acute coronary syndrome Antiplatelet therapy Aspirin is recommended for all patients without contraindications at an initial oral LD of 150–300 mg (or 75–250 mg i.v.) and an MD of 75–100 mg o.d. for long-term treatment. I A In all ACS patients, a P2Y12 receptor inhibitor is recommended in addition to aspirin, given as an initial oral LD followed by an MD for 12 months unless there is high bleeding risk. I A A proton pump inhibitor in combination with dual antiplatelet therapy is recommended in patients at high risk of gastrointestinal bleeding. I A

Continued Prasugrel is recommended in P2Y12 receptor

inhibitor-naïve patients proceeding to PCI (60 mg LD, 10 mg o.d. MD, 5 mg o.d. MD for patients aged ≥75 years or with a body weight <60 kg). I B Ticagrelor is recommended irrespective of the treatment strategy (invasive or conservative) (180 mg LD, 90 mg twice a day MD). I B Clopidogrel (300–600 mg LD, 75 mg o.d. MD) is recommended when prasugrel or ticagrelor are not available, cannot be tolerated, or are contraindicated. I C If patients presenting with ACS stop DAPT to undergo CABG, it is recommended they resume DAPT after surgery for at least 12 months. I C Pre-treatment with a glycoprotein IIb/IIIa antagonist is not recommended. III A Routine pre-treatment with a P2Y12 receptor inhibitor in NSTE-ACS patients in whom coronary anatomy is not known and early invasive management (<24 h) is planned is not recommended. III A Anticoagulant therapy Parenteral anticoagulation is recommended for all patients with ACS at the time of diagnosis. I A Routine use of a UFH bolus (weight-adjusted i.v. bolus during PCI of 70–100 IU/kg) is recommended in patients undergoing PCI. I C Patients with STEMI Fondaparinux is not recommended in patients with STEMI undergoing PPCI. III B Patients with NSTE-ACS For patients with NSTE-ACS in whom early invasive angiography (i.e. within 24 h) is not anticipated, fondaparinux is recommended. I B Combining antiplatelets and OAC As the default strategy for patients with atrial fibrillation and CHA2DS2-VASc score ≥1 in men and ≥2 in women, after up to 1 week of triple antithrombotic therapy following the ACS event, dual antithrombotic therapy using a non-vitamin K antagonist oral anticoagulant at the recommended dose for stroke prevention and a single oral antiplatelet agent (preferably clopidogrel) for up to 12 months is recommended. I A During PCI, a UFH bolus is recommended in any of the following circumstances: • if the patient is on a NOAC • if the INR is <2.5 in VKA-treated patients. I C The use of ticagrelor or prasugrel as part of triple antithrombotic therapy is not recommended. III C

Continued

ESC Guidelines                                                                                                                                                                                          3797

Downloaded from academic.oup.com/eurheartj/article/44/38/3720/7243210 by guest on 07 October 2026