p.66 抽出テキスト
13.3.3 Beta-blockers

The clinical benefit of beta-blockers after ACS in patients with reduced LVEF is supported by evidence from contemporary trials.557,798–800 However, the evidence for prescribing beta-blockers after uncomplicated ACS in patients with LVEF >40% is less well established. With the exception of the CAPRICORN (CArvedilol Post-infaRct survIval COntRolled evaluatioN) trial, which only recruited patients with LVEF ≤40%, all large RCTs testing the benefits of post-MI beta-blocker maintenance were performed in the pre-reperfusion era.801 Pooled data demonstrated that post-MI beta-blocker therapy reduced the

Prior treatment

LDL-C <1.4 mmol/L

or 55 mg/dLa Add ezetimibe

(Class I)

LDL-C <1.4 mmol/L

or 55 mg/dLa

LDL-C <1.4 mmol/L

or 55 mg/dLa

On highest tolerated statin and ezetimibe,

add PCSK9i

(Class I)

LDL-C <1.4 mmol/L

or 55 mg/dLa

Lipid lowering therapy in ACS patients

Y

Y N

N

N

No change in therapy

No change in therapy

Y

No change in therapy Y

No change in therapy Add PCSK9i (Class I)

N

LLT-naive, irrespective of LDL-C values

Initiate high-potency high-dose statin

(Class I) Combination therapy with statin and

ezetimibe (Class IIb) Change to high-potency high-dose statin

(Class I)

On low-potency/ low-dose statin, irrespective of LDL-C values On highest tolerated statin On highest tolerated

statin and ezetimibe

Combination therapy with statin and

ezetimibe (Class IIb)

On highest tolerated statin,

add ezetimibe

(Class I) On highest tolerated statin and ezetimibe, add PCSK9i

(Class I)

During admission

Outpatient follow-up After 4–6 weeks

After further 4–6 weeks

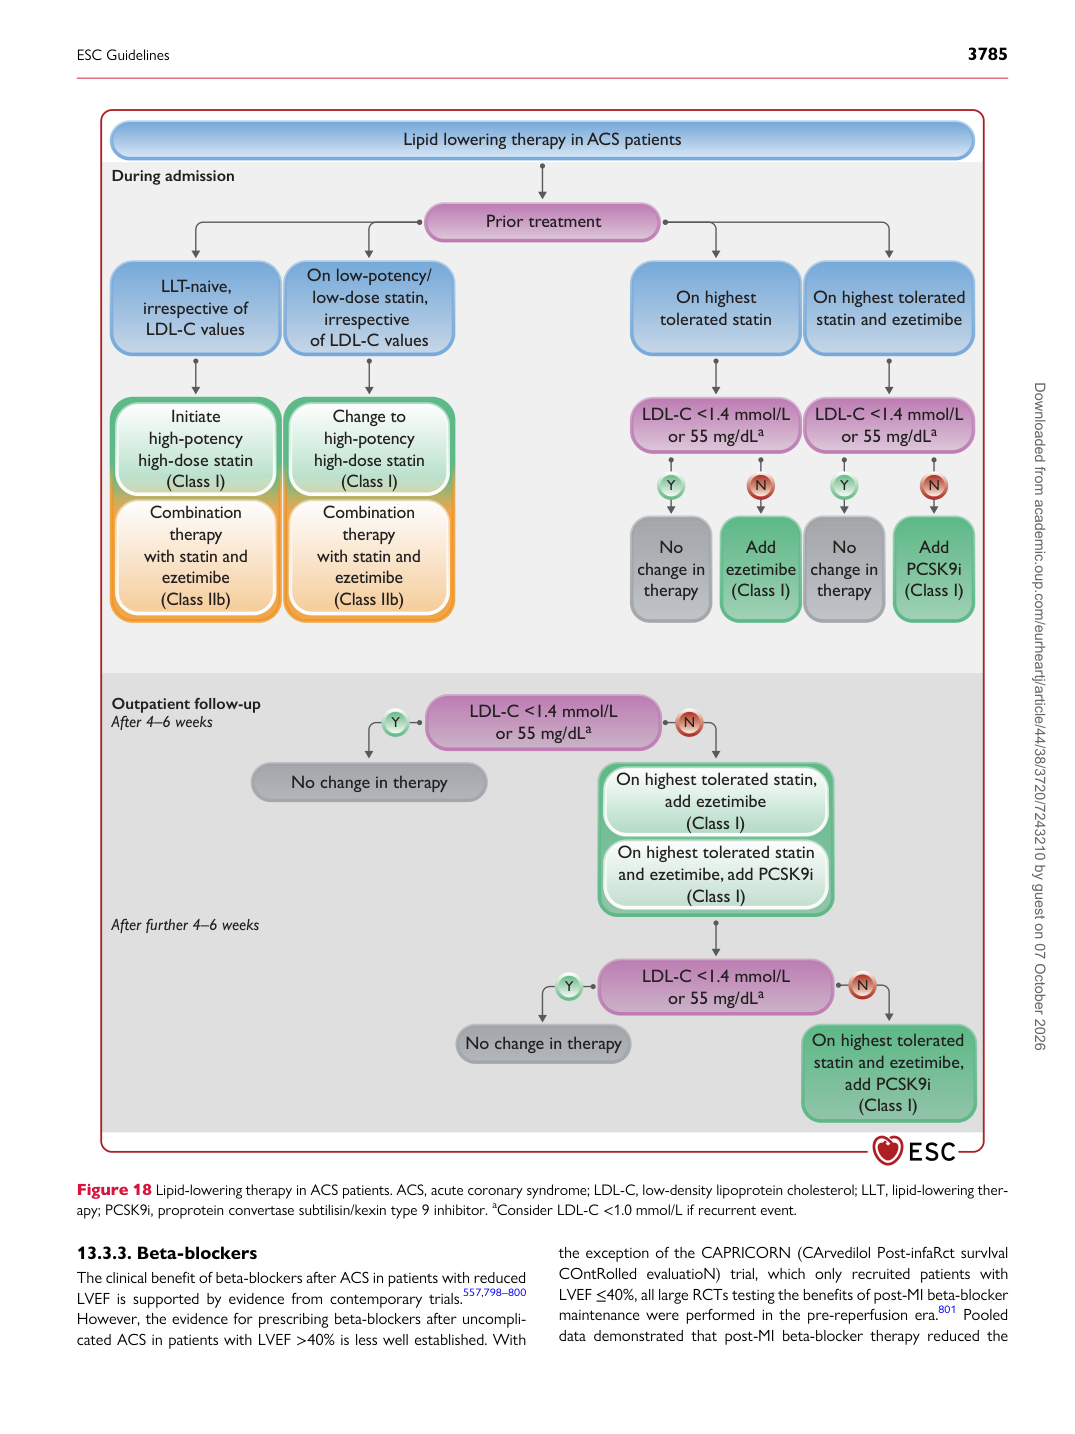
Figure 18 Lipid-lowering therapy in ACS patients. ACS, acute coronary syndrome; LDL-C, low-density lipoprotein cholesterol; LLT, lipid-lowering therapy; PCSK9i, proprotein convertase subtilisin/kexin type 9 inhibitor. aConsider LDL-C <1.0 mmol/L if recurrent event.

ESC Guidelines                                                                                                                                                                                          3785

Downloaded from academic.oup.com/eurheartj/article/44/38/3720/7243210 by guest on 07 October 2026