p.39 抽出テキスト
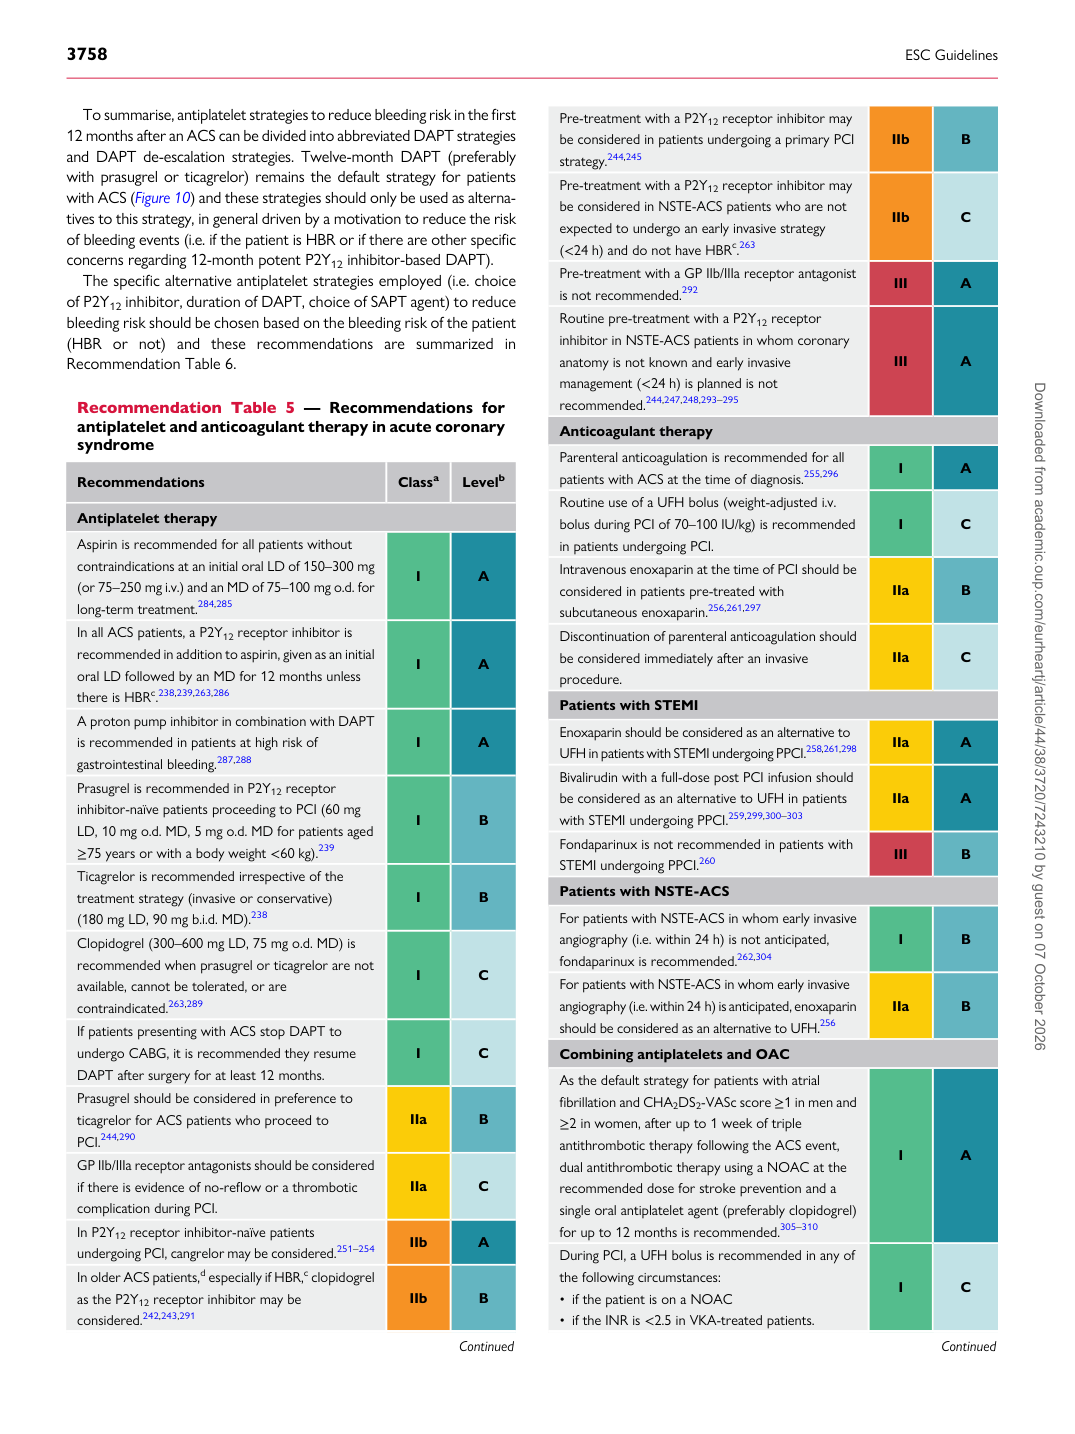
To summarise, antiplatelet strategies to reduce bleeding risk in the first 12 months after an ACS can be divided into abbreviated DAPT strategies and DAPT de-escalation strategies. Twelve-month DAPT (preferably with prasugrel or ticagrelor) remains the default strategy for patients with ACS (Figure 10) and these strategies should only be used as alternatives to this strategy, in general driven by a motivation to reduce the risk of bleeding events (i.e. if the patient is HBR or if there are other specific concerns regarding 12-month potent P2Y12 inhibitor-based DAPT). The specific alternative antiplatelet strategies employed (i.e. choice of P2Y12 inhibitor, duration of DAPT, choice of SAPT agent) to reduce bleeding risk should be chosen based on the bleeding risk of the patient (HBR or not) and these recommendations are summarized in Recommendation Table 6.

Recommendation Table 5 — Recommendations for antiplatelet and anticoagulant therapy in acute coronary syndrome

Recommendations Classa Levelb

Antiplatelet therapy Aspirin is recommended for all patients without contraindications at an initial oral LD of 150–300 mg (or 75–250 mg i.v.) and an MD of 75–100 mg o.d. for long-term treatment.284,285 I A In all ACS patients, a P2Y12 receptor inhibitor is recommended in addition to aspirin, given as an initial oral LD followed by an MD for 12 months unless there is HBRc.238,239,263,286 I A A proton pump inhibitor in combination with DAPT is recommended in patients at high risk of gastrointestinal bleeding.287,288 I A Prasugrel is recommended in P2Y12 receptor inhibitor-naïve patients proceeding to PCI (60 mg LD, 10 mg o.d. MD, 5 mg o.d. MD for patients aged ≥75 years or with a body weight <60 kg).239 I B Ticagrelor is recommended irrespective of the treatment strategy (invasive or conservative) (180 mg LD, 90 mg b.i.d. MD).238 I B Clopidogrel (300–600 mg LD, 75 mg o.d. MD) is recommended when prasugrel or ticagrelor are not available, cannot be tolerated, or are contraindicated.263,289 I C If patients presenting with ACS stop DAPT to undergo CABG, it is recommended they resume DAPT after surgery for at least 12 months. I C Prasugrel should be considered in preference to ticagrelor for ACS patients who proceed to PCI.244,290 IIa B GP IIb/IIIa receptor antagonists should be considered if there is evidence of no-reflow or a thrombotic complication during PCI. IIa C In P2Y12 receptor inhibitor-naïve patients undergoing PCI, cangrelor may be considered.251–254 IIb A In older ACS patients,d especially if HBR,c clopidogrel as the P2Y12 receptor inhibitor may be considered.242,243,291 IIb B

Continued Pre-treatment with a P2Y12 receptor inhibitor may

be considered in patients undergoing a primary PCI strategy.244,245 IIb B Pre-treatment with a P2Y12 receptor inhibitor may be considered in NSTE-ACS patients who are not expected to undergo an early invasive strategy (<24 h) and do not have HBRc.263 IIb C Pre-treatment with a GP IIb/IIIa receptor antagonist is not recommended.292 III A Routine pre-treatment with a P2Y12 receptor inhibitor in NSTE-ACS patients in whom coronary anatomy is not known and early invasive management (<24 h) is planned is not recommended.244,247,248,293–295 III A Anticoagulant therapy Parenteral anticoagulation is recommended for all patients with ACS at the time of diagnosis.255,296 I A Routine use of a UFH bolus (weight-adjusted i.v. bolus during PCI of 70–100 IU/kg) is recommended in patients undergoing PCI. I C Intravenous enoxaparin at the time of PCI should be considered in patients pre-treated with subcutaneous enoxaparin.256,261,297 IIa B Discontinuation of parenteral anticoagulation should be considered immediately after an invasive procedure. IIa C Patients with STEMI Enoxaparin should be considered as an alternative to UFH in patients with STEMI undergoing PPCI.258,261,298 IIa A Bivalirudin with a full-dose post PCI infusion should be considered as an alternative to UFH in patients with STEMI undergoing PPCI.259,299,300–303 IIa A Fondaparinux is not recommended in patients with STEMI undergoing PPCI.260 III B Patients with NSTE-ACS For patients with NSTE-ACS in whom early invasive angiography (i.e. within 24 h) is not anticipated, fondaparinux is recommended.262,304 I B For patients with NSTE-ACS in whom early invasive angiography (i.e. within 24 h) is anticipated, enoxaparin should be considered as an alternative to UFH.256 IIa B Combining antiplatelets and OAC As the default strategy for patients with atrial fibrillation and CHA2DS2-VASc score ≥1 in men and ≥2 in women, after up to 1 week of triple antithrombotic therapy following the ACS event, dual antithrombotic therapy using a NOAC at the recommended dose for stroke prevention and a single oral antiplatelet agent (preferably clopidogrel) for up to 12 months is recommended.305–310 I A During PCI, a UFH bolus is recommended in any of the following circumstances: • if the patient is on a NOAC • if the INR is <2.5 in VKA-treated patients. I C

Continued Downloaded from academic.oup.com/eurheartj/article/44/38/3720/7243210 by guest on 07 October 2026