p.36 抽出テキスト
6.3 Maintenance antithrombotic therapy

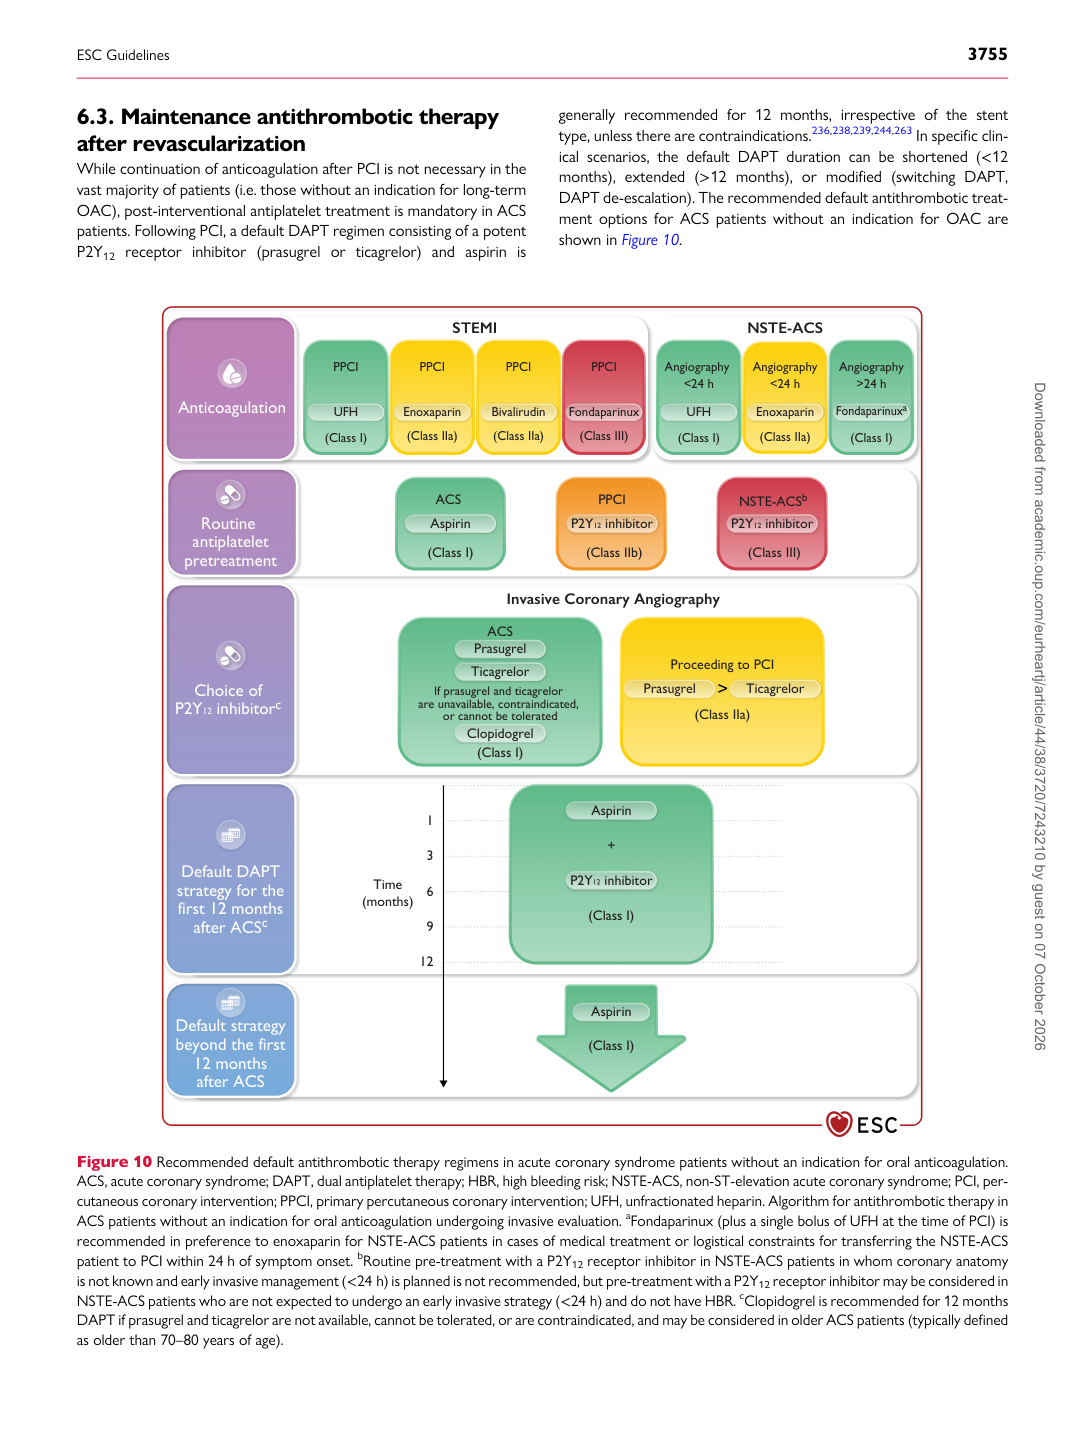
after revascularization While continuation of anticoagulation after PCI is not necessary in the vast majority of patients (i.e. those without an indication for long-term OAC), post-interventional antiplatelet treatment is mandatory in ACS patients. Following PCI, a default DAPT regimen consisting of a potent P2Y12 receptor inhibitor (prasugrel or ticagrelor) and aspirin is generally recommended for 12 months, irrespective of the stent type, unless there are contraindications.236,238,239,244,263 In specific clinical scenarios, the default DAPT duration can be shortened (<12 months), extended (>12 months), or modified (switching DAPT, DAPT de-escalation). The recommended default antithrombotic treatment options for ACS patients without an indication for OAC are shown in Figure 10.

Routine antiplatelet pretreatment ACS

(Class I) PPCI

(Class IIb)

ACS

+

(Class I)

(Class I) Proceeding to PCI

(Class IIa)

Prasugrel Ticagrelor >

NSTE-ACSb

(Class III)

Anticoagulation

Choice of P2Y12 inhibitorc

Default DAPT strategy for the first 12 months

after ACSc

Default strategy beyond the first

12 months after ACS Invasive Coronary Angiography

If prasugrel and ticagrelor are unavailable, contraindicated,

or cannot be tolerated Angiography

<24 h

(Class I)

UFH

PPCI

(Class IIa)

Enoxaparin PPCI

(Class III)

Fondaparinux

Aspirin

Aspirin

P2Y12 inhibitor

(Class I)

Aspirin

P2Y12 inhibitor

Prasugrel Ticagrelor

Clopidogrel P2Y12 inhibitor

1

3 6 Time (months)

9 12 NSTE-ACS STEMI

(Class IIa)

Enoxaparin

Angiography

<24 h

(Class I)

Fondaparinuxa

Angiography

>24 h

(Class I)

UFH

PPCI PPCI

(Class IIa)

Bivalirudin

Figure 10 Recommended default antithrombotic therapy regimens in acute coronary syndrome patients without an indication for oral anticoagulation. ACS, acute coronary syndrome; DAPT, dual antiplatelet therapy; HBR, high bleeding risk; NSTE-ACS, non-ST-elevation acute coronary syndrome; PCI, percutaneous coronary intervention; PPCI, primary percutaneous coronary intervention; UFH, unfractionated heparin. Algorithm for antithrombotic therapy in ACS patients without an indication for oral anticoagulation undergoing invasive evaluation. aFondaparinux (plus a single bolus of UFH at the time of PCI) is recommended in preference to enoxaparin for NSTE-ACS patients in cases of medical treatment or logistical constraints for transferring the NSTE-ACS patient to PCI within 24 h of symptom onset. bRoutine pre-treatment with a P2Y12 receptor inhibitor in NSTE-ACS patients in whom coronary anatomy is not known and early invasive management (<24 h) is planned is not recommended, but pre-treatment with a P2Y12 receptor inhibitor may be considered in NSTE-ACS patients who are not expected to undergo an early invasive strategy (<24 h) and do not have HBR. cClopidogrel is recommended for 12 months DAPT if prasugrel and ticagrelor are not available, cannot be tolerated, or are contraindicated, and may be considered in older ACS patients (typically defined as older than 70–80 years of age).

ESC Guidelines                                                                                                                                                                                          3755

Downloaded from academic.oup.com/eurheartj/article/44/38/3720/7243210 by guest on 07 October 2026