p.32 抽出テキスト
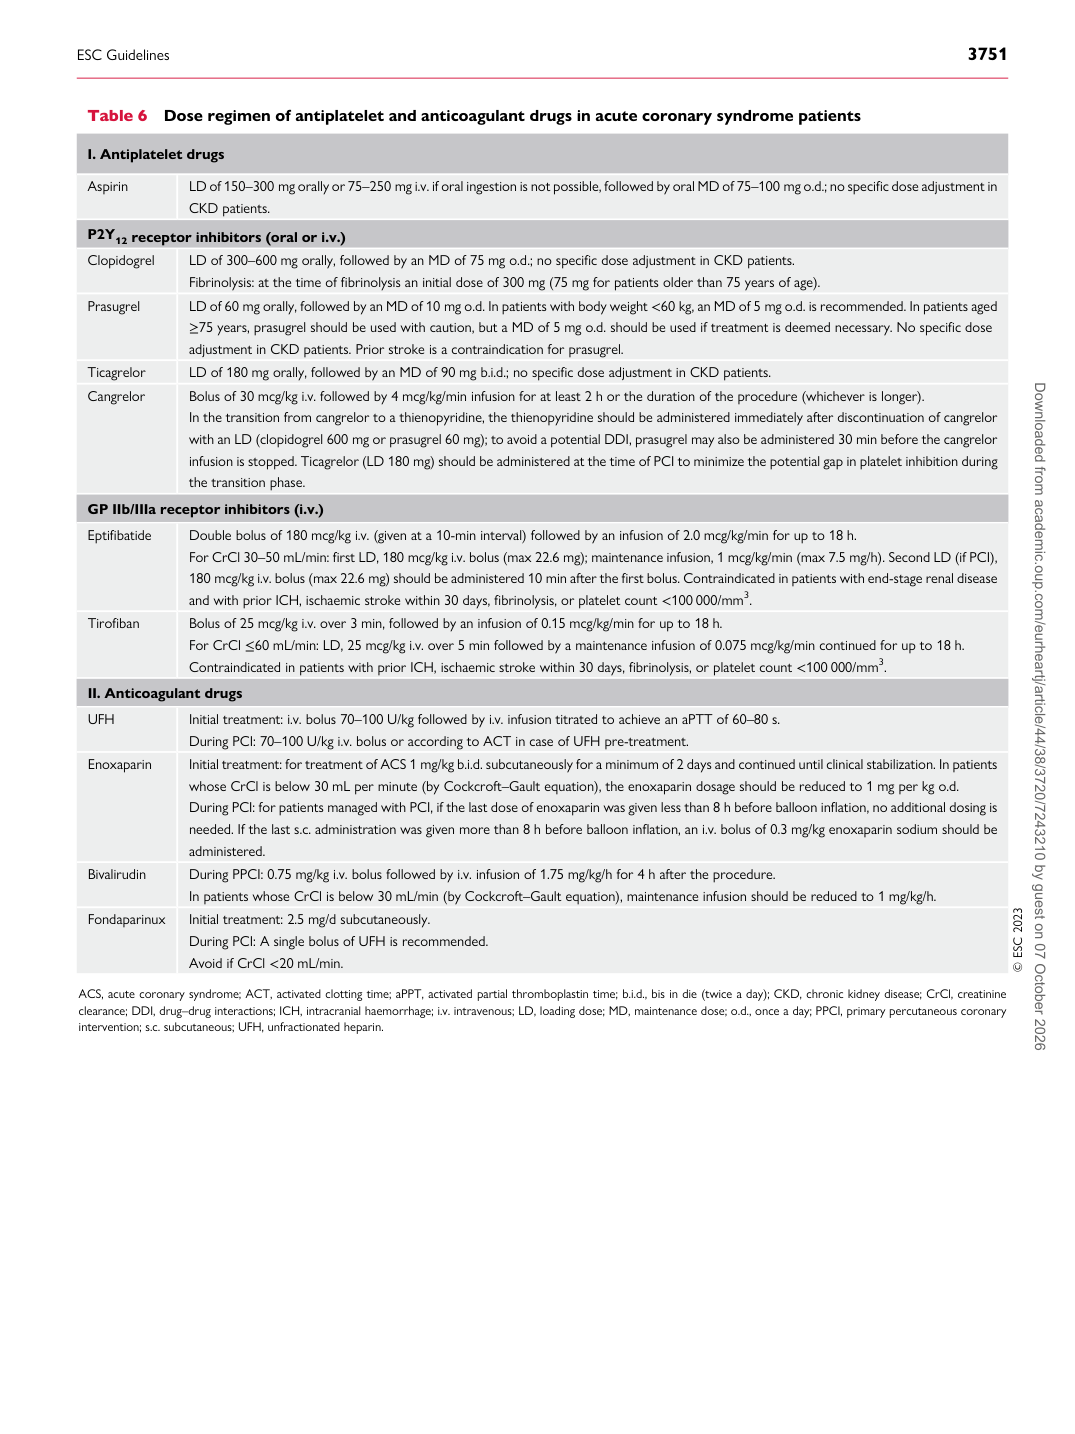
Table 6 Dose regimen of antiplatelet and anticoagulant drugs in acute coronary syndrome patients

I. Antiplatelet drugs

Aspirin LD of 150–300 mg orally or 75–250 mg i.v. if oral ingestion is not possible, followed by oral MD of 75–100 mg o.d.; no specific dose adjustment in CKD patients. P2Y12 receptor inhibitors (oral or i.v.) Clopidogrel LD of 300–600 mg orally, followed by an MD of 75 mg o.d.; no specific dose adjustment in CKD patients.

Fibrinolysis: at the time of fibrinolysis an initial dose of 300 mg (75 mg for patients older than 75 years of age).

Prasugrel LD of 60 mg orally, followed by an MD of 10 mg o.d. In patients with body weight <60 kg, an MD of 5 mg o.d. is recommended. In patients aged

≥75 years, prasugrel should be used with caution, but a MD of 5 mg o.d. should be used if treatment is deemed necessary. No specific dose adjustment in CKD patients. Prior stroke is a contraindication for prasugrel.

Ticagrelor LD of 180 mg orally, followed by an MD of 90 mg b.i.d.; no specific dose adjustment in CKD patients. Cangrelor Bolus of 30 mcg/kg i.v. followed by 4 mcg/kg/min infusion for at least 2 h or the duration of the procedure (whichever is longer). In the transition from cangrelor to a thienopyridine, the thienopyridine should be administered immediately after discontinuation of cangrelor

with an LD (clopidogrel 600 mg or prasugrel 60 mg); to avoid a potential DDI, prasugrel may also be administered 30 min before the cangrelor infusion is stopped. Ticagrelor (LD 180 mg) should be administered at the time of PCI to minimize the potential gap in platelet inhibition during the transition phase.

GP IIb/IIIa receptor inhibitors (i.v.) Eptifibatide Double bolus of 180 mcg/kg i.v. (given at a 10-min interval) followed by an infusion of 2.0 mcg/kg/min for up to 18 h.

For CrCl 30–50 mL/min: first LD, 180 mcg/kg i.v. bolus (max 22.6 mg); maintenance infusion, 1 mcg/kg/min (max 7.5 mg/h). Second LD (if PCI), 180 mcg/kg i.v. bolus (max 22.6 mg) should be administered 10 min after the first bolus. Contraindicated in patients with end-stage renal disease and with prior ICH, ischaemic stroke within 30 days, fibrinolysis, or platelet count <100 000/mm3.

Tirofiban Bolus of 25 mcg/kg i.v. over 3 min, followed by an infusion of 0.15 mcg/kg/min for up to 18 h.

For CrCl ≤60 mL/min: LD, 25 mcg/kg i.v. over 5 min followed by a maintenance infusion of 0.075 mcg/kg/min continued for up to 18 h. Contraindicated in patients with prior ICH, ischaemic stroke within 30 days, fibrinolysis, or platelet count <100 000/mm3.

II. Anticoagulant drugs UFH Initial treatment: i.v. bolus 70–100 U/kg followed by i.v. infusion titrated to achieve an aPTT of 60–80 s.

During PCI: 70–100 U/kg i.v. bolus or according to ACT in case of UFH pre-treatment.

Enoxaparin Initial treatment: for treatment of ACS 1 mg/kg b.i.d. subcutaneously for a minimum of 2 days and continued until clinical stabilization. In patients

whose CrCl is below 30 mL per minute (by Cockcroft–Gault equation), the enoxaparin dosage should be reduced to 1 mg per kg o.d. During PCI: for patients managed with PCI, if the last dose of enoxaparin was given less than 8 h before balloon inflation, no additional dosing is needed. If the last s.c. administration was given more than 8 h before balloon inflation, an i.v. bolus of 0.3 mg/kg enoxaparin sodium should be administered.

Bivalirudin During PPCI: 0.75 mg/kg i.v. bolus followed by i.v. infusion of 1.75 mg/kg/h for 4 h after the procedure.

In patients whose CrCl is below 30 mL/min (by Cockcroft–Gault equation), maintenance infusion should be reduced to 1 mg/kg/h.

Fondaparinux Initial treatment: 2.5 mg/d subcutaneously.

During PCI: A single bolus of UFH is recommended. Avoid if CrCl <20 mL/min. © ESC 2023

ACS, acute coronary syndrome; ACT, activated clotting time; aPPT, activated partial thromboplastin time; b.i.d., bis in die (twice a day); CKD, chronic kidney disease; CrCl, creatinine clearance; DDI, drug–drug interactions; ICH, intracranial haemorrhage; i.v. intravenous; LD, loading dose; MD, maintenance dose; o.d., once a day; PPCI, primary percutaneous coronary intervention; s.c. subcutaneous; UFH, unfractionated heparin.

ESC Guidelines                                                                                                                                                                                          3751

Downloaded from academic.oup.com/eurheartj/article/44/38/3720/7243210 by guest on 07 October 2026