p.99 抽出テキスト
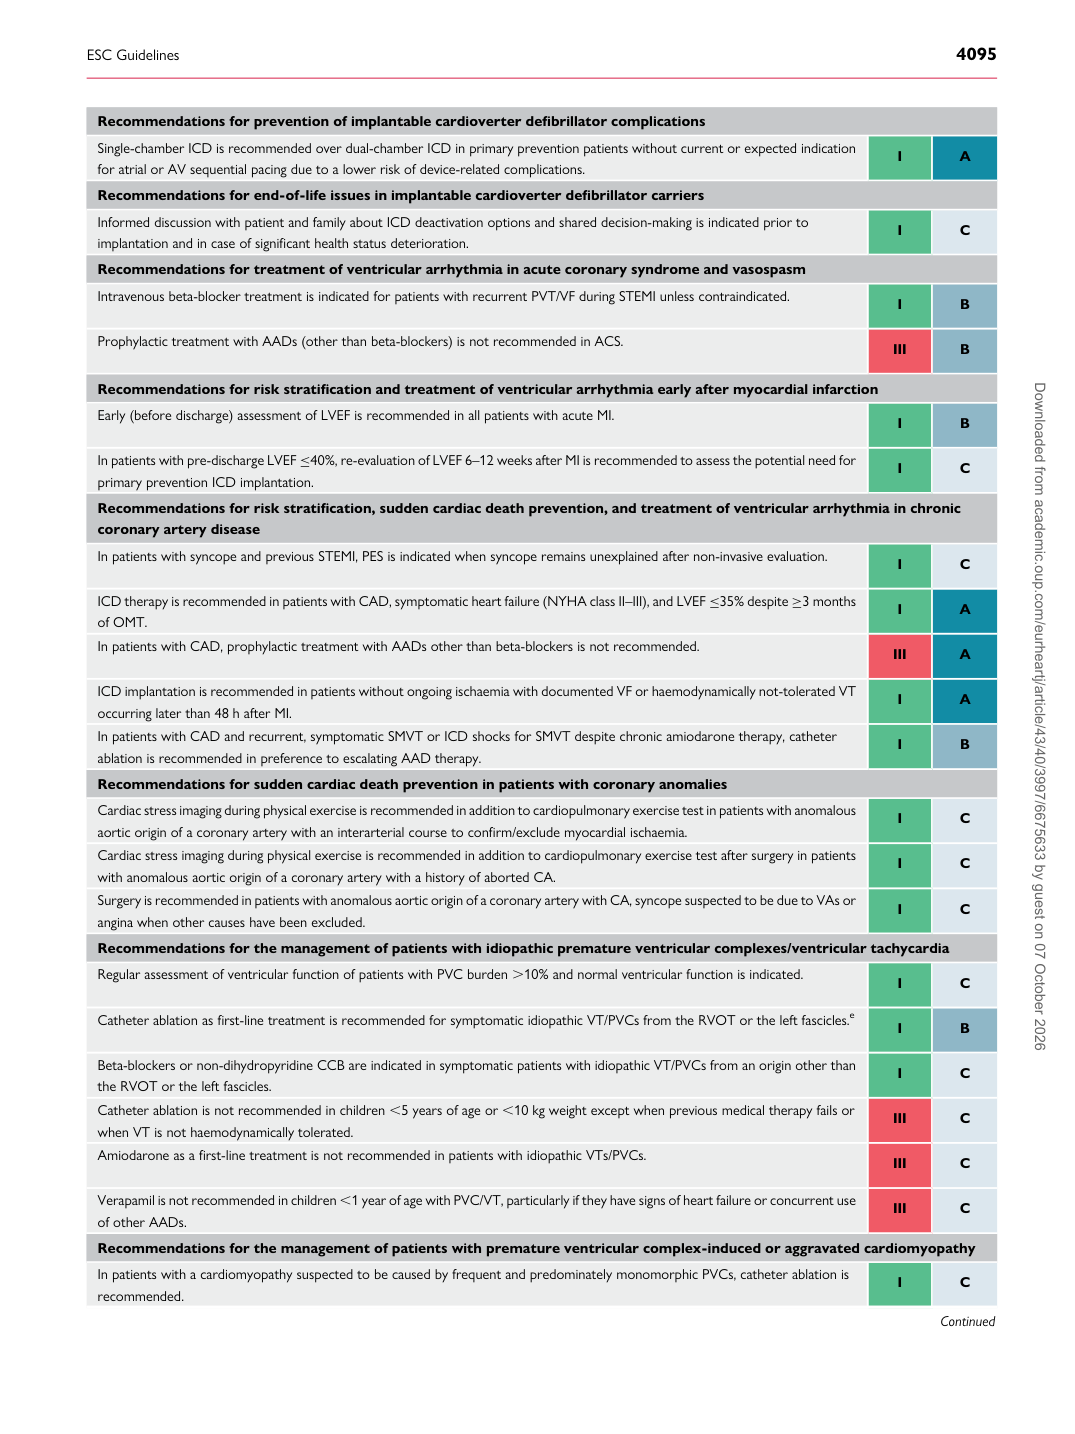
Recommendations for prevention of implantable cardioverter defibrillator complications Single-chamber ICD is recommended over dual-chamber ICD in primary prevention patients without current or expected indication for atrial or AV sequential pacing due to a lower risk of device-related complications. I A Recommendations for end-of-life issues in implantable cardioverter defibrillator carriers Informed discussion with patient and family about ICD deactivation options and shared decision-making is indicated prior to implantation and in case of significant health status deterioration. I C Recommendations for treatment of ventricular arrhythmia in acute coronary syndrome and vasospasm Intravenous beta-blocker treatment is indicated for patients with recurrent PVT/VF during STEMI unless contraindicated. I B

Prophylactic treatment with AADs (other than beta-blockers) is not recommended in ACS. III B

Recommendations for risk stratification and treatment of ventricular arrhythmia early after myocardial infarction Early (before discharge) assessment of LVEF is recommended in all patients with acute MI. I B

In patients with pre-discharge LVEF ≤40%, re-evaluation of LVEF 6–12 weeks after MI is recommended to assess the potential need for primary prevention ICD implantation. I C Recommendations for risk stratification, sudden cardiac death prevention, and treatment of ventricular arrhythmia in chronic coronary artery disease In patients with syncope and previous STEMI, PES is indicated when syncope remains unexplained after non-invasive evaluation. I C

ICD therapy is recommended in patients with CAD, symptomatic heart failure (NYHA class II–III), and LVEF ≤35% despite ≥3 months of OMT. I A In patients with CAD, prophylactic treatment with AADs other than beta-blockers is not recommended. III A

ICD implantation is recommended in patients without ongoing ischaemia with documented VF or haemodynamically not-tolerated VT occurring later than 48 h after MI. I A In patients with CAD and recurrent, symptomatic SMVT or ICD shocks for SMVT despite chronic amiodarone therapy, catheter ablation is recommended in preference to escalating AAD therapy. I B Recommendations for sudden cardiac death prevention in patients with coronary anomalies Cardiac stress imaging during physical exercise is recommended in addition to cardiopulmonary exercise test in patients with anomalous aortic origin of a coronary artery with an interarterial course to confirm/exclude myocardial ischaemia. I C Cardiac stress imaging during physical exercise is recommended in addition to cardiopulmonary exercise test after surgery in patients with anomalous aortic origin of a coronary artery with a history of aborted CA. I C Surgery is recommended in patients with anomalous aortic origin of a coronary artery with CA, syncope suspected to be due to VAs or angina when other causes have been excluded. I C Recommendations for the management of patients with idiopathic premature ventricular complexes/ventricular tachycardia Regular assessment of ventricular function of patients with PVC burden .10% and normal ventricular function is indicated. I C

Catheter ablation as first-line treatment is recommended for symptomatic idiopathic VT/PVCs from the RVOT or the left fascicles.e I B

Beta-blockers or non-dihydropyridine CCB are indicated in symptomatic patients with idiopathic VT/PVCs from an origin other than the RVOT or the left fascicles. I C Catheter ablation is not recommended in children ,5 years of age or ,10 kg weight except when previous medical therapy fails or when VT is not haemodynamically tolerated. III C Amiodarone as a first-line treatment is not recommended in patients with idiopathic VTs/PVCs. III C

Verapamil is not recommended in children ,1 year of age with PVC/VT, particularly if they have signs of heart failure or concurrent use of other AADs. III C Recommendations for the management of patients with premature ventricular complex-induced or aggravated cardiomyopathy In patients with a cardiomyopathy suspected to be caused by frequent and predominately monomorphic PVCs, catheter ablation is recommended. I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026