p.98 抽出テキスト
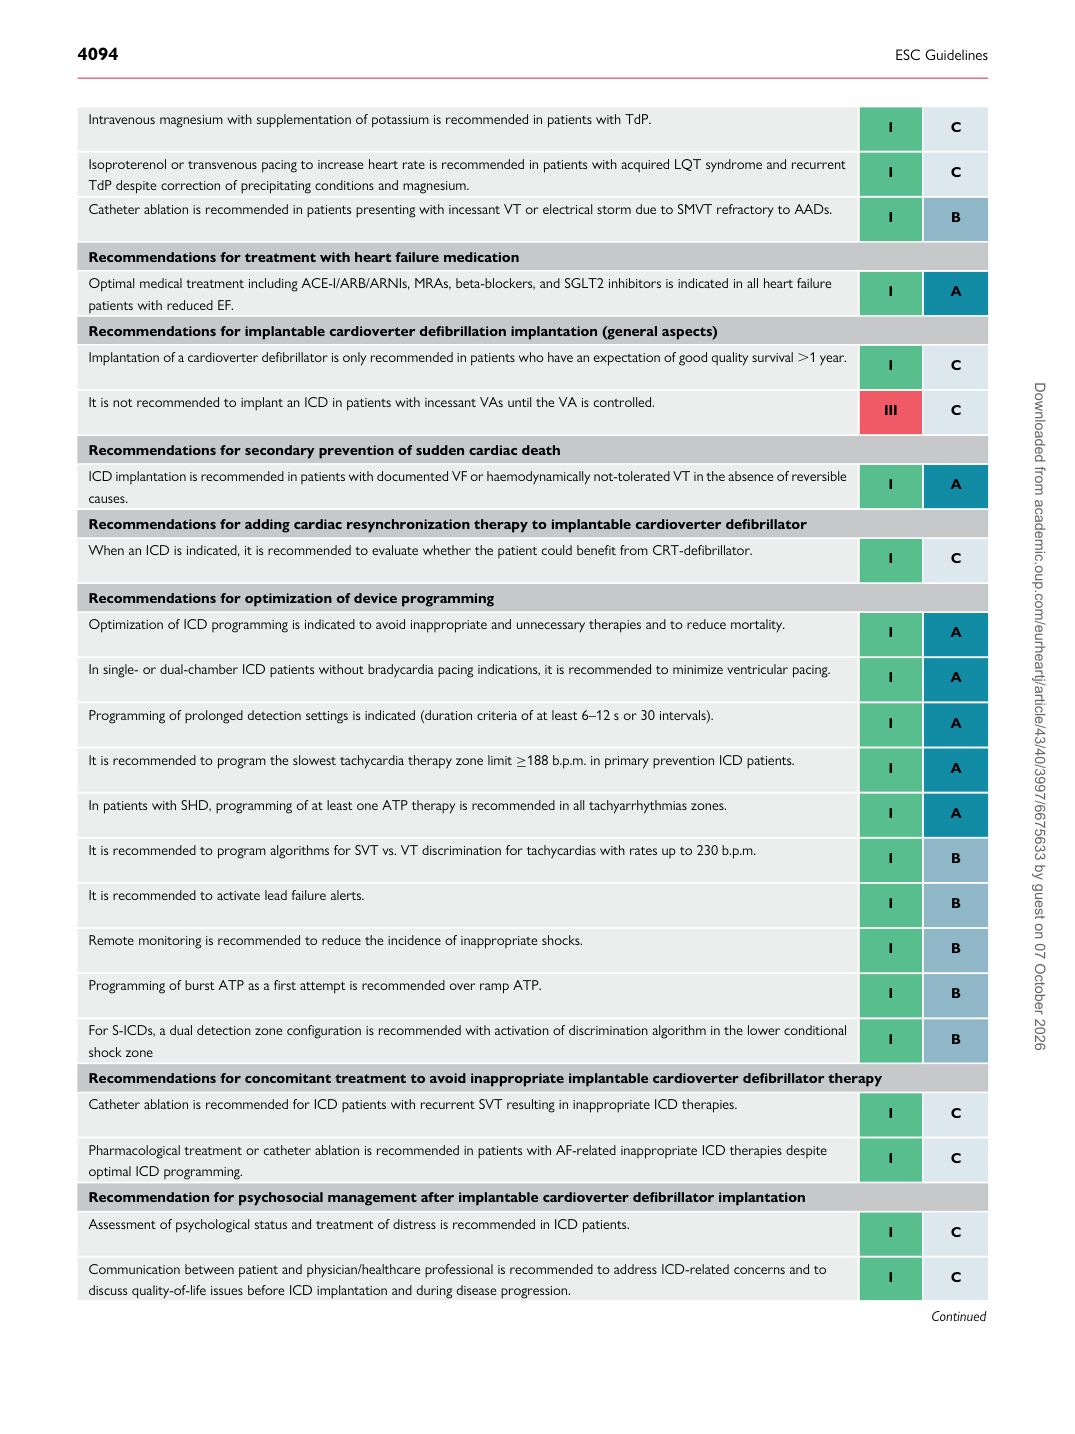
Intravenous magnesium with supplementation of potassium is recommended in patients with TdP. I C

Isoproterenol or transvenous pacing to increase heart rate is recommended in patients with acquired LQT syndrome and recurrent TdP despite correction of precipitating conditions and magnesium. I C Catheter ablation is recommended in patients presenting with incessant VT or electrical storm due to SMVT refractory to AADs. I B

Recommendations for treatment with heart failure medication Optimal medical treatment including ACE-I/ARB/ARNIs, MRAs, beta-blockers, and SGLT2 inhibitors is indicated in all heart failure patients with reduced EF. I A Recommendations for implantable cardioverter defibrillation implantation (general aspects) Implantation of a cardioverter defibrillator is only recommended in patients who have an expectation of good quality survival .1 year. I C

It is not recommended to implant an ICD in patients with incessant VAs until the VA is controlled. III C

Recommendations for secondary prevention of sudden cardiac death ICD implantation is recommended in patients with documented VF or haemodynamically not-tolerated VT in the absence of reversible causes. I A Recommendations for adding cardiac resynchronization therapy to implantable cardioverter defibrillator When an ICD is indicated, it is recommended to evaluate whether the patient could benefit from CRT-defibrillator. I C

Recommendations for optimization of device programming Optimization of ICD programming is indicated to avoid inappropriate and unnecessary therapies and to reduce mortality. I A

In single- or dual-chamber ICD patients without bradycardia pacing indications, it is recommended to minimize ventricular pacing. I A

Programming of prolonged detection settings is indicated (duration criteria of at least 6–12 s or 30 intervals). I A

It is recommended to program the slowest tachycardia therapy zone limit ≥188 b.p.m. in primary prevention ICD patients. I A

In patients with SHD, programming of at least one ATP therapy is recommended in all tachyarrhythmias zones. I A

It is recommended to program algorithms for SVT vs. VT discrimination for tachycardias with rates up to 230 b.p.m. I B

It is recommended to activate lead failure alerts. I B

Remote monitoring is recommended to reduce the incidence of inappropriate shocks. I B

Programming of burst ATP as a first attempt is recommended over ramp ATP. I B

For S-ICDs, a dual detection zone configuration is recommended with activation of discrimination algorithm in the lower conditional shock zone I B Recommendations for concomitant treatment to avoid inappropriate implantable cardioverter defibrillator therapy Catheter ablation is recommended for ICD patients with recurrent SVT resulting in inappropriate ICD therapies. I C

Pharmacological treatment or catheter ablation is recommended in patients with AF-related inappropriate ICD therapies despite optimal ICD programming. I C Recommendation for psychosocial management after implantable cardioverter defibrillator implantation Assessment of psychological status and treatment of distress is recommended in ICD patients. I C

Communication between patient and physician/healthcare professional is recommended to address ICD-related concerns and to discuss quality-of-life issues before ICD implantation and during disease progression. I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026