p.91 抽出テキスト
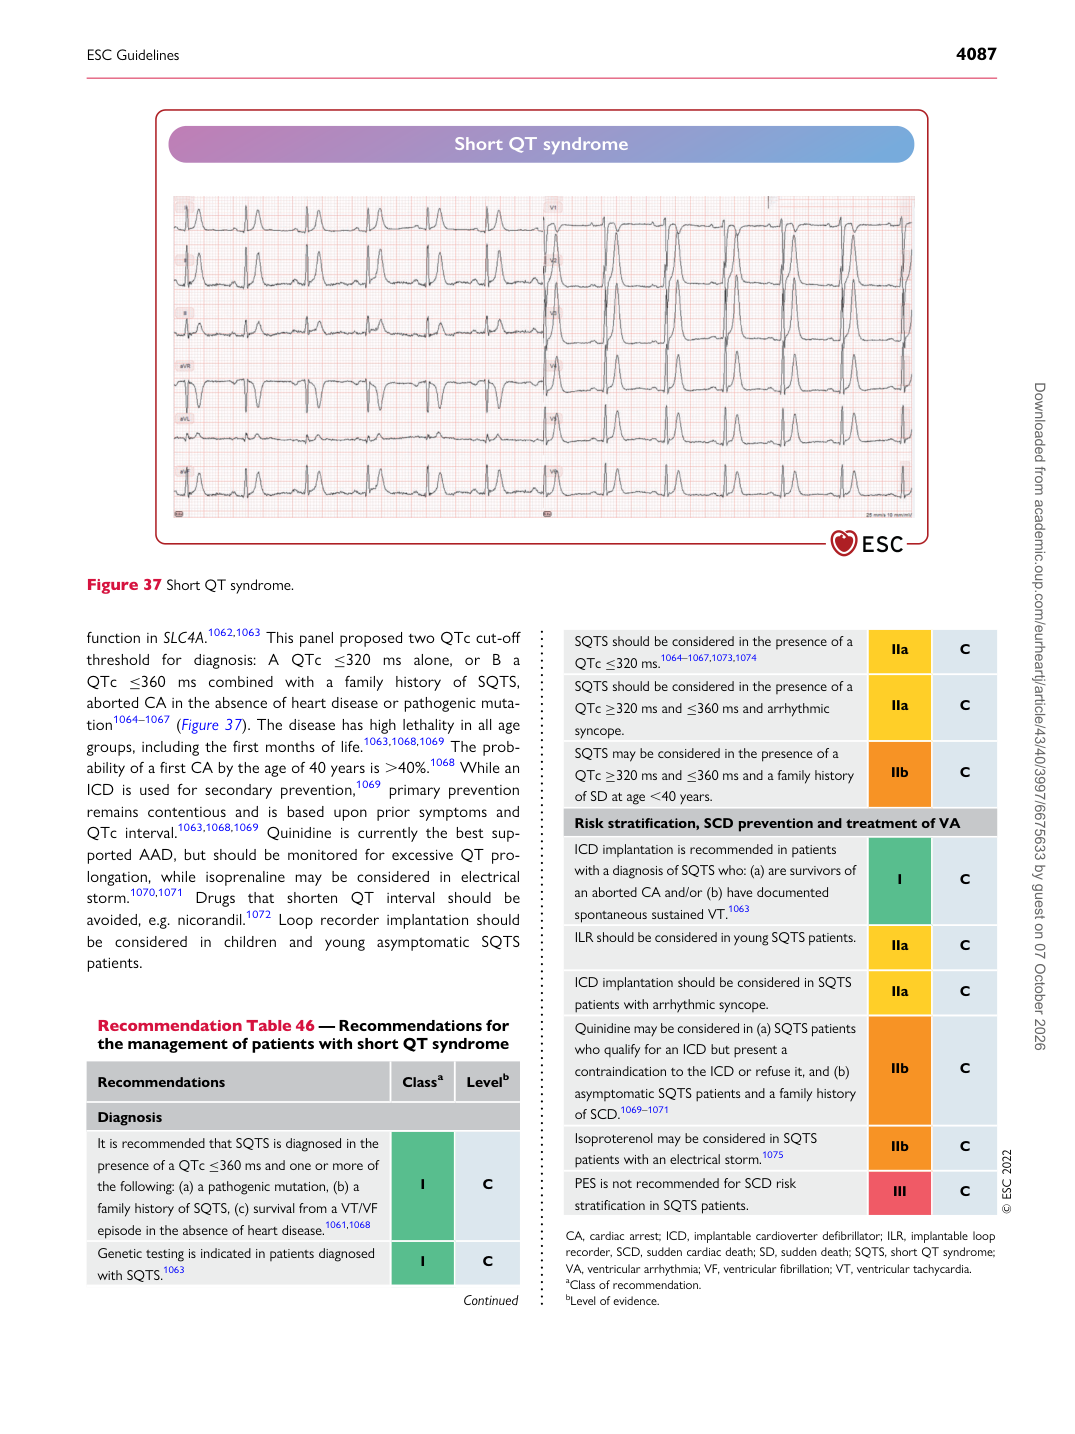
function in SLC4A.1062,1063 This panel proposed two QTc cut-off threshold for diagnosis: A QTc ≤320 ms alone, or B a QTc ≤360 ms combined with a family history of SQTS, aborted CA in the absence of heart disease or pathogenic mutation1064–1067 (Figure 37). The disease has high lethality in all age groups, including the first months of life.1063,1068,1069 The probability of a first CA by the age of 40 years is .40%.1068 While an ICD is used for secondary prevention,1069 primary prevention remains contentious and is based upon prior symptoms and QTc interval.1063,1068,1069 Quinidine is currently the best supported AAD, but should be monitored for excessive QT prolongation, while isoprenaline may be considered in electrical storm.1070,1071 Drugs that shorten QT interval should be avoided, e.g. nicorandil.1072 Loop recorder implantation should be considered in children and young asymptomatic SQTS patients.

Short QT syndrome

Figure 37 Short QT syndrome.

Recommendation Table 46 — Recommendations for the management of patients with short QT syndrome

Recommendations Classa Levelb

Diagnosis It is recommended that SQTS is diagnosed in the presence of a QTc ≤360 ms and one or more of the following: (a) a pathogenic mutation, (b) a family history of SQTS, (c) survival from a VT/VF episode in the absence of heart disease.1061,1068 I C Genetic testing is indicated in patients diagnosed with SQTS.1063 I C

Continued SQTS should be considered in the presence of a

QTc ≤320 ms.1064–1067,1073,1074 IIa C SQTS should be considered in the presence of a QTc ≥320 ms and ≤360 ms and arrhythmic syncope. IIa C SQTS may be considered in the presence of a QTc ≥320 ms and ≤360 ms and a family history of SD at age ,40 years. IIb C Risk stratification, SCD prevention and treatment of VA ICD implantation is recommended in patients with a diagnosis of SQTS who: (a) are survivors of an aborted CA and/or (b) have documented spontaneous sustained VT.1063 I C ILR should be considered in young SQTS patients. IIa C

ICD implantation should be considered in SQTS patients with arrhythmic syncope. IIa C Quinidine may be considered in (a) SQTS patients who qualify for an ICD but present a contraindication to the ICD or refuse it, and (b) asymptomatic SQTS patients and a family history of SCD.1069–1071 IIb C Isoproterenol may be considered in SQTS patients with an electrical storm.1075 IIb C PES is not recommended for SCD risk stratification in SQTS patients. III C © ESC 2022

CA, cardiac arrest; ICD, implantable cardioverter defibrillator; ILR, implantable loop recorder, SCD, sudden cardiac death; SD, sudden death; SQTS, short QT syndrome; VA, ventricular arrhythmia; VF, ventricular fibrillation; VT, ventricular tachycardia. aClass of recommendation. bLevel of evidence. Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026