p.87 抽出テキスト
Exclude alternati v e diagnosis consistent with ECG

o a

Sustained V A or abo

V V r ted ca r diac a r r est

N

Y Sp o nt an e o u s t y

t t pe

1 Br

S EC G

Results

P ositi v e Negati v e

ICD implantation

(Class I)

General r ecommendations b

(Class I)

S od iu m c h an nel b l oc k er

k k t es t (Cl ass III )

ICD implantation

(Class I)

General r ecommendations b

(Class I) S od i u m c h an n e l bl oc k er

k k t es t (Cl ass I )

R e cu r r ent sym

t pt oma ti

a a c V A

V V

Q u i n i d in e (Cl ass II a )

Rec u r r e nt sy

t m p t o m a ti

a c V A

V V

C a th

a e t er a bl a ti

a a o n (Cl ass II a ) F u r th er e va l ua ti

a o n f o

f f r

a lt er n a ti

a v e ca u se o f V A/

V V C A

Rec u r r e nt sy

t m p t o m a ti

a a c V A

V V

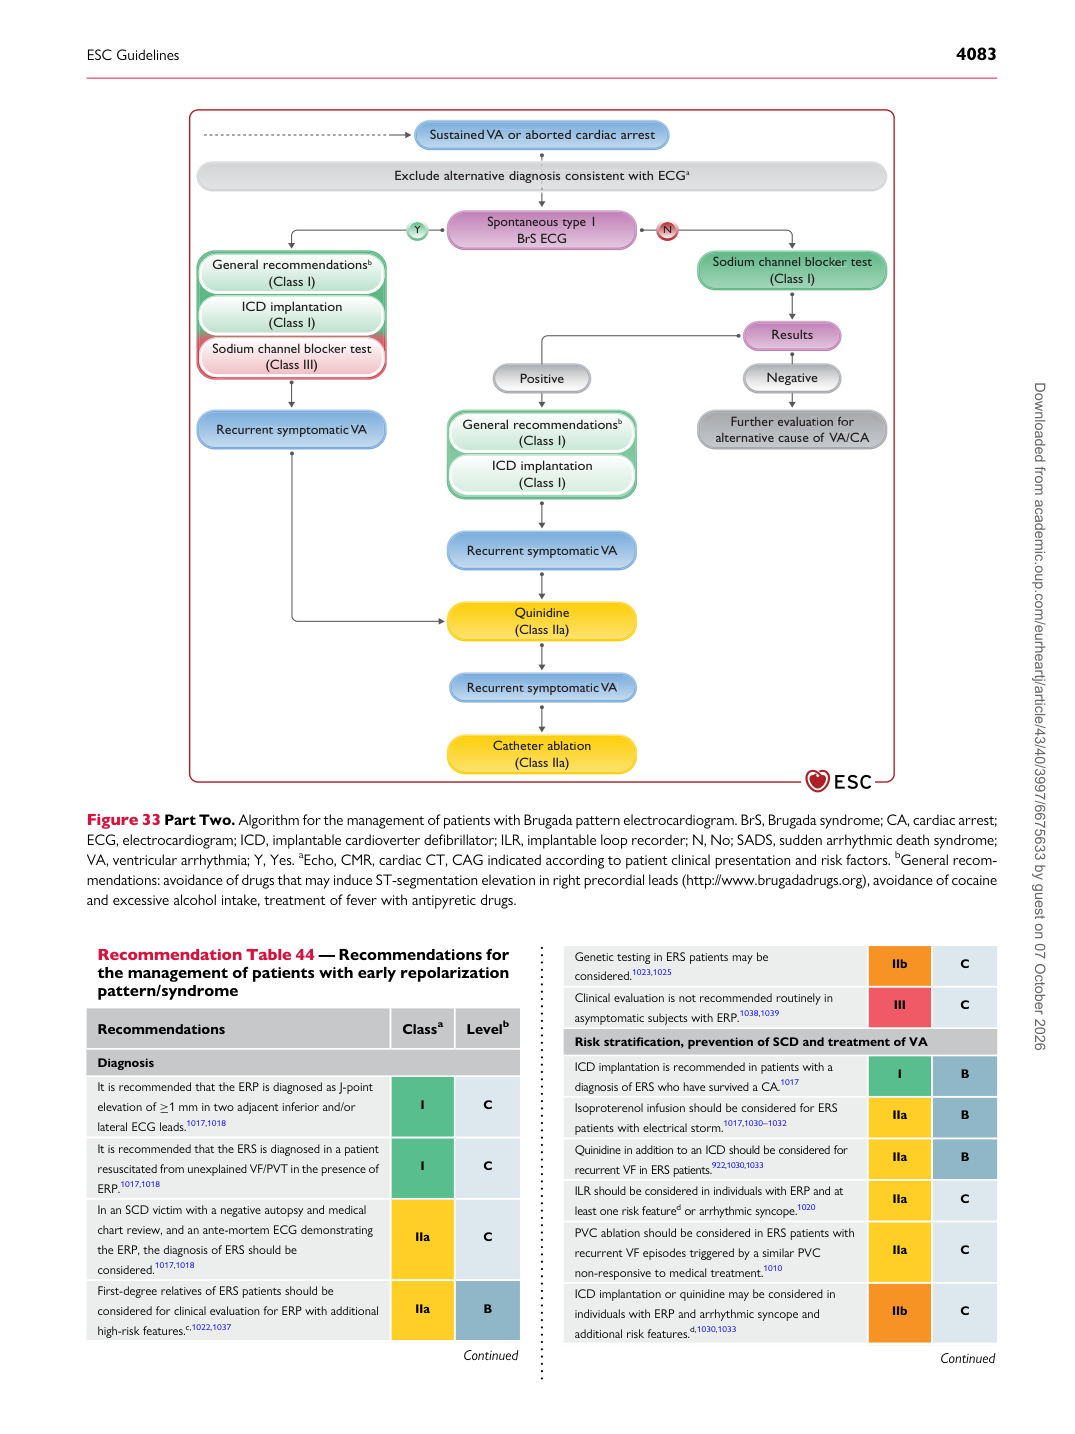
Figure 33 Part Two. Algorithm for the management of patients with Brugada pattern electrocardiogram. BrS, Brugada syndrome; CA, cardiac arrest; ECG, electrocardiogram; ICD, implantable cardioverter defibrillator; ILR, implantable loop recorder; N, No; SADS, sudden arrhythmic death syndrome; VA, ventricular arrhythmia; Y, Yes. aEcho, CMR, cardiac CT, CAG indicated according to patient clinical presentation and risk factors. bGeneral recommendations: avoidance of drugs that may induce ST-segmentation elevation in right precordial leads (http://www.brugadadrugs.org), avoidance of cocaine and excessive alcohol intake, treatment of fever with antipyretic drugs.

Recommendation Table 44 — Recommendations for the management of patients with early repolarization pattern/syndrome

Recommendations Classa Levelb

Diagnosis It is recommended that the ERP is diagnosed as J-point elevation of ≥1 mm in two adjacent inferior and/or lateral ECG leads.1017,1018 I C It is recommended that the ERS is diagnosed in a patient resuscitated from unexplained VF/PVT in the presence of ERP.1017,1018 I C In an SCD victim with a negative autopsy and medical chart review, and an ante-mortem ECG demonstrating the ERP, the diagnosis of ERS should be considered.1017,1018 IIa C First-degree relatives of ERS patients should be considered for clinical evaluation for ERP with additional high-risk features.c,1022,1037 IIa B

Continued Genetic testing in ERS patients may be

considered.1023,1025 IIb C Clinical evaluation is not recommended routinely in asymptomatic subjects with ERP.1038,1039 III C Risk stratification, prevention of SCD and treatment of VA ICD implantation is recommended in patients with a diagnosis of ERS who have survived a CA.1017 I B Isoproterenol infusion should be considered for ERS patients with electrical storm.1017,1030–1032 IIa B Quinidine in addition to an ICD should be considered for recurrent VF in ERS patients.922,1030,1033 IIa B ILR should be considered in individuals with ERP and at least one risk featured or arrhythmic syncope.1020 IIa C PVC ablation should be considered in ERS patients with recurrent VF episodes triggered by a similar PVC non-responsive to medical treatment.1010 IIa C ICD implantation or quinidine may be considered in individuals with ERP and arrhythmic syncope and additional risk features.d,1030,1033 IIb C

Continued Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026