p.73 抽出テキスト
of ICD implantation in these patients. Indeed, a meta-analysis of observational studies found no benefit of ICD (n = 483) vs. amiodarone (n = 115) for the secondary prevention of SCD in patients with Chagas’ disease as all-cause annual mortality rates were comparable in both groups (9.7% and 9.6%, respectively).856 Another meta-analysis found a 4.7% annual incidence of inappropriate shocks and a high 9.0% annual mortality rate in 1041 ICD patients with Chagas’ disease.851

Amiodarone857 and catheter ablation858–860 have been successfully used to control recurrent VAs in some patients. As with various forms of myocarditis, the arrhythmogenic substrate is often found at the epicardium in Chagas’ cardiomyopathy.

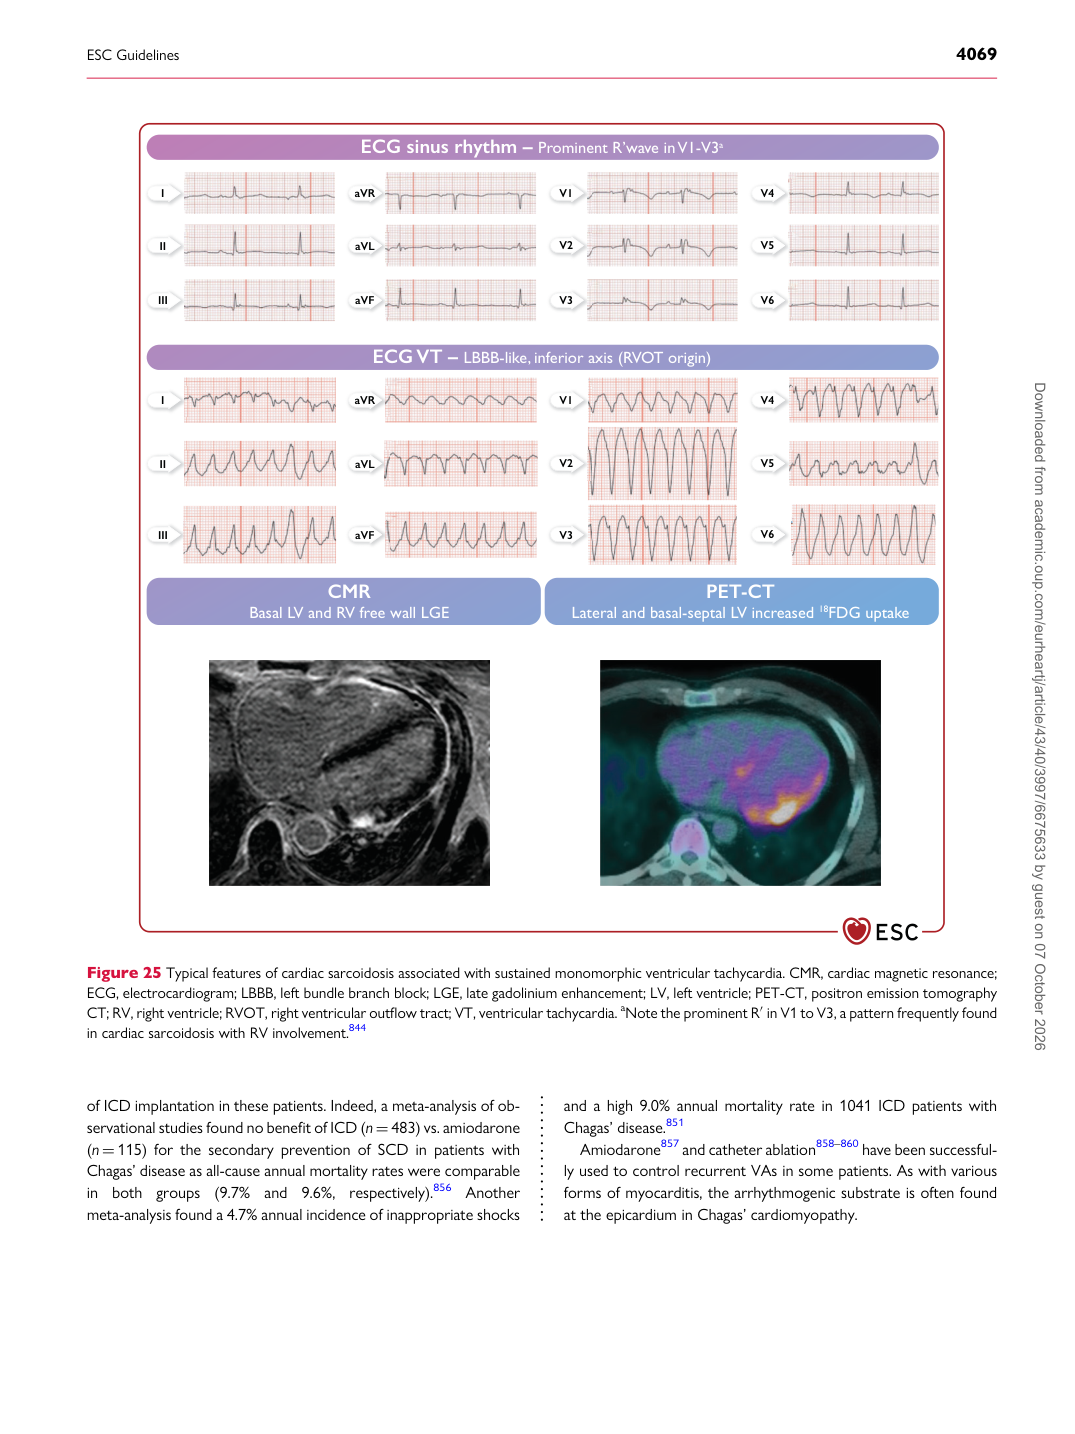
ECG sinus rhythm – Prominent R’wave inV1-V3a

ECG VT – LBBB-like, inferior axis (RVOT origin)

CMR Basal LV and RV free wall LGE PET-CT Lateral and basal-septal LV increased 18FDG uptake

I

II

III V1

V2

V3

aVR

aVL

aVF V4

V5

V6

I

II

III V1

V2

V3

aVR

aVL

aVF V4

V5

V6

Figure 25 Typical features of cardiac sarcoidosis associated with sustained monomorphic ventricular tachycardia. CMR, cardiac magnetic resonance; ECG, electrocardiogram; LBBB, left bundle branch block; LGE, late gadolinium enhancement; LV, left ventricle; PET-CT, positron emission tomography CT; RV, right ventricle; RVOT, right ventricular outflow tract; VT, ventricular tachycardia. aNote the prominent R′ in V1 to V3, a pattern frequently found in cardiac sarcoidosis with RV involvement.844 Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026