p.68 抽出テキスト
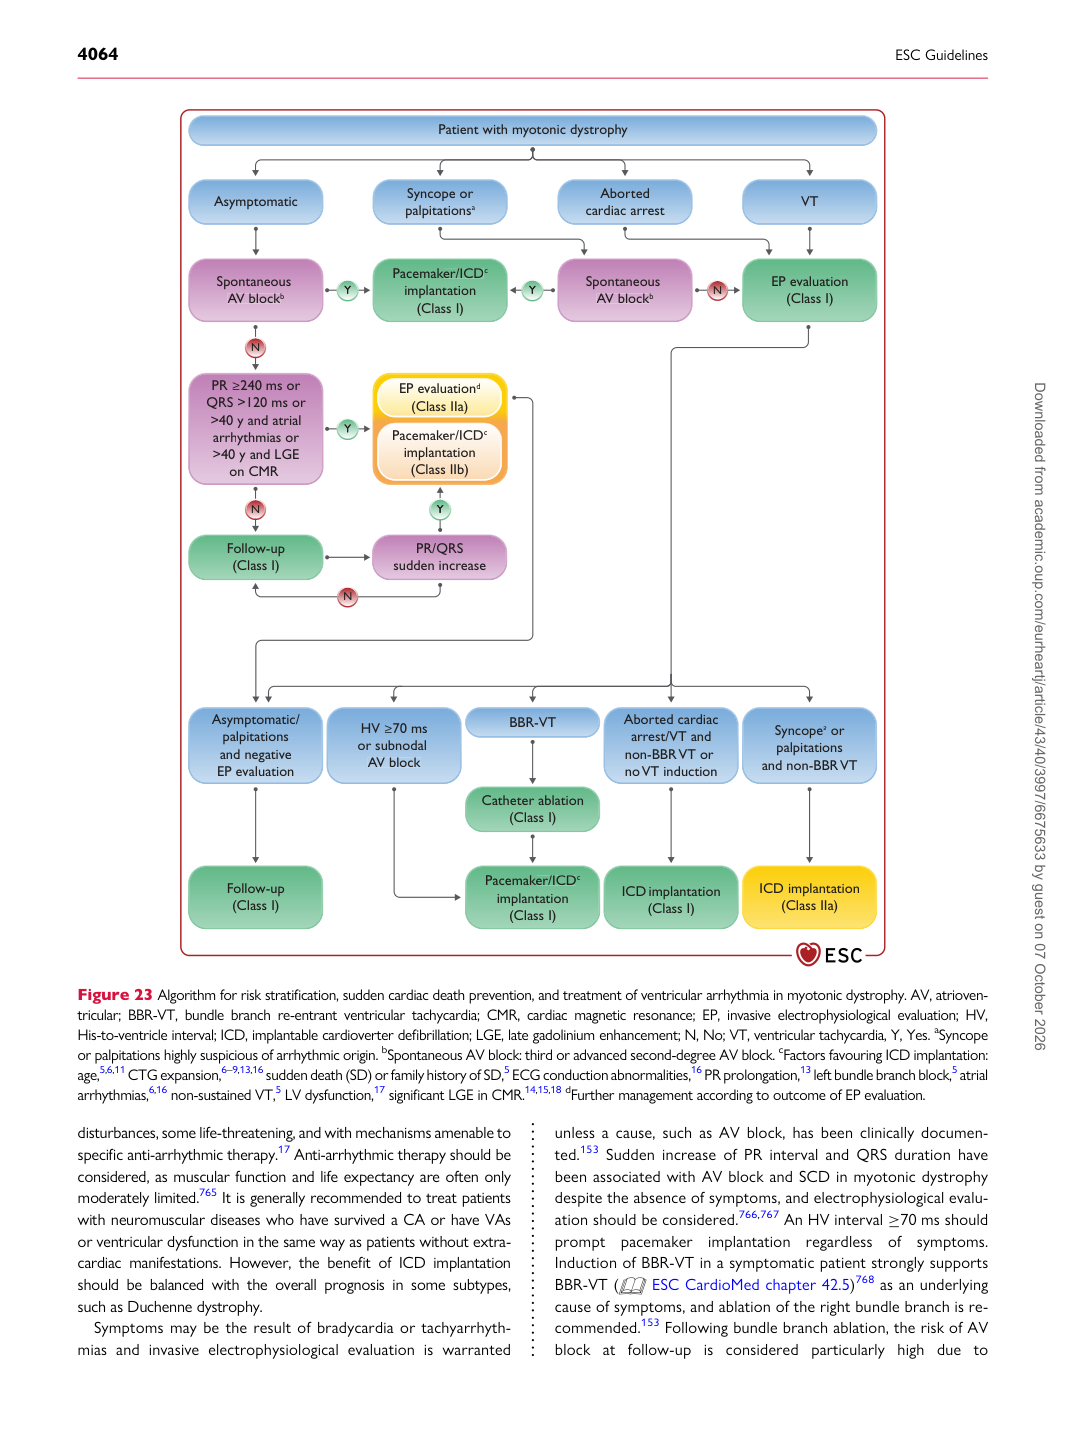
disturbances, some life-threatening, and with mechanisms amenable to specific anti-arrhythmic therapy.17 Anti-arrhythmic therapy should be considered, as muscular function and life expectancy are often only moderately limited.765 It is generally recommended to treat patients with neuromuscular diseases who have survived a CA or have VAs or ventricular dysfunction in the same way as patients without extracardiac manifestations. However, the benefit of ICD implantation should be balanced with the overall prognosis in some subtypes, such as Duchenne dystrophy. Symptoms may be the result of bradycardia or tachyarrhythmias and invasive electrophysiological evaluation is warranted unless a cause, such as AV block, has been clinically documented.153 Sudden increase of PR interval and QRS duration have been associated with AV block and SCD in myotonic dystrophy despite the absence of symptoms, and electrophysiological evaluation should be considered.766,767 An HV interval ≥70 ms should prompt pacemaker implantation regardless of symptoms. Induction of BBR-VT in a symptomatic patient strongly supports BBR-VT ( ESC CardioMed chapter 42.5)768 as an underlying cause of symptoms, and ablation of the right bundle branch is recommended.153 Following bundle branch ablation, the risk of AV block at follow-up is considered particularly high due to

BBR-VT

Pacema k er/ICD

k k c implantation

(Class I)

Pacema k er/ICD

k k c implantation

(Class I)

Spontaneous

A V block A A b Spontaneous

A V block A A b EP e valuation

(Class I)

Catheter ablation

(Class I)

F oll o w-up (Class I) PR/QRS

su d den inc r ease

ICD implantation

(Class I)

F oll o w-up (Class I) ICD implantation

(Class IIa)

Abo r ted ca r diac a r r est/VT and non-BBR VT or no VT induction

HV ≥ 70 ms or subnodal

A V block

A

A

Asymptomatic/

palpitations and negati v e EP e valuation Syncope a or

palpitations and non-BBR VT

N

N

PR ≥ 240 ms or QRS >120 ms or >40 y and atrial a r r h ythmias or >40 y and LGE

on CMR

N

N

Y Y

Y Y

Y Y Y Y

Patient with m y otonic dyst r op h y

Asymptomatic Syncope or

palpitations a Abo r ted

ca r diac a r r est VT

Pacema k er/ICD

k k c implantation (Class IIb)

EP e valuation d

(Class IIa)

Figure 23 Algorithm for risk stratification, sudden cardiac death prevention, and treatment of ventricular arrhythmia in myotonic dystrophy. AV, atrioventricular; BBR-VT, bundle branch re-entrant ventricular tachycardia; CMR, cardiac magnetic resonance; EP, invasive electrophysiological evaluation; HV, His-to-ventricle interval; ICD, implantable cardioverter defibrillation; LGE, late gadolinium enhancement; N, No; VT, ventricular tachycardia, Y, Yes. aSyncope or palpitations highly suspicious of arrhythmic origin. bSpontaneous AV block: third or advanced second-degree AV block. cFactors favouring ICD implantation: age,5,6,11 CTG expansion,6–9,13,16 sudden death (SD) orfamily history of SD,5 ECG conduction abnormalities,16 PRprolongation,13 left bundle branch block,5 atrial arrhythmias,6,16 non-sustained VT,5 LV dysfunction,17 significant LGE in CMR.14,15,18 dFurther management according to outcome of EP evaluation. Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026