p.59 抽出テキスト
events in DCM patients with a low LVEF and an unexplained syncope was similar to those with prior CA657 and high, independent from the outcome of PES.148 However, data in DCM patients with a mildly reduced EF suggest an incremental value of PES. Among DCM patients with an EF ≥40% and an unexplained syncope, who underwent ICD implantation after a positive PES, 80% had appropriate ICD therapy during follow-up. No SCD or symptomatic VA occurred in non-inducible patients.146

7.1.3.1.2 Primary prevention of sudden cardiac death. In patients

with DCM/HNDCM, OMT according to current 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure is mandatory.342 Re-evaluation of cardiac function and clinical status after 3 months’ OMT is required before primary prevention ICD implantation. LV function is more likely to improve in DCM caused by myocarditis or TTN mutations.

The efficacy of primary prevention ICDs in DCM patients with HFrEF has been addressed in six RCTs.635 Five studies were published between 2002 and 2005 (CAT, AMIOVIRT, DEFINITE, COMPANION, and SCD-HeFT). The first three were smaller studies enrolling only DCM patients, whereas SCD-HeFT and COMPANION were larger and

Patient with DCM/HNDCM

Suspicious of cause requiring specific treatment

Family history of DCM/HNDCM or family history of SCD (<50 y, first-degree relative) or

AV block <50 y

5-year risk ofVA ≥10% and LVEF <50% or NSVT or AV conduction delay

Pathogenic mutation LMNA

ICD implantation

(Class IIa) ICD implantation

(Class IIa)

ICD implantation

(Class IIa)

ICD implantation

(Class IIa)

Genetic testing (Class IIa) (Class I) Go to specific sections for specific aetiology-directed management,

especially for inflammatory diseases

CMR (Class IIa)

Annual reevaluation

LVEF

≥2 risk factorsa

SMVT inducible

PES (Class IIa) ILRb (Class I)

Follow-up Unexplained syncope

Y

Y

Y

Y Y

Y

N N

N

N

N N

≤35% 36–50%

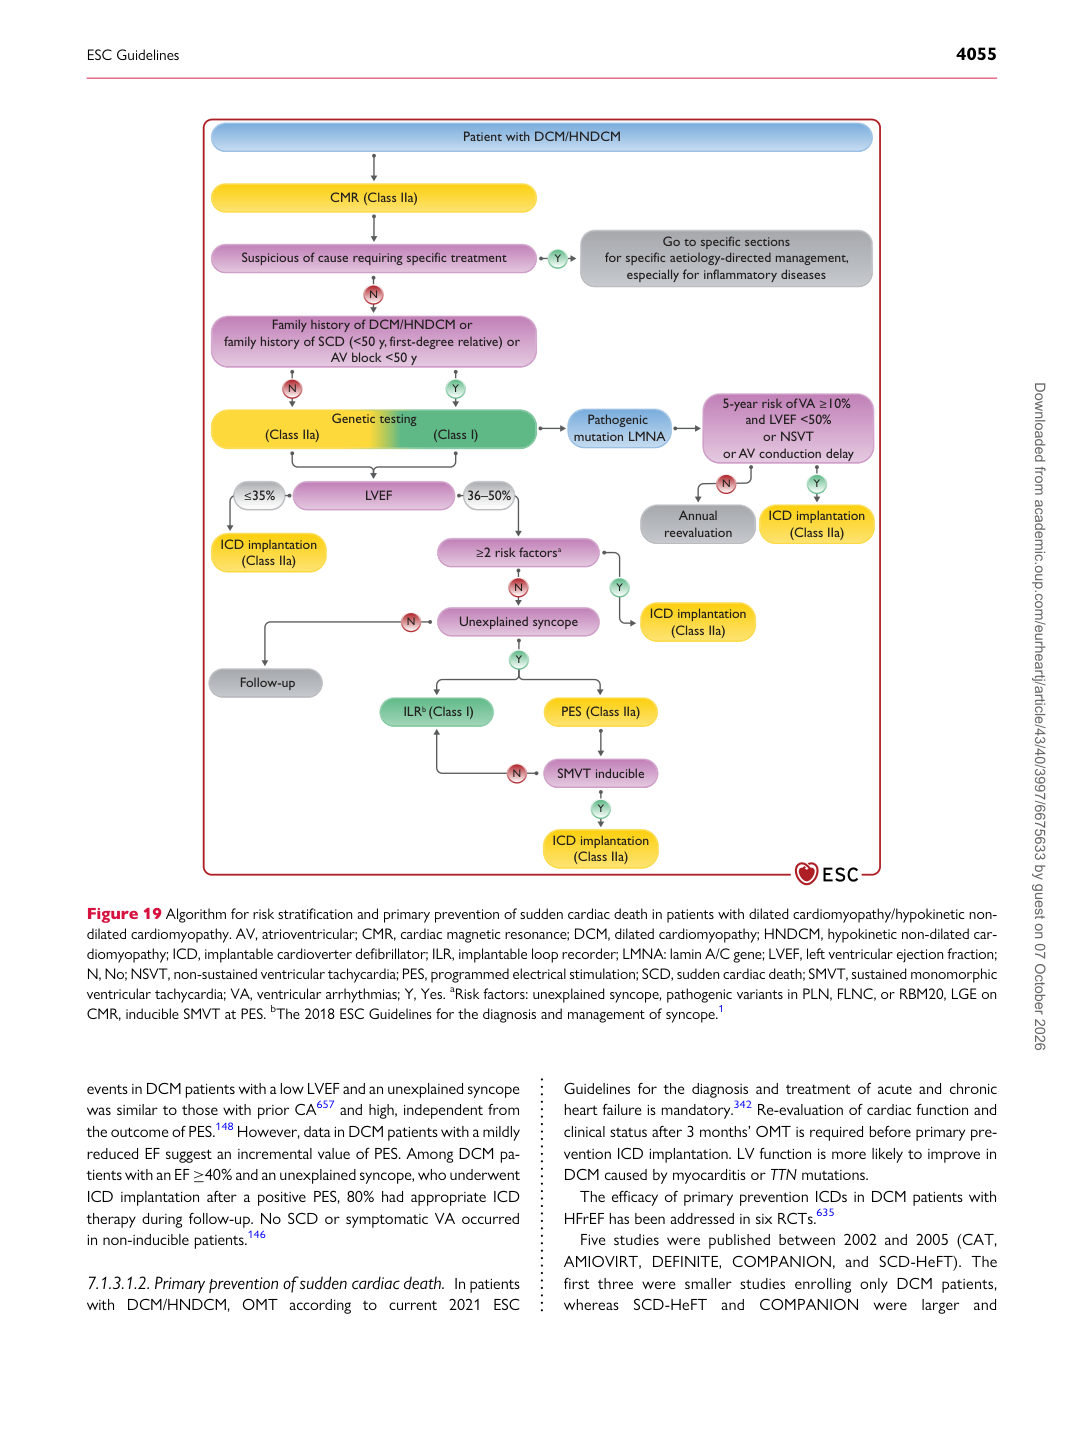
Figure 19 Algorithm for risk stratification and primary prevention of sudden cardiac death in patients with dilated cardiomyopathy/hypokinetic nondilated cardiomyopathy. AV, atrioventricular; CMR, cardiac magnetic resonance; DCM, dilated cardiomyopathy; HNDCM, hypokinetic non-dilated cardiomyopathy; ICD, implantable cardioverter defibrillator; ILR, implantable loop recorder; LMNA: lamin A/C gene; LVEF, left ventricular ejection fraction; N, No; NSVT, non-sustained ventricular tachycardia; PES, programmed electrical stimulation; SCD, sudden cardiac death; SMVT, sustained monomorphic ventricular tachycardia; VA, ventricular arrhythmias; Y, Yes. aRisk factors: unexplained syncope, pathogenic variants in PLN, FLNC, or RBM20, LGE on CMR, inducible SMVT at PES. bThe 2018 ESC Guidelines for the diagnosis and management of syncope.1 Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026