p.102 抽出テキスト
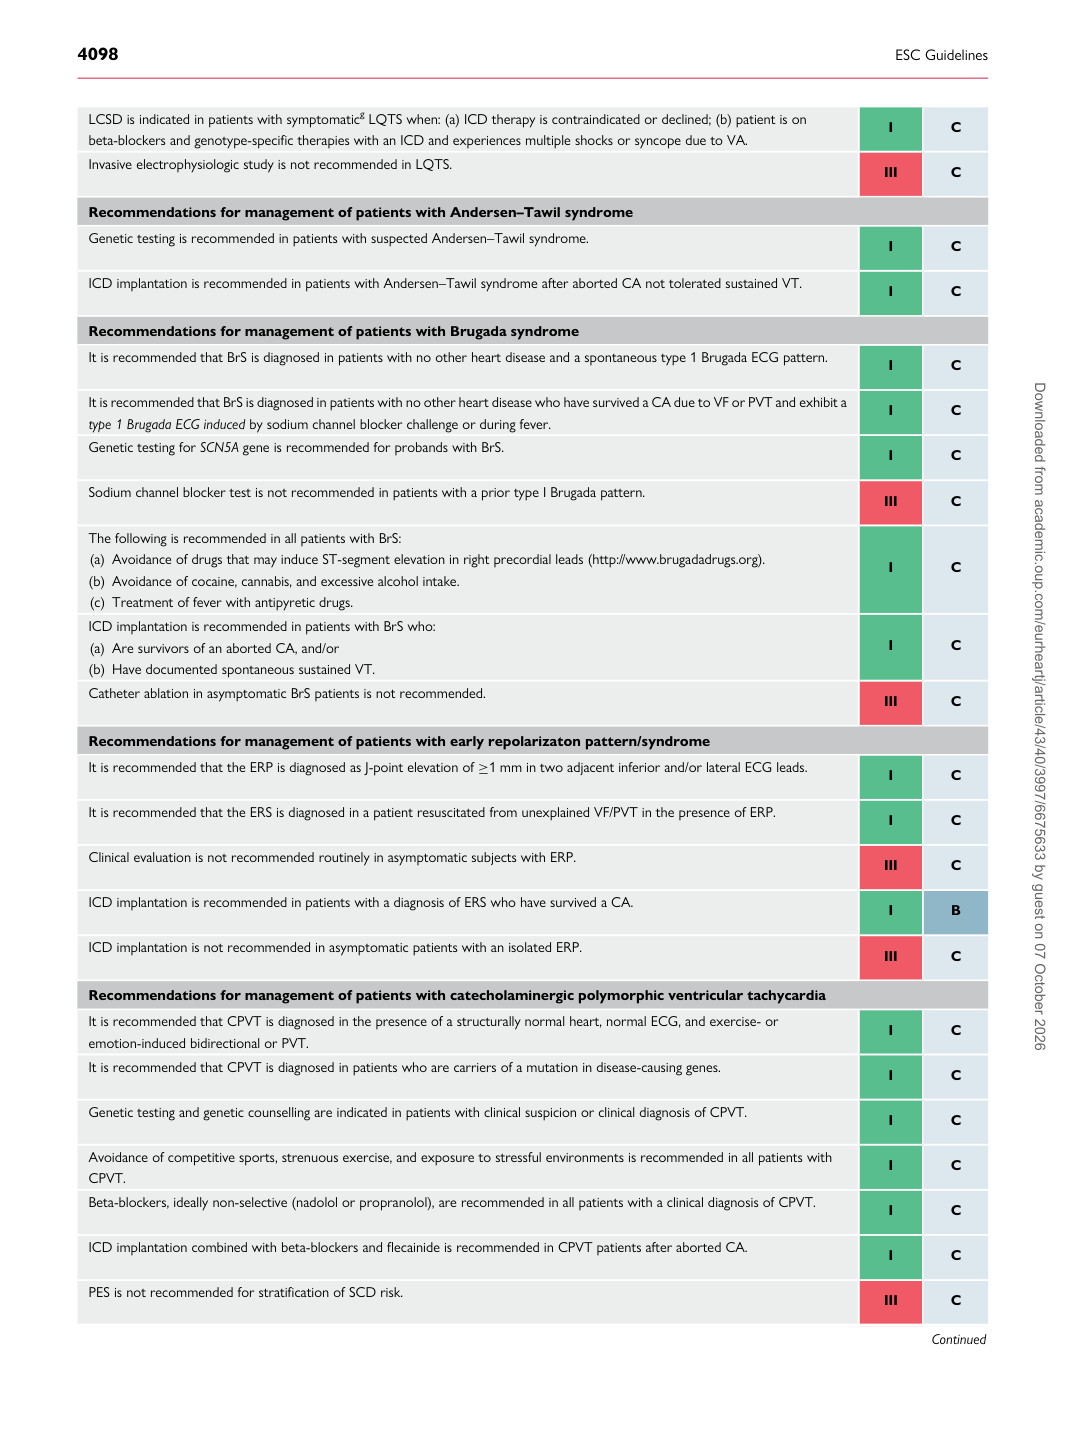
LCSD is indicated in patients with symptomaticg LQTS when: (a) ICD therapy is contraindicated or declined; (b) patient is on beta-blockers and genotype-specific therapies with an ICD and experiences multiple shocks or syncope due to VA. I C Invasive electrophysiologic study is not recommended in LQTS. III C

Recommendations for management of patients with Andersen–Tawil syndrome Genetic testing is recommended in patients with suspected Andersen–Tawil syndrome. I C

ICD implantation is recommended in patients with Andersen–Tawil syndrome after aborted CA not tolerated sustained VT. I C

Recommendations for management of patients with Brugada syndrome It is recommended that BrS is diagnosed in patients with no other heart disease and a spontaneous type 1 Brugada ECG pattern. I C

It is recommended that BrS is diagnosed in patients with no other heart disease who have survived a CA due to VF or PVT and exhibit a type 1 Brugada ECG induced by sodium channel blocker challenge or during fever. I C Genetic testing for SCN5A gene is recommended for probands with BrS. I C

Sodium channel blocker test is not recommended in patients with a prior type I Brugada pattern. III C

The following is recommended in all patients with BrS: (a) Avoidance of drugs that may induce ST-segment elevation in right precordial leads (http://www.brugadadrugs.org). (b) Avoidance of cocaine, cannabis, and excessive alcohol intake. (c) Treatment of fever with antipyretic drugs. I C ICD implantation is recommended in patients with BrS who: (a) Are survivors of an aborted CA, and/or (b) Have documented spontaneous sustained VT. I C Catheter ablation in asymptomatic BrS patients is not recommended. III C

Recommendations for management of patients with early repolarizaton pattern/syndrome It is recommended that the ERP is diagnosed as J-point elevation of ≥1 mm in two adjacent inferior and/or lateral ECG leads. I C

It is recommended that the ERS is diagnosed in a patient resuscitated from unexplained VF/PVT in the presence of ERP. I C

Clinical evaluation is not recommended routinely in asymptomatic subjects with ERP. III C

ICD implantation is recommended in patients with a diagnosis of ERS who have survived a CA. I B

ICD implantation is not recommended in asymptomatic patients with an isolated ERP. III C

Recommendations for management of patients with catecholaminergic polymorphic ventricular tachycardia It is recommended that CPVT is diagnosed in the presence of a structurally normal heart, normal ECG, and exercise- or emotion-induced bidirectional or PVT. I C It is recommended that CPVT is diagnosed in patients who are carriers of a mutation in disease-causing genes. I C

Genetic testing and genetic counselling are indicated in patients with clinical suspicion or clinical diagnosis of CPVT. I C

Avoidance of competitive sports, strenuous exercise, and exposure to stressful environments is recommended in all patients with CPVT. I C Beta-blockers, ideally non-selective (nadolol or propranolol), are recommended in all patients with a clinical diagnosis of CPVT. I C

ICD implantation combined with beta-blockers and flecainide is recommended in CPVT patients after aborted CA. I C

PES is not recommended for stratification of SCD risk. III C

Continued Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026