p.101 抽出テキスト
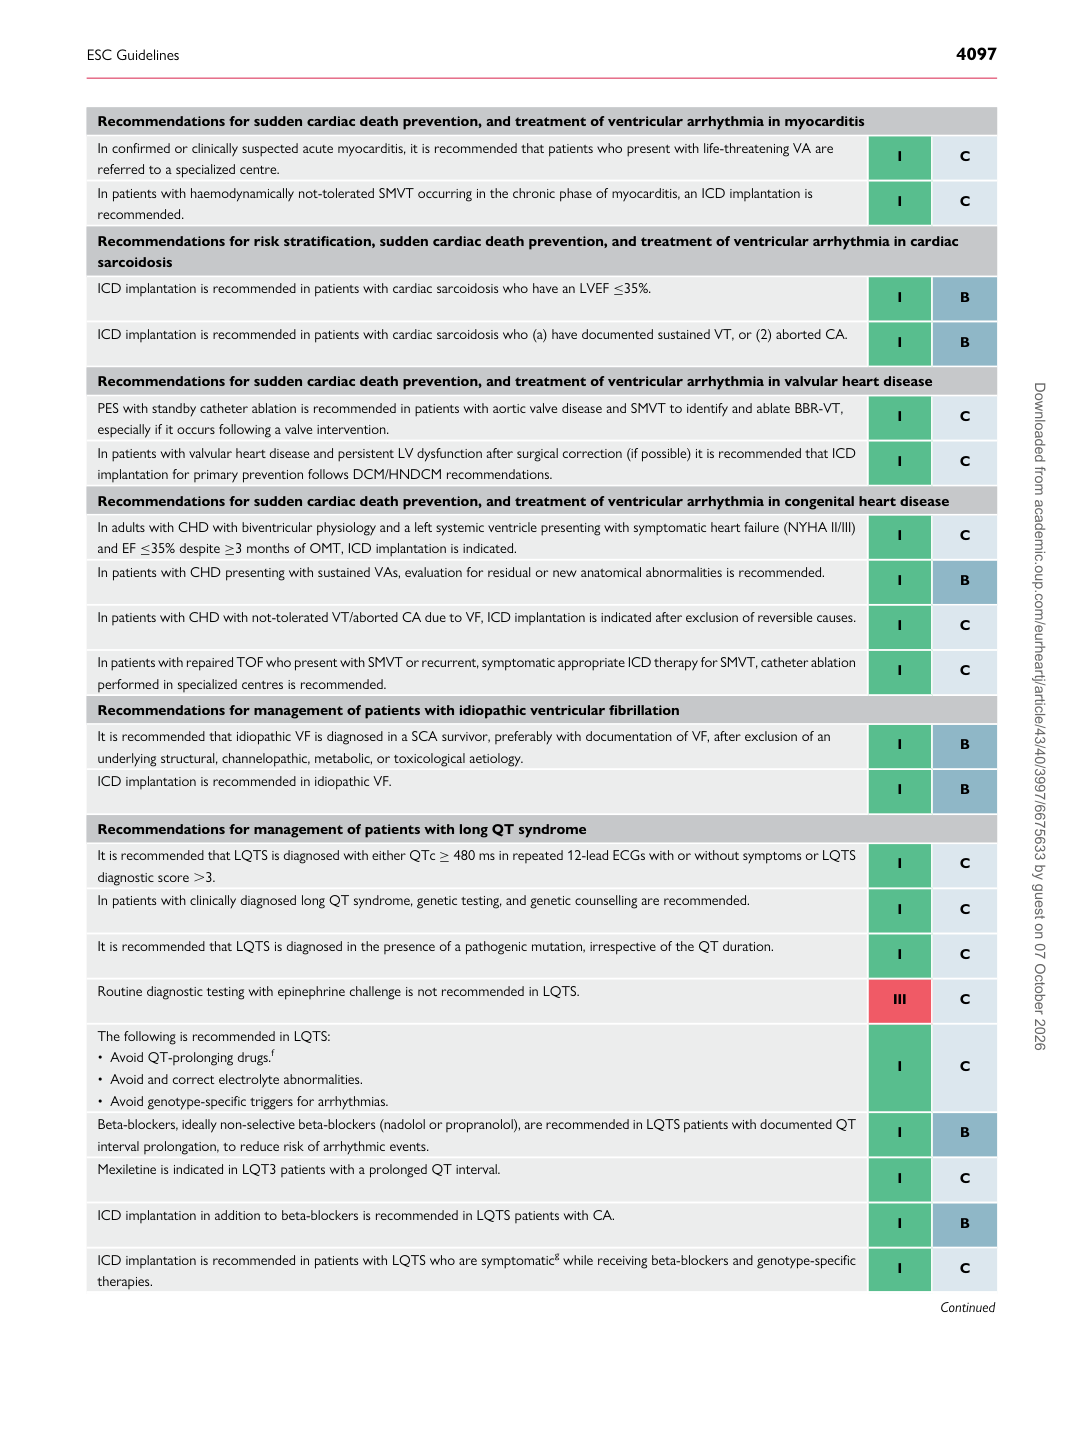
Recommendations for sudden cardiac death prevention, and treatment of ventricular arrhythmia in myocarditis In confirmed or clinically suspected acute myocarditis, it is recommended that patients who present with life-threatening VA are referred to a specialized centre. I C In patients with haemodynamically not-tolerated SMVT occurring in the chronic phase of myocarditis, an ICD implantation is recommended. I C Recommendations for risk stratification, sudden cardiac death prevention, and treatment of ventricular arrhythmia in cardiac sarcoidosis ICD implantation is recommended in patients with cardiac sarcoidosis who have an LVEF ≤35%. I B

ICD implantation is recommended in patients with cardiac sarcoidosis who (a) have documented sustained VT, or (2) aborted CA. I B

Recommendations for sudden cardiac death prevention, and treatment of ventricular arrhythmia in valvular heart disease PES with standby catheter ablation is recommended in patients with aortic valve disease and SMVT to identify and ablate BBR-VT, especially if it occurs following a valve intervention. I C In patients with valvular heart disease and persistent LV dysfunction after surgical correction (if possible) it is recommended that ICD implantation for primary prevention follows DCM/HNDCM recommendations. I C Recommendations for sudden cardiac death prevention, and treatment of ventricular arrhythmia in congenital heart disease In adults with CHD with biventricular physiology and a left systemic ventricle presenting with symptomatic heart failure (NYHA II/III) and EF ≤35% despite ≥3 months of OMT, ICD implantation is indicated. I C In patients with CHD presenting with sustained VAs, evaluation for residual or new anatomical abnormalities is recommended. I B

In patients with CHD with not-tolerated VT/aborted CA due to VF, ICD implantation is indicated after exclusion of reversible causes. I C

In patients with repaired TOF who present with SMVT or recurrent, symptomatic appropriate ICD therapy for SMVT, catheter ablation performed in specialized centres is recommended. I C Recommendations for management of patients with idiopathic ventricular fibrillation It is recommended that idiopathic VF is diagnosed in a SCA survivor, preferably with documentation of VF, after exclusion of an underlying structural, channelopathic, metabolic, or toxicological aetiology. I B ICD implantation is recommended in idiopathic VF. I B

Recommendations for management of patients with long QT syndrome It is recommended that LQTS is diagnosed with either QTc ≥480 ms in repeated 12-lead ECGs with or without symptoms or LQTS diagnostic score .3. I C In patients with clinically diagnosed long QT syndrome, genetic testing, and genetic counselling are recommended. I C

It is recommended that LQTS is diagnosed in the presence of a pathogenic mutation, irrespective of the QT duration. I C

Routine diagnostic testing with epinephrine challenge is not recommended in LQTS. III C

The following is recommended in LQTS: • Avoid QT-prolonging drugs.f • Avoid and correct electrolyte abnormalities. • Avoid genotype-specific triggers for arrhythmias. I C Beta-blockers, ideally non-selective beta-blockers (nadolol or propranolol), are recommended in LQTS patients with documented QT interval prolongation, to reduce risk of arrhythmic events. I B Mexiletine is indicated in LQT3 patients with a prolonged QT interval. I C

ICD implantation in addition to beta-blockers is recommended in LQTS patients with CA. I B

ICD implantation is recommended in patients with LQTS who are symptomaticg while receiving beta-blockers and genotype-specific therapies. I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026