p.100 抽出テキスト
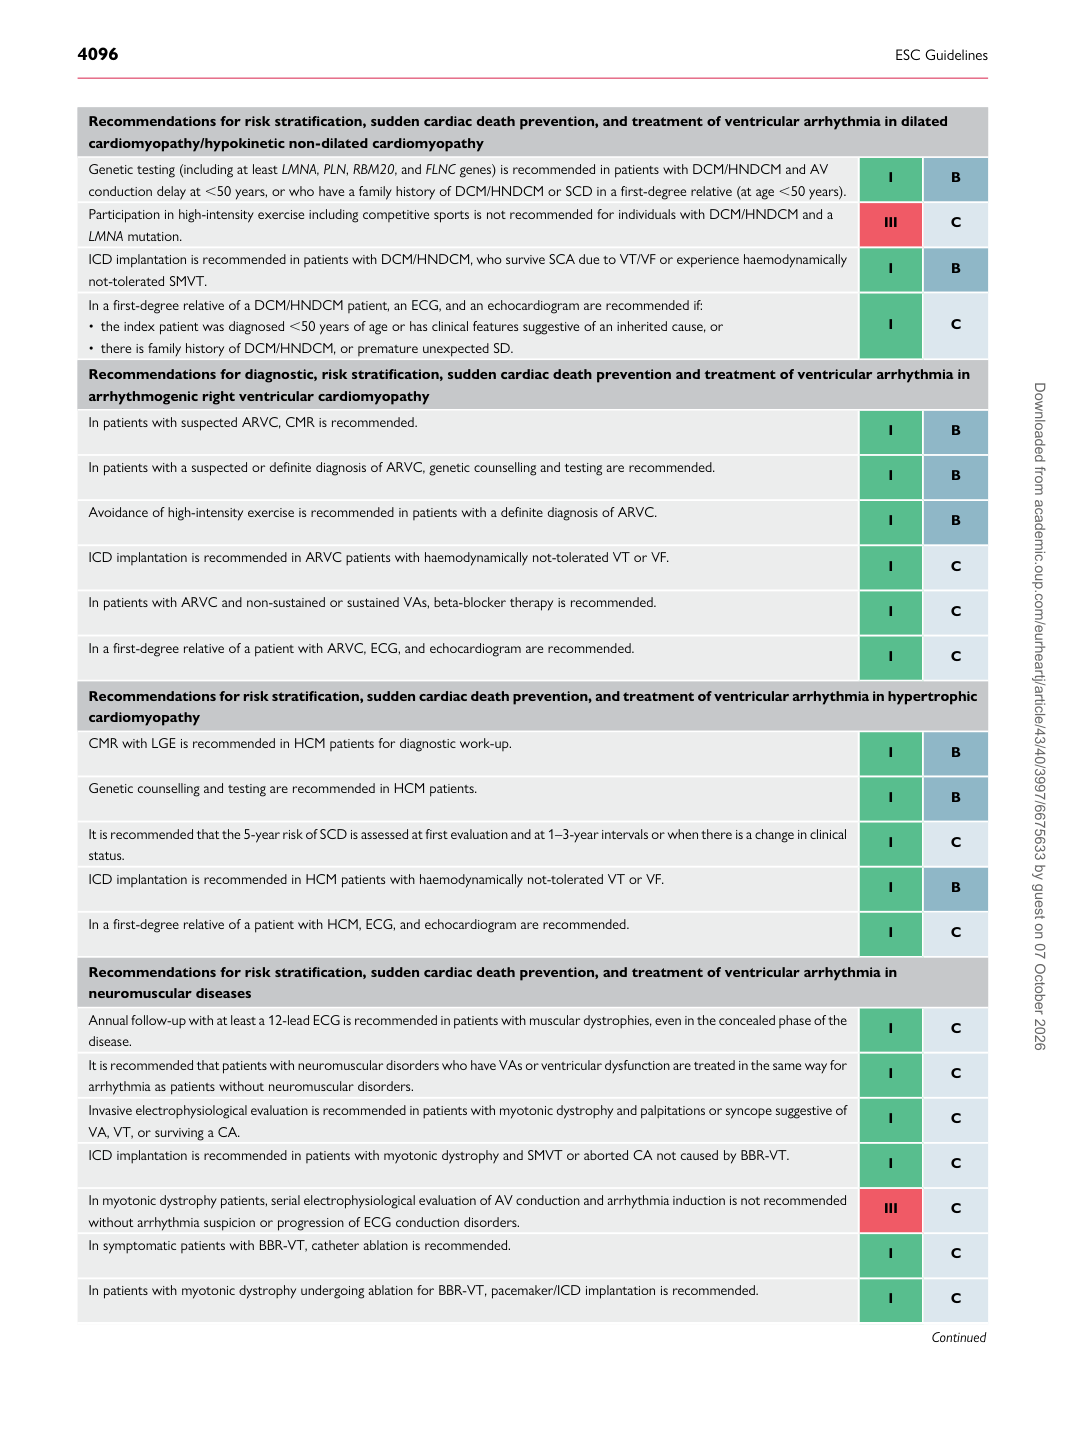
Recommendations for risk stratification, sudden cardiac death prevention, and treatment of ventricular arrhythmia in dilated cardiomyopathy/hypokinetic non-dilated cardiomyopathy Genetic testing (including at least LMNA, PLN, RBM20, and FLNC genes) is recommended in patients with DCM/HNDCM and AV conduction delay at ,50 years, or who have a family history of DCM/HNDCM or SCD in a first-degree relative (at age ,50 years). I B Participation in high-intensity exercise including competitive sports is not recommended for individuals with DCM/HNDCM and a LMNA mutation. III C ICD implantation is recommended in patients with DCM/HNDCM, who survive SCA due to VT/VF or experience haemodynamically not-tolerated SMVT. I B In a first-degree relative of a DCM/HNDCM patient, an ECG, and an echocardiogram are recommended if: • the index patient was diagnosed ,50 years of age or has clinical features suggestive of an inherited cause, or • there is family history of DCM/HNDCM, or premature unexpected SD. I C Recommendations for diagnostic, risk stratification, sudden cardiac death prevention and treatment of ventricular arrhythmia in arrhythmogenic right ventricular cardiomyopathy In patients with suspected ARVC, CMR is recommended. I B

In patients with a suspected or definite diagnosis of ARVC, genetic counselling and testing are recommended. I B

Avoidance of high-intensity exercise is recommended in patients with a definite diagnosis of ARVC. I B

ICD implantation is recommended in ARVC patients with haemodynamically not-tolerated VT or VF. I C

In patients with ARVC and non-sustained or sustained VAs, beta-blocker therapy is recommended. I C

In a first-degree relative of a patient with ARVC, ECG, and echocardiogram are recommended. I C

Recommendations for risk stratification, sudden cardiac death prevention, and treatment of ventricular arrhythmia in hypertrophic cardiomyopathy CMR with LGE is recommended in HCM patients for diagnostic work-up. I B

Genetic counselling and testing are recommended in HCM patients. I B

It is recommended that the 5-year risk of SCD is assessed at first evaluation and at 1–3-year intervals or when there is a change in clinical status. I C ICD implantation is recommended in HCM patients with haemodynamically not-tolerated VT or VF. I B

In a first-degree relative of a patient with HCM, ECG, and echocardiogram are recommended. I C

Recommendations for risk stratification, sudden cardiac death prevention, and treatment of ventricular arrhythmia in neuromuscular diseases Annual follow-up with at least a 12-lead ECG is recommended in patients with muscular dystrophies, even in the concealed phase of the disease. I C It is recommended that patients with neuromuscular disorders who have VAs or ventricular dysfunction are treated in the same way for arrhythmia as patients without neuromuscular disorders. I C Invasive electrophysiological evaluation is recommended in patients with myotonic dystrophy and palpitations or syncope suggestive of VA, VT, or surviving a CA. I C ICD implantation is recommended in patients with myotonic dystrophy and SMVT or aborted CA not caused by BBR-VT. I C

In myotonic dystrophy patients, serial electrophysiological evaluation of AV conduction and arrhythmia induction is not recommended without arrhythmia suspicion or progression of ECG conduction disorders. III C In symptomatic patients with BBR-VT, catheter ablation is recommended. I C

In patients with myotonic dystrophy undergoing ablation for BBR-VT, pacemaker/ICD implantation is recommended. I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/40/3997/6675633 by guest on 07 October 2026