p.92 抽出テキスト
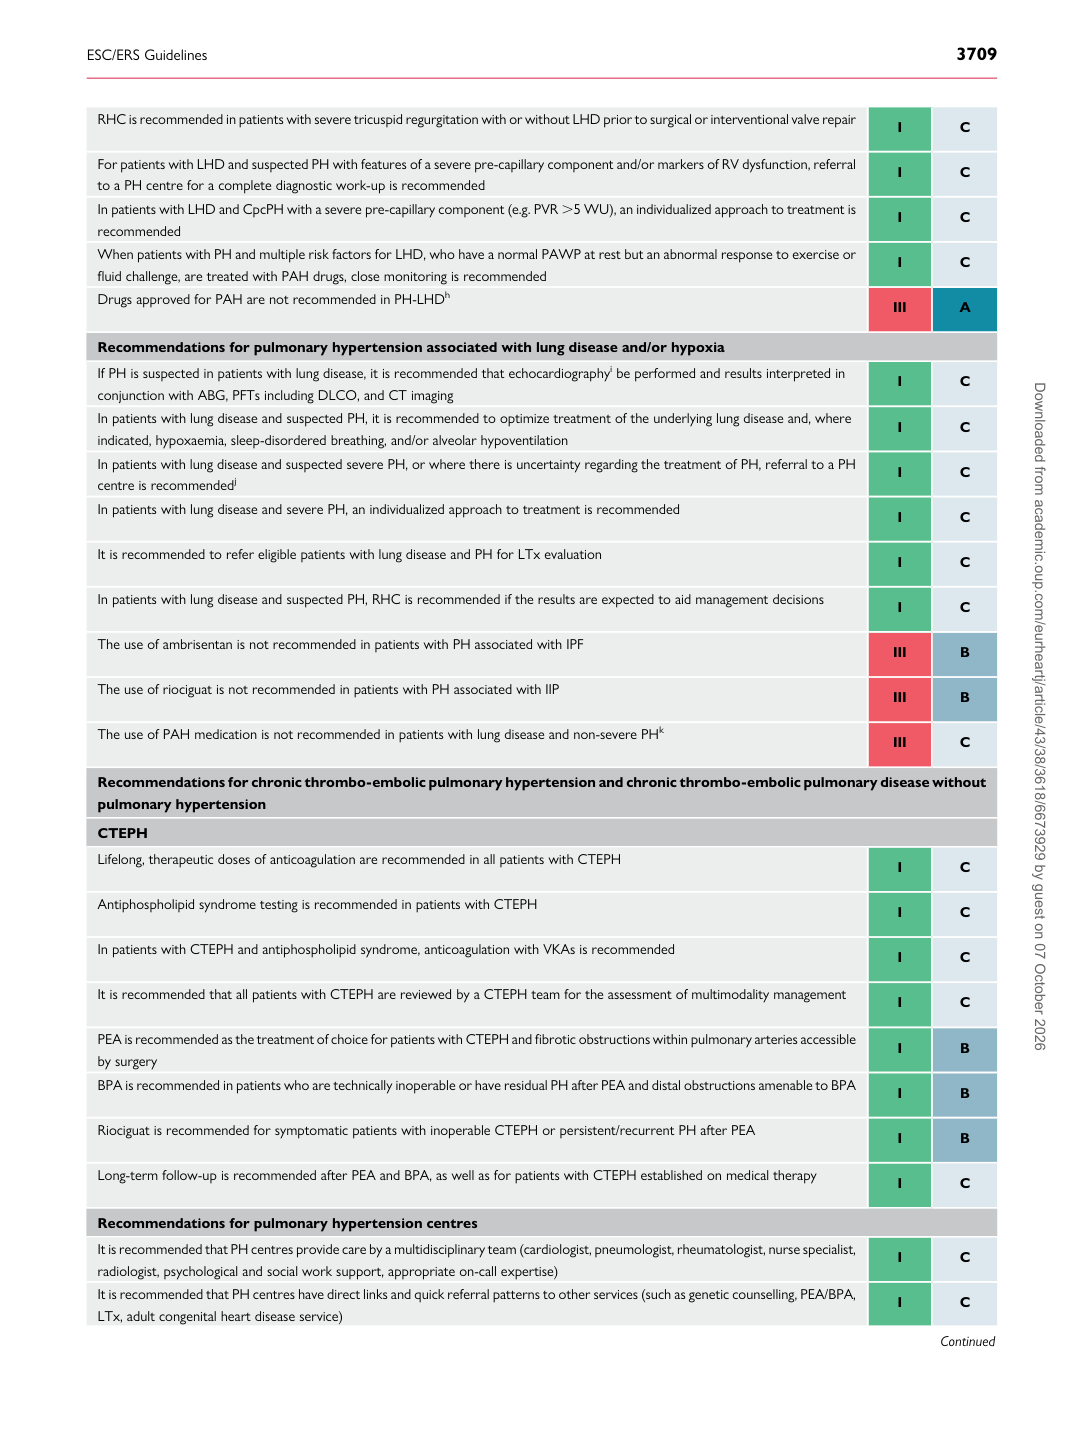
RHC is recommended in patients with severe tricuspid regurgitation with or without LHD prior to surgical or interventional valve repair I C

For patients with LHD and suspected PH with features of a severe pre-capillary component and/or markers of RV dysfunction, referral to a PH centre for a complete diagnostic work-up is recommended I C In patients with LHD and CpcPH with a severe pre-capillary component (e.g. PVR .5 WU), an individualized approach to treatment is recommended I C When patients with PH and multiple risk factors for LHD, who have a normal PAWP at rest but an abnormal response to exercise or fluid challenge, are treated with PAH drugs, close monitoring is recommended I C Drugs approved for PAH are not recommended in PH-LHDh III A

Recommendations for pulmonary hypertension associated with lung disease and/or hypoxia If PH is suspected in patients with lung disease, it is recommended that echocardiographyi be performed and results interpreted in conjunction with ABG, PFTs including DLCO, and CT imaging I C In patients with lung disease and suspected PH, it is recommended to optimize treatment of the underlying lung disease and, where indicated, hypoxaemia, sleep-disordered breathing, and/or alveolar hypoventilation I C In patients with lung disease and suspected severe PH, or where there is uncertainty regarding the treatment of PH, referral to a PH centre is recommendedj I C In patients with lung disease and severe PH, an individualized approach to treatment is recommended I C

It is recommended to refer eligible patients with lung disease and PH for LTx evaluation I C

In patients with lung disease and suspected PH, RHC is recommended if the results are expected to aid management decisions I C

The use of ambrisentan is not recommended in patients with PH associated with IPF III B

The use of riociguat is not recommended in patients with PH associated with IIP III B

The use of PAH medication is not recommended in patients with lung disease and non-severe PHk III C

Recommendations for chronic thrombo-embolic pulmonary hypertension and chronic thrombo-embolic pulmonary disease without pulmonary hypertension CTEPH Lifelong, therapeutic doses of anticoagulation are recommended in all patients with CTEPH I C

Antiphospholipid syndrome testing is recommended in patients with CTEPH I C

In patients with CTEPH and antiphospholipid syndrome, anticoagulation with VKAs is recommended I C

It is recommended that all patients with CTEPH are reviewed by a CTEPH team for the assessment of multimodality management I C

PEA is recommended as the treatment of choice for patients with CTEPH and fibrotic obstructions within pulmonary arteries accessible by surgery I B BPA is recommended in patients who are technically inoperable or have residual PH after PEA and distal obstructions amenable to BPA I B

Riociguat is recommended for symptomatic patients with inoperable CTEPH or persistent/recurrent PH after PEA I B

Long-term follow-up is recommended after PEA and BPA, as well as for patients with CTEPH established on medical therapy I C

Recommendations for pulmonary hypertension centres It is recommended that PH centres provide care by a multidisciplinary team (cardiologist, pneumologist, rheumatologist, nurse specialist, radiologist, psychological and social work support, appropriate on-call expertise) I C It is recommended that PH centres have direct links and quick referral patterns to other services (such as genetic counselling, PEA/BPA, LTx, adult congenital heart disease service) I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026