p.91 抽出テキスト
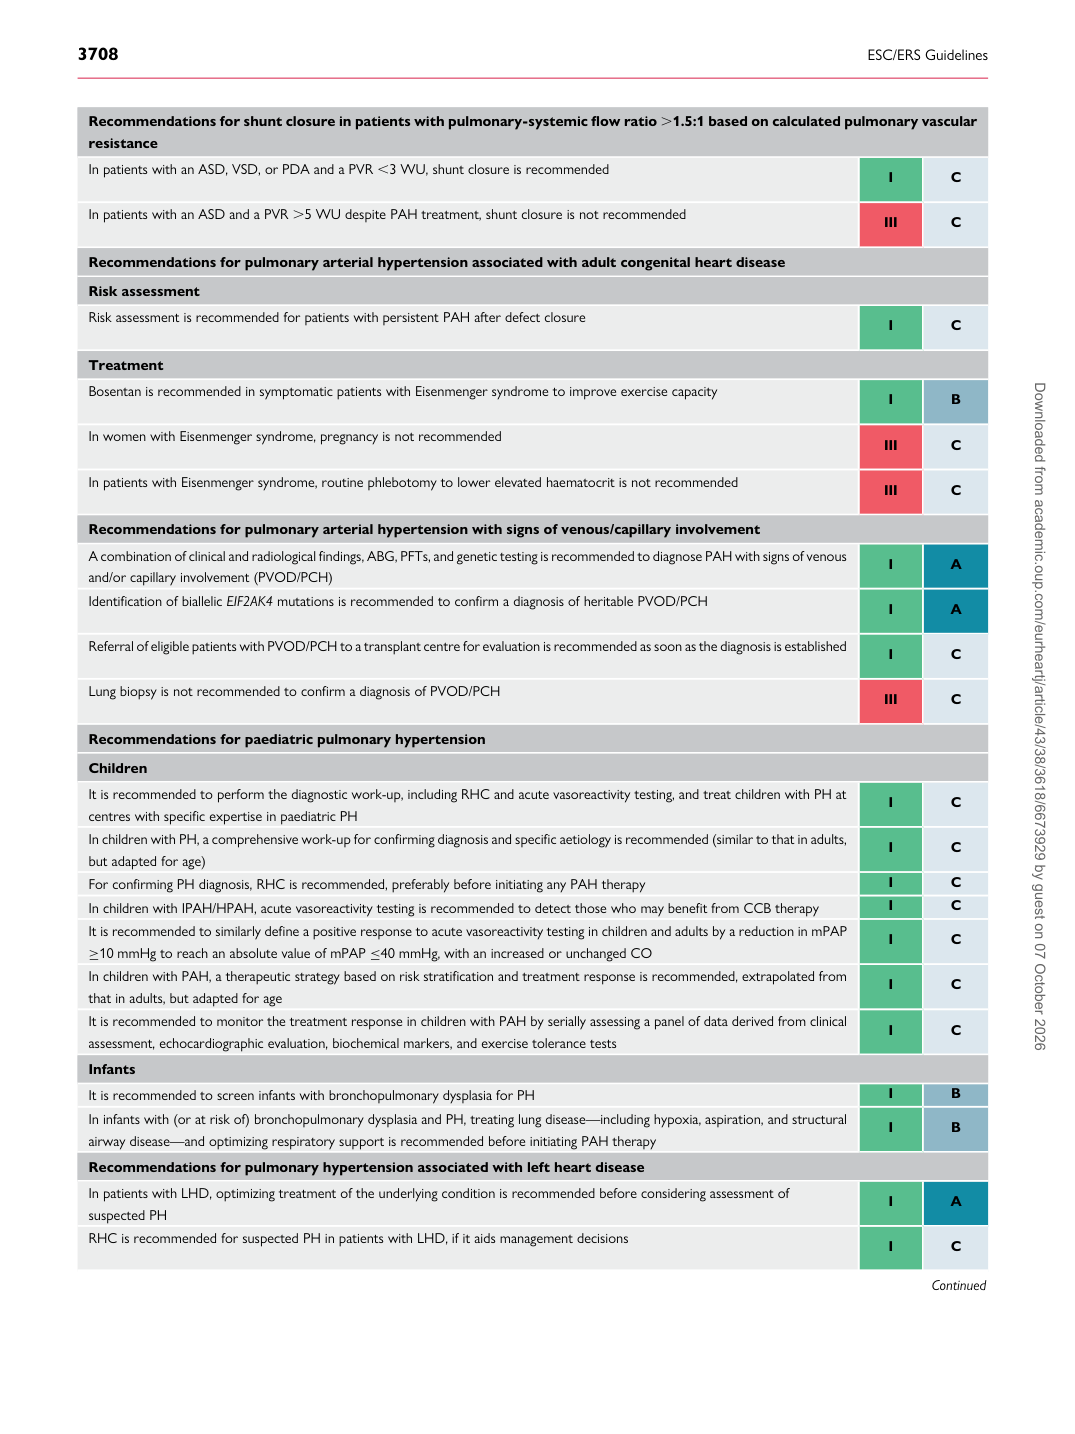
Recommendations for shunt closure in patients with pulmonary-systemic flow ratio .1.5:1 based on calculated pulmonary vascular resistance In patients with an ASD, VSD, or PDA and a PVR ,3 WU, shunt closure is recommended I C

In patients with an ASD and a PVR .5 WU despite PAH treatment, shunt closure is not recommended III C

Recommendations for pulmonary arterial hypertension associated with adult congenital heart disease Risk assessment Risk assessment is recommended for patients with persistent PAH after defect closure I C

Treatment Bosentan is recommended in symptomatic patients with Eisenmenger syndrome to improve exercise capacity I B

In women with Eisenmenger syndrome, pregnancy is not recommended III C

In patients with Eisenmenger syndrome, routine phlebotomy to lower elevated haematocrit is not recommended III C

Recommendations for pulmonary arterial hypertension with signs of venous/capillary involvement A combination of clinical and radiological findings, ABG, PFTs, and genetic testing is recommended to diagnose PAH with signs of venous and/or capillary involvement (PVOD/PCH) I A Identification of biallelic EIF2AK4 mutations is recommended to confirm a diagnosis of heritable PVOD/PCH I A

Referral of eligible patients with PVOD/PCH to a transplant centre for evaluation is recommended as soon as the diagnosis is established I C

Lung biopsy is not recommended to confirm a diagnosis of PVOD/PCH III C

Recommendations for paediatric pulmonary hypertension Children It is recommended to perform the diagnostic work-up, including RHC and acute vasoreactivity testing, and treat children with PH at centres with specific expertise in paediatric PH I C In children with PH, a comprehensive work-up for confirming diagnosis and specific aetiology is recommended (similar to that in adults, but adapted for age) I C For confirming PH diagnosis, RHC is recommended, preferably before initiating any PAH therapy I C In children with IPAH/HPAH, acute vasoreactivity testing is recommended to detect those who may benefit from CCB therapy I C It is recommended to similarly define a positive response to acute vasoreactivity testing in children and adults by a reduction in mPAP ≥10 mmHg to reach an absolute value of mPAP ≤40 mmHg, with an increased or unchanged CO I C In children with PAH, a therapeutic strategy based on risk stratification and treatment response is recommended, extrapolated from that in adults, but adapted for age I C It is recommended to monitor the treatment response in children with PAH by serially assessing a panel of data derived from clinical assessment, echocardiographic evaluation, biochemical markers, and exercise tolerance tests I C Infants It is recommended to screen infants with bronchopulmonary dysplasia for PH I B In infants with (or at risk of) bronchopulmonary dysplasia and PH, treating lung disease—including hypoxia, aspiration, and structural airway disease—and optimizing respiratory support is recommended before initiating PAH therapy I B Recommendations for pulmonary hypertension associated with left heart disease In patients with LHD, optimizing treatment of the underlying condition is recommended before considering assessment of suspected PH I A RHC is recommended for suspected PH in patients with LHD, if it aids management decisions I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026