p.90 抽出テキスト
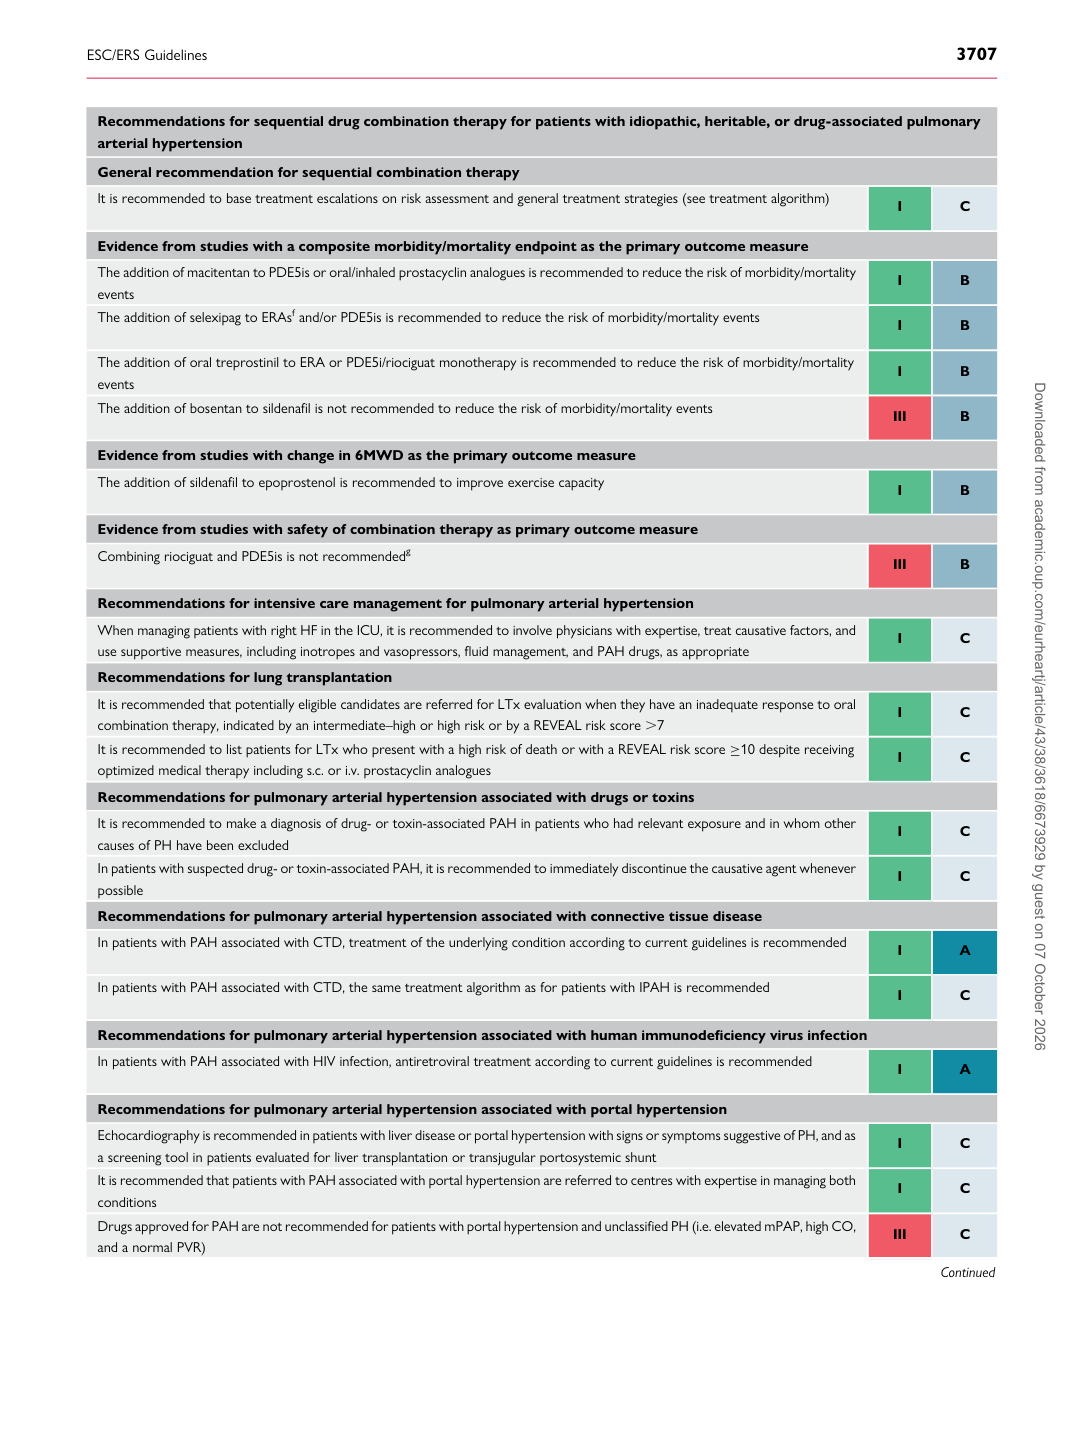
Recommendations for sequential drug combination therapy for patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension General recommendation for sequential combination therapy It is recommended to base treatment escalations on risk assessment and general treatment strategies (see treatment algorithm) I C

Evidence from studies with a composite morbidity/mortality endpoint as the primary outcome measure The addition of macitentan to PDE5is or oral/inhaled prostacyclin analogues is recommended to reduce the risk of morbidity/mortality events I B The addition of selexipag to ERAsf and/or PDE5is is recommended to reduce the risk of morbidity/mortality events I B

The addition of oral treprostinil to ERA or PDE5i/riociguat monotherapy is recommended to reduce the risk of morbidity/mortality events I B The addition of bosentan to sildenafil is not recommended to reduce the risk of morbidity/mortality events III B

Evidence from studies with change in 6MWD as the primary outcome measure The addition of sildenafil to epoprostenol is recommended to improve exercise capacity I B

Evidence from studies with safety of combination therapy as primary outcome measure Combining riociguat and PDE5is is not recommendedg III B

Recommendations for intensive care management for pulmonary arterial hypertension When managing patients with right HF in the ICU, it is recommended to involve physicians with expertise, treat causative factors, and use supportive measures, including inotropes and vasopressors, fluid management, and PAH drugs, as appropriate I C Recommendations for lung transplantation It is recommended that potentially eligible candidates are referred for LTx evaluation when they have an inadequate response to oral combination therapy, indicated by an intermediate–high or high risk or by a REVEAL risk score .7 I C It is recommended to list patients for LTx who present with a high risk of death or with a REVEAL risk score ≥10 despite receiving optimized medical therapy including s.c. or i.v. prostacyclin analogues I C Recommendations for pulmonary arterial hypertension associated with drugs or toxins It is recommended to make a diagnosis of drug- or toxin-associated PAH in patients who had relevant exposure and in whom other causes of PH have been excluded I C In patients with suspected drug- or toxin-associated PAH, it is recommended to immediately discontinue the causative agent whenever possible I C Recommendations for pulmonary arterial hypertension associated with connective tissue disease In patients with PAH associated with CTD, treatment of the underlying condition according to current guidelines is recommended I A

In patients with PAH associated with CTD, the same treatment algorithm as for patients with IPAH is recommended I C

Recommendations for pulmonary arterial hypertension associated with human immunodeficiency virus infection In patients with PAH associated with HIV infection, antiretroviral treatment according to current guidelines is recommended I A

Recommendations for pulmonary arterial hypertension associated with portal hypertension Echocardiography is recommended in patients with liver disease or portal hypertension with signs or symptoms suggestive of PH, and as a screening tool in patients evaluated for liver transplantation or transjugular portosystemic shunt I C It is recommended that patients with PAH associated with portal hypertension are referred to centres with expertise in managing both conditions I C Drugs approved for PAH are not recommended for patients with portal hypertension and unclassified PH (i.e. elevated mPAP, high CO, and a normal PVR) III C

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026