p.9 抽出テキスト
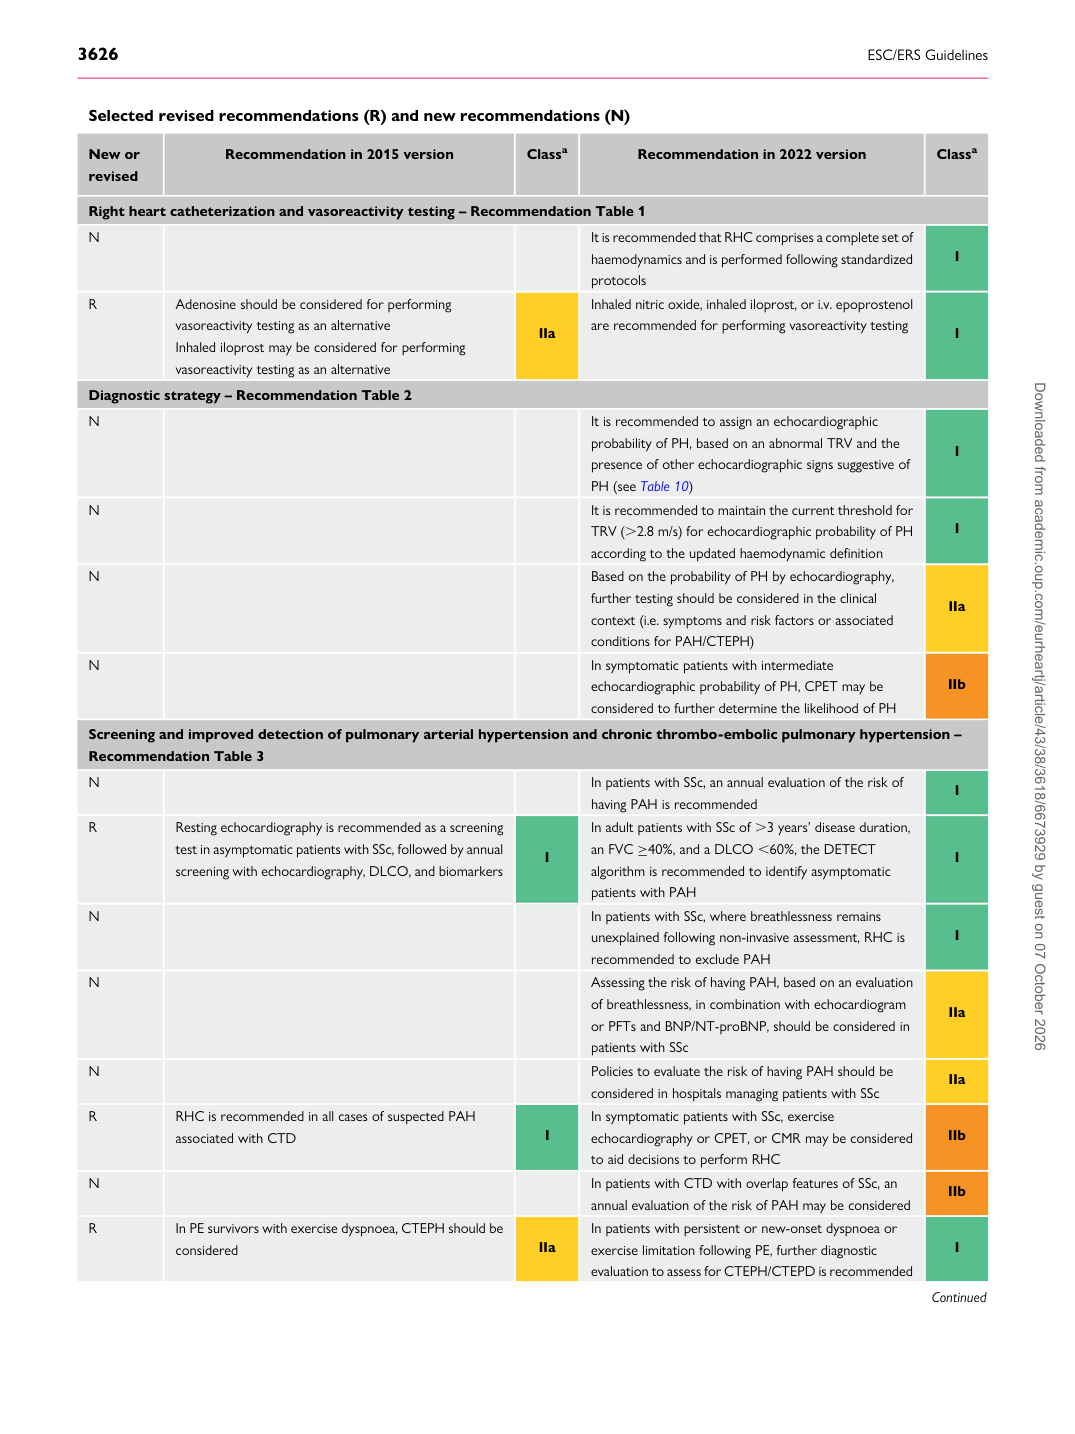
Selected revised recommendations (R) and new recommendations (N)

New or revised Recommendation in 2015 version Classa Recommendation in 2022 version Classa

Right heart catheterization and vasoreactivity testing – Recommendation Table 1 N It is recommended that RHC comprises a complete set of haemodynamics and is performed following standardized

protocols I

R Adenosine should be considered for performing

vasoreactivity testing as an alternative Inhaled iloprost may be considered for performing vasoreactivity testing as an alternative IIa Inhaled nitric oxide, inhaled iloprost, or i.v. epoprostenol

are recommended for performing vasoreactivity testing I

Diagnostic strategy – Recommendation Table 2 N It is recommended to assign an echocardiographic probability of PH, based on an abnormal TRV and the

presence of other echocardiographic signs suggestive of PH (see Table 10) I

N It is recommended to maintain the current threshold for

TRV (.2.8 m/s) for echocardiographic probability of PH according to the updated haemodynamic definition I

N Based on the probability of PH by echocardiography, further testing should be considered in the clinical

context (i.e. symptoms and risk factors or associated conditions for PAH/CTEPH) IIa

N In symptomatic patients with intermediate

echocardiographic probability of PH, CPET may be considered to further determine the likelihood of PH IIb

Screening and improved detection of pulmonary arterial hypertension and chronic thrombo-embolic pulmonary hypertension – Recommendation Table 3 N In patients with SSc, an annual evaluation of the risk of having PAH is recommended I R Resting echocardiography is recommended as a screening

test in asymptomatic patients with SSc, followed by annual screening with echocardiography, DLCO, and biomarkers I In adult patients with SSc of .3 years’ disease duration,

an FVC ≥40%, and a DLCO ,60%, the DETECT algorithm is recommended to identify asymptomatic patients with PAH I

N In patients with SSc, where breathlessness remains unexplained following non-invasive assessment, RHC is

recommended to exclude PAH I

N Assessing the risk of having PAH, based on an evaluation

of breathlessness, in combination with echocardiogram or PFTs and BNP/NT-proBNP, should be considered in patients with SSc IIa

N Policies to evaluate the risk of having PAH should be considered in hospitals managing patients with SSc IIa R RHC is recommended in all cases of suspected PAH associated with CTD I In symptomatic patients with SSc, exercise echocardiography or CPET, or CMR may be considered

to aid decisions to perform RHC IIb

N In patients with CTD with overlap features of SSc, an

annual evaluation of the risk of PAH may be considered IIb

R In PE survivors with exercise dyspnoea, CTEPH should be

considered IIa In patients with persistent or new-onset dyspnoea or

exercise limitation following PE, further diagnostic evaluation to assess for CTEPH/CTEPD is recommended I

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026