p.89 抽出テキスト
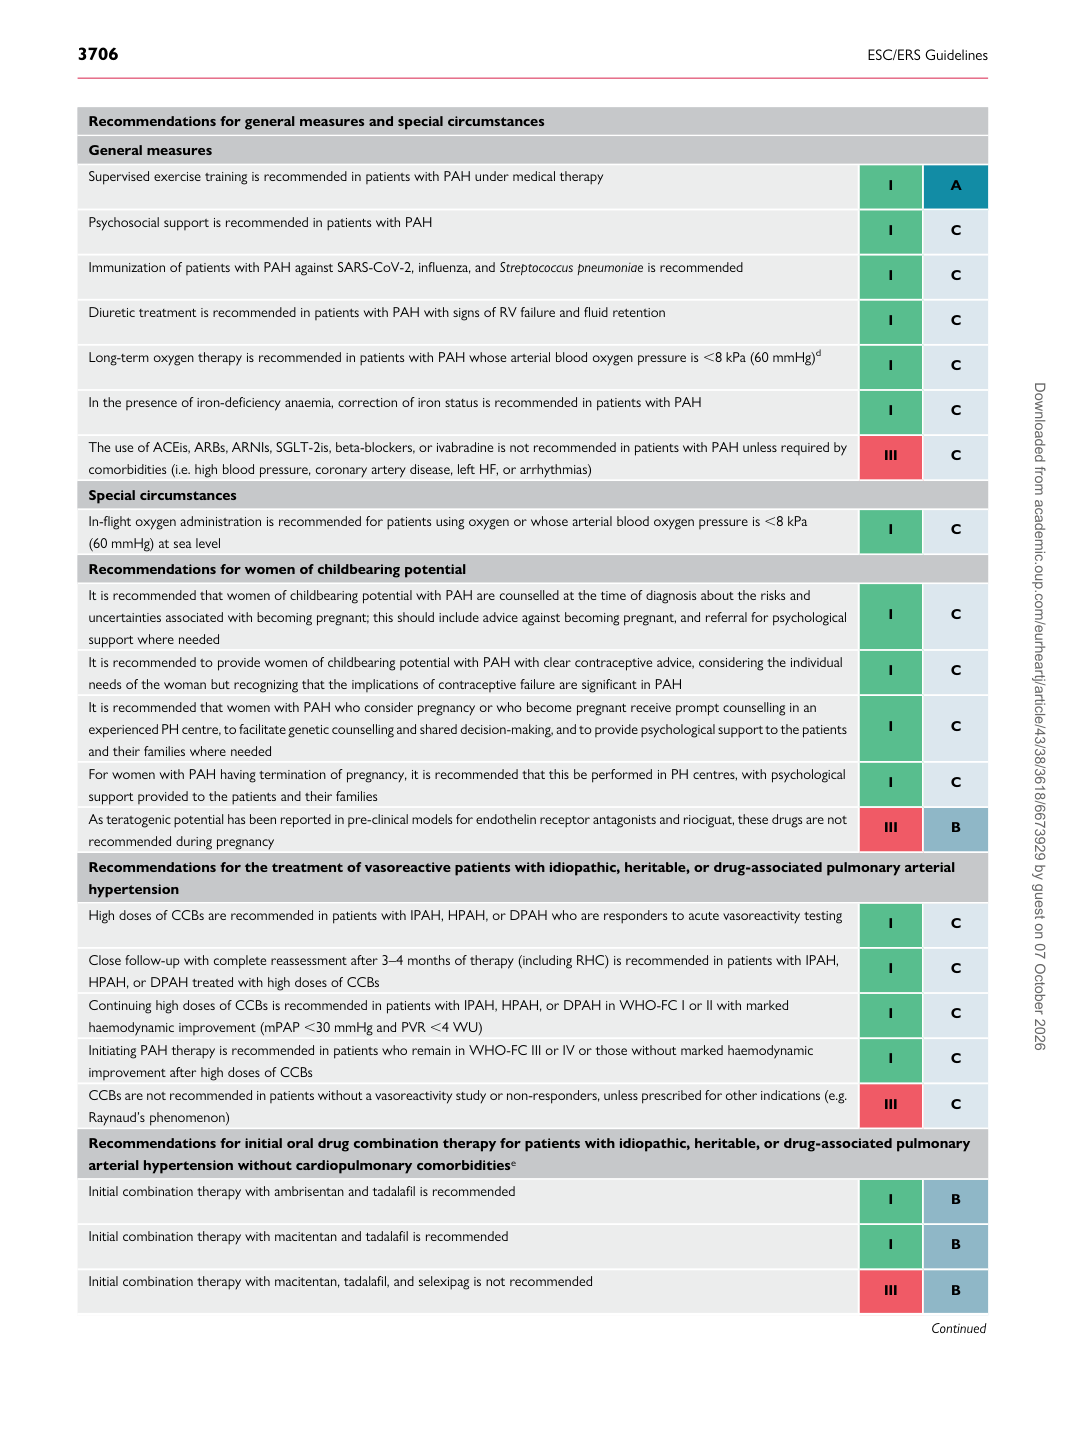
Recommendations for general measures and special circumstances General measures Supervised exercise training is recommended in patients with PAH under medical therapy I A

Psychosocial support is recommended in patients with PAH I C

Immunization of patients with PAH against SARS-CoV-2, influenza, and Streptococcus pneumoniae is recommended I C

Diuretic treatment is recommended in patients with PAH with signs of RV failure and fluid retention I C

Long-term oxygen therapy is recommended in patients with PAH whose arterial blood oxygen pressure is ,8 kPa (60 mmHg)d I C

In the presence of iron-deficiency anaemia, correction of iron status is recommended in patients with PAH I C

The use of ACEis, ARBs, ARNIs, SGLT-2is, beta-blockers, or ivabradine is not recommended in patients with PAH unless required by comorbidities (i.e. high blood pressure, coronary artery disease, left HF, or arrhythmias) III C Special circumstances In-flight oxygen administration is recommended for patients using oxygen or whose arterial blood oxygen pressure is ,8 kPa (60 mmHg) at sea level I C Recommendations for women of childbearing potential It is recommended that women of childbearing potential with PAH are counselled at the time of diagnosis about the risks and uncertainties associated with becoming pregnant; this should include advice against becoming pregnant, and referral for psychological support where needed I C It is recommended to provide women of childbearing potential with PAH with clear contraceptive advice, considering the individual needs of the woman but recognizing that the implications of contraceptive failure are significant in PAH I C It is recommended that women with PAH who consider pregnancy or who become pregnant receive prompt counselling in an experienced PH centre, to facilitate genetic counselling and shared decision-making, and to provide psychological support to the patients and their families where needed I C For women with PAH having termination of pregnancy, it is recommended that this be performed in PH centres, with psychological support provided to the patients and their families I C As teratogenic potential has been reported in pre-clinical models for endothelin receptor antagonists and riociguat, these drugs are not recommended during pregnancy III B Recommendations for the treatment of vasoreactive patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension High doses of CCBs are recommended in patients with IPAH, HPAH, or DPAH who are responders to acute vasoreactivity testing I C

Close follow-up with complete reassessment after 3–4 months of therapy (including RHC) is recommended in patients with IPAH, HPAH, or DPAH treated with high doses of CCBs I C Continuing high doses of CCBs is recommended in patients with IPAH, HPAH, or DPAH in WHO-FC I or II with marked haemodynamic improvement (mPAP ,30 mmHg and PVR ,4 WU) I C Initiating PAH therapy is recommended in patients who remain in WHO-FC III or IV or those without marked haemodynamic improvement after high doses of CCBs I C CCBs are not recommended in patients without a vasoreactivity study or non-responders, unless prescribed for other indications (e.g. Raynaud’s phenomenon) III C Recommendations for initial oral drug combination therapy for patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension without cardiopulmonary comorbiditiese Initial combination therapy with ambrisentan and tadalafil is recommended I B

Initial combination therapy with macitentan and tadalafil is recommended I B

Initial combination therapy with macitentan, tadalafil, and selexipag is not recommended III B

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026