p.88 抽出テキスト
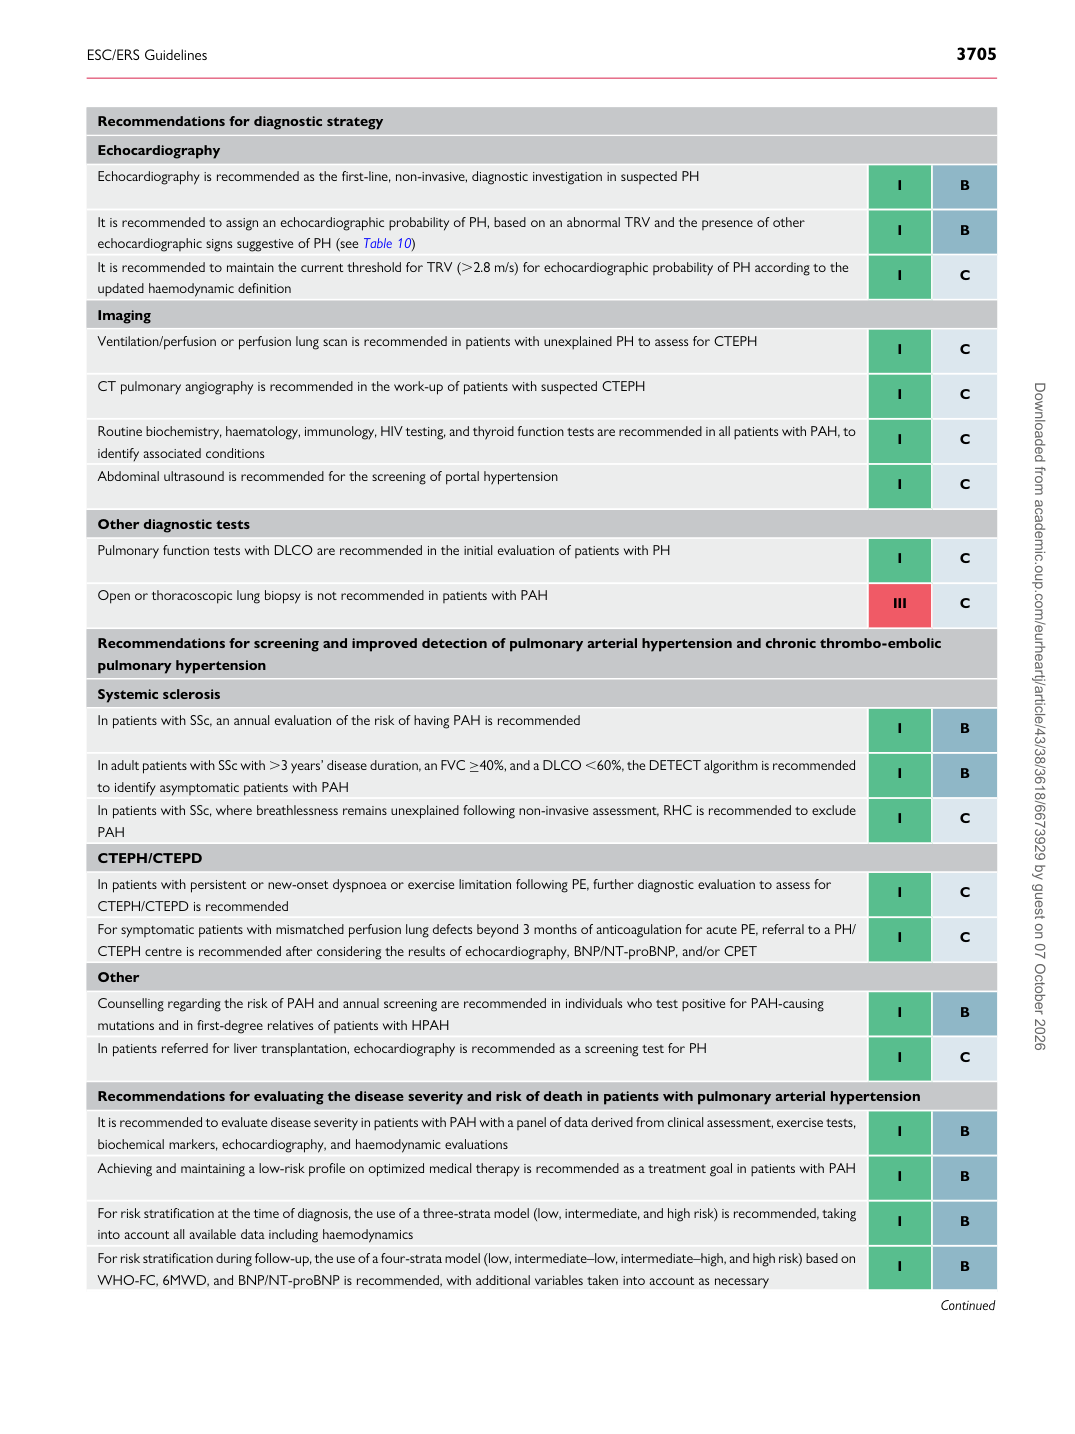
Recommendations for diagnostic strategy Echocardiography Echocardiography is recommended as the first-line, non-invasive, diagnostic investigation in suspected PH I B

It is recommended to assign an echocardiographic probability of PH, based on an abnormal TRV and the presence of other echocardiographic signs suggestive of PH (see Table 10) I B It is recommended to maintain the current threshold for TRV (.2.8 m/s) for echocardiographic probability of PH according to the updated haemodynamic definition I C Imaging Ventilation/perfusion or perfusion lung scan is recommended in patients with unexplained PH to assess for CTEPH I C

CT pulmonary angiography is recommended in the work-up of patients with suspected CTEPH I C

Routine biochemistry, haematology, immunology, HIV testing, and thyroid function tests are recommended in all patients with PAH, to identify associated conditions I C Abdominal ultrasound is recommended for the screening of portal hypertension I C

Other diagnostic tests Pulmonary function tests with DLCO are recommended in the initial evaluation of patients with PH I C

Open or thoracoscopic lung biopsy is not recommended in patients with PAH III C

Recommendations for screening and improved detection of pulmonary arterial hypertension and chronic thrombo-embolic pulmonary hypertension Systemic sclerosis In patients with SSc, an annual evaluation of the risk of having PAH is recommended I B

In adult patients with SSc with .3 years’ disease duration, an FVC ≥40%, and a DLCO ,60%, the DETECT algorithm is recommended to identify asymptomatic patients with PAH I B In patients with SSc, where breathlessness remains unexplained following non-invasive assessment, RHC is recommended to exclude PAH I C CTEPH/CTEPD In patients with persistent or new-onset dyspnoea or exercise limitation following PE, further diagnostic evaluation to assess for CTEPH/CTEPD is recommended I C For symptomatic patients with mismatched perfusion lung defects beyond 3 months of anticoagulation for acute PE, referral to a PH/ CTEPH centre is recommended after considering the results of echocardiography, BNP/NT-proBNP, and/or CPET I C Other Counselling regarding the risk of PAH and annual screening are recommended in individuals who test positive for PAH-causing mutations and in first-degree relatives of patients with HPAH I B In patients referred for liver transplantation, echocardiography is recommended as a screening test for PH I C

Recommendations for evaluating the disease severity and risk of death in patients with pulmonary arterial hypertension It is recommended to evaluate disease severity in patients with PAH with a panel of data derived from clinical assessment, exercise tests, biochemical markers, echocardiography, and haemodynamic evaluations I B Achieving and maintaining a low-risk profile on optimized medical therapy is recommended as a treatment goal in patients with PAH I B

For risk stratification at the time of diagnosis, the use of a three-strata model (low, intermediate, and high risk) is recommended, taking into account all available data including haemodynamics I B For risk stratification during follow-up, the use of a four-strata model (low, intermediate–low, intermediate–high, and high risk) based on WHO-FC, 6MWD, and BNP/NT-proBNP is recommended, with additional variables taken into account as necessary I B

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026