p.48 抽出テキスト
pulmonary endothelial cells, promoting vasodilation through accelerated production of prostacyclin and nitric oxide, and clearance of endothelin-1.380 Nevertheless, selective blocking of endothelin A receptors alone or non-selective blocking of both A and B receptors has shown similar effectiveness in PAH.380 Endothelial receptor antagonists have teratogenic effects and should not be used during pregnancy.381

6.3.3.2.1 Ambrisentan. Ambrisentan is an oral ERA that preferen-

tially blocks the endothelin A receptors. The approved dosages in adults are 5 mg and 10 mg o.d. In patients with PAH, it has demonstrated efficacy for symptoms, exercise capacity, haemodynamics, and time to clinical worsening.382 An increased incidence of peripheral oedema was reported with ambrisentan use, while there was no increased incidence of abnormal liver function.

6.3.3.2.2 Bosentan. Bosentan is an oral, dual ERA that improves

exercise capacity, WHO-FC, haemodynamics, and time to clinical worsening in patients with PAH.383 The approved target dose in adults is 125 mg b.i.d. Dose-dependent increases in liver transaminases can occur in ≏10% of treated patients (reversible after dose reduction or discontinuation).384 Thus, liver function testing should be performed monthly in patients receiving bosentan.384 Due to pharmacokinetic interactions, bosentan may render hormonal contraceptives unreliable and lower serum levels of warfarin, sildenafil, and tadalafil.361,385–387

Y

V aso

V

V r eactivity testing al g orithm in patients with p r esumed diagnosis of I/H/D- P AH and t

P

P r eatment of r esponders

Re f er to PH cent

f f r e

Reassess after 3–6 months

Conti n ue ther a p y and

p p r eassess e v e r y 6–12 months

Right hea r t catheterization with pulmona r y vaso r eactivity testing a

(Class I)

Initiate ther a p y with calcium channel bloc

p p k ers

k k

and titrate to optimized individual dose b

(Class I)

≥ 10 mmHg m P AP d

P P r op f r om baseline

to ≤ 40 mmHg with inc r eased or unchanged ca r diac output

Y Y

WH O -FC I/II, BNP <50 ng/L or N T -p

T

T r oBNP <300 ng/L,

no r mal or nea r -no r mal r esting haemodynamics c T r e a t a cc o r ding

t o F igu r e 9

N

N

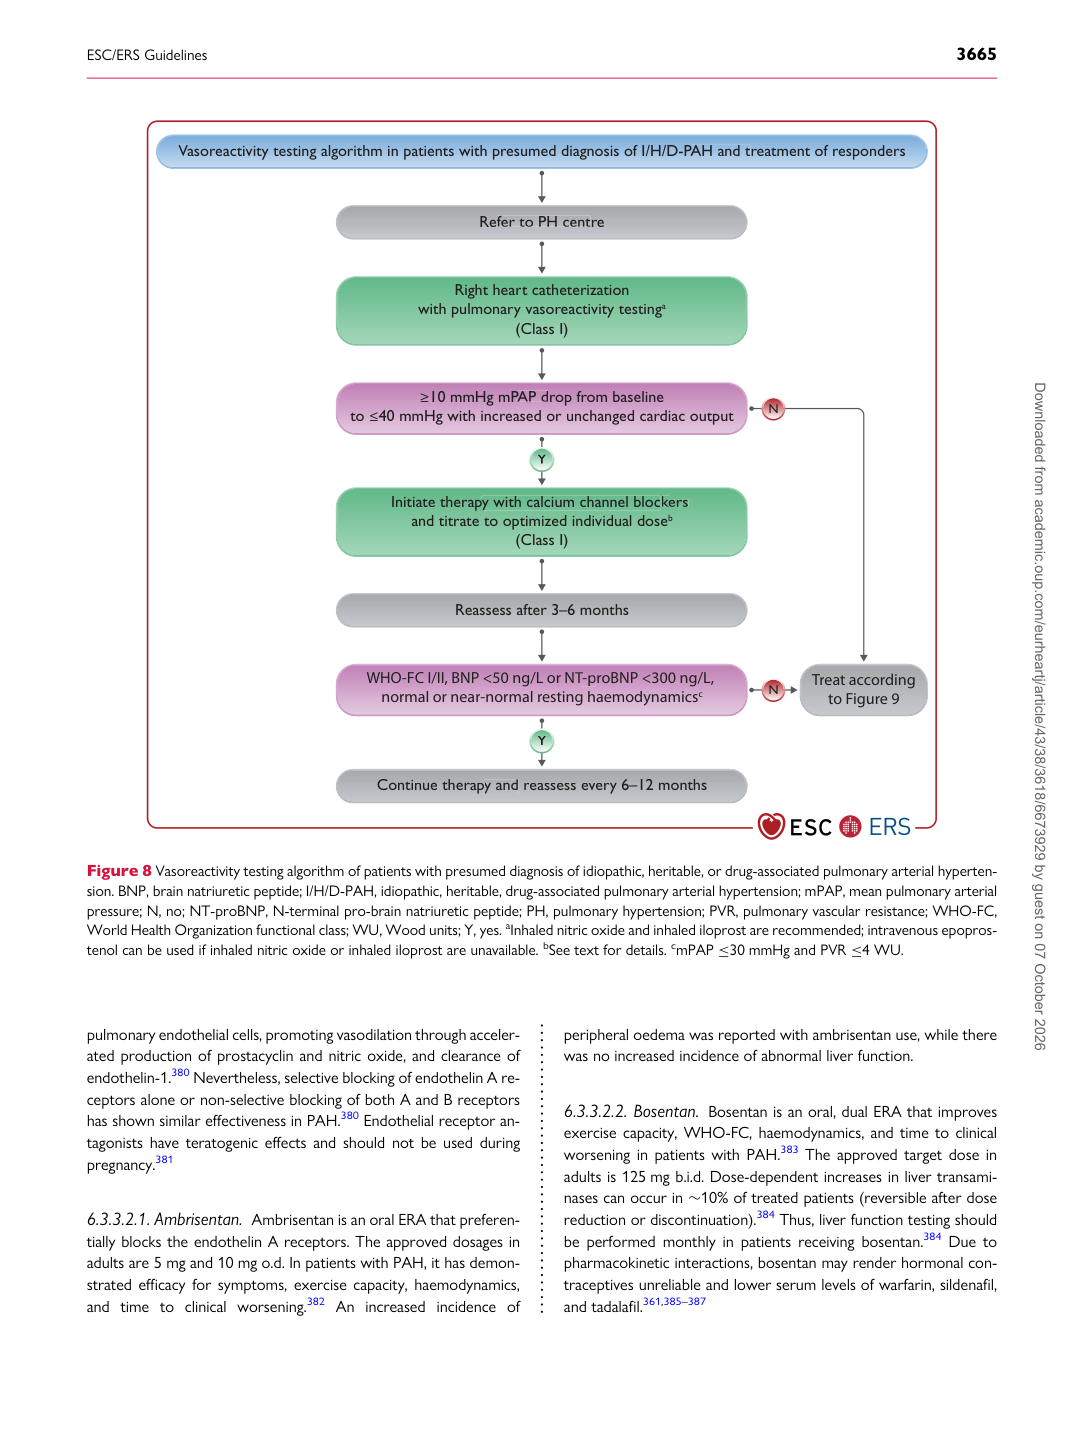
Figure 8 Vasoreactivity testing algorithm of patients with presumed diagnosis of idiopathic, heritable, or drug-associated pulmonary arterial hypertension. BNP, brain natriuretic peptide; I/H/D-PAH, idiopathic, heritable, drug-associated pulmonary arterial hypertension; mPAP, mean pulmonary arterial pressure; N, no; NT-proBNP, N-terminal pro-brain natriuretic peptide; PH, pulmonary hypertension; PVR, pulmonary vascular resistance; WHO-FC, World Health Organization functional class; WU, Wood units; Y, yes. aInhaled nitric oxide and inhaled iloprost are recommended; intravenous epoprostenol can be used if inhaled nitric oxide or inhaled iloprost are unavailable. bSee text for details. cmPAP ≤30 mmHg and PVR ≤4 WU. Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026