p.12 抽出テキスト
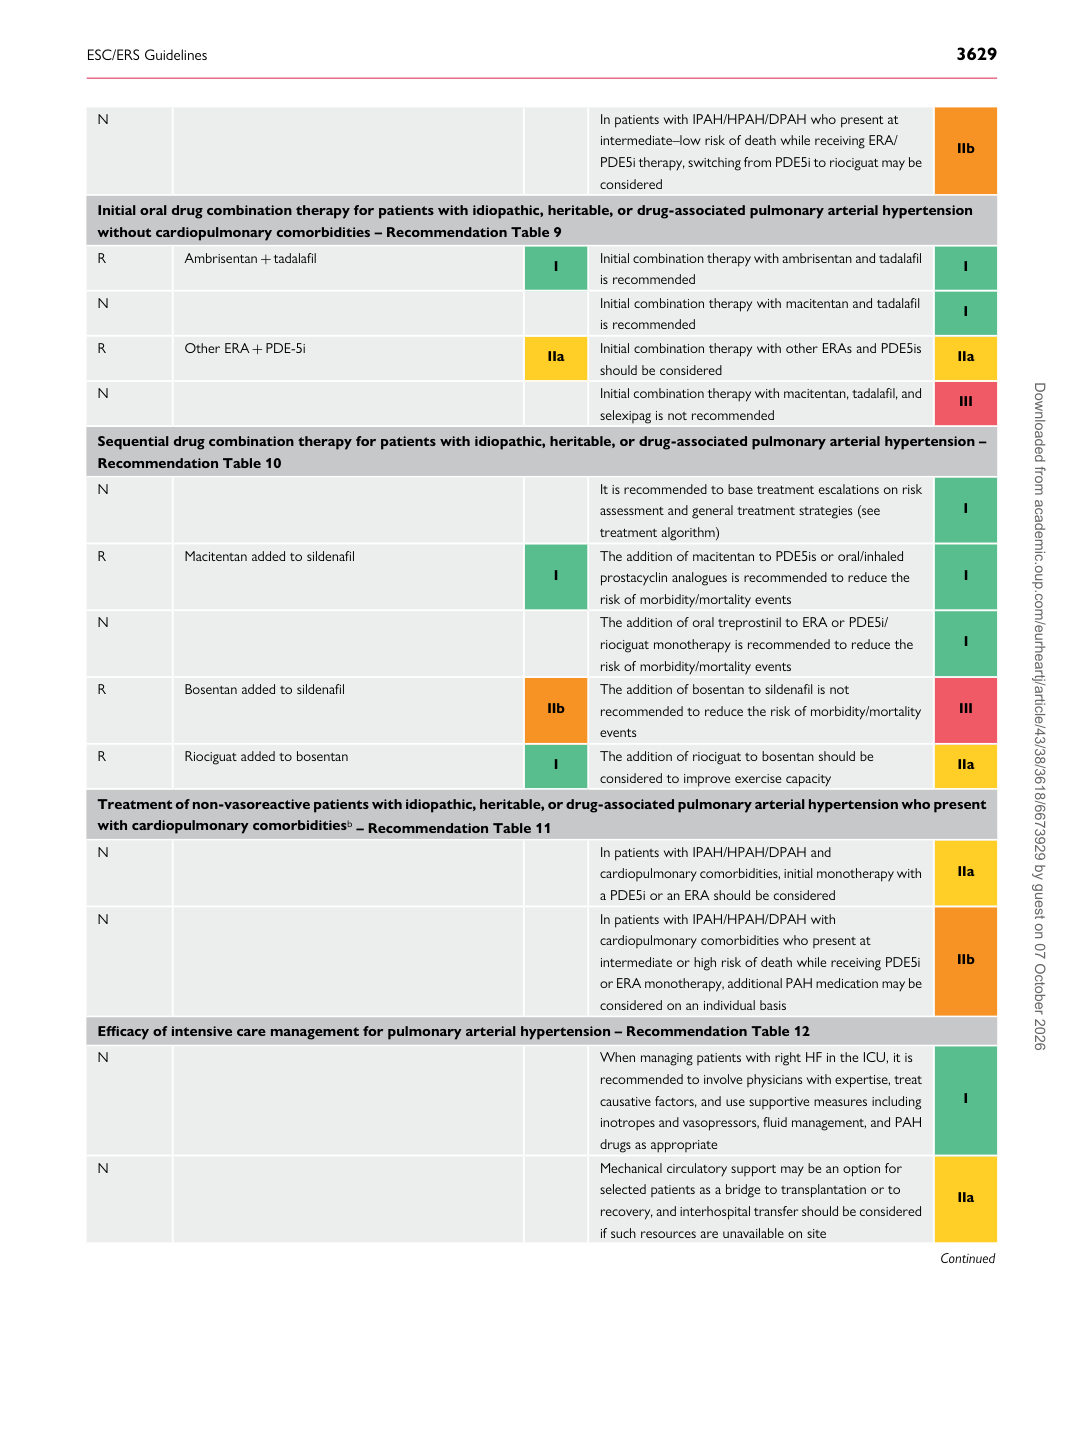
N In patients with IPAH/HPAH/DPAH who present at

intermediate–low risk of death while receiving ERA/ PDE5i therapy, switching from PDE5i to riociguat may be considered IIb

Initial oral drug combination therapy for patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension without cardiopulmonary comorbidities – Recommendation Table 9 R Ambrisentan + tadalafil I Initial combination therapy with ambrisentan and tadalafil

is recommended I

N Initial combination therapy with macitentan and tadalafil

is recommended I

R Other ERA + PDE-5i IIa Initial combination therapy with other ERAs and PDE5is

should be considered IIa

N Initial combination therapy with macitentan, tadalafil, and

selexipag is not recommended III

Sequential drug combination therapy for patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension – Recommendation Table 10 N It is recommended to base treatment escalations on risk

assessment and general treatment strategies (see treatment algorithm) I

R Macitentan added to sildenafil

I The addition of macitentan to PDE5is or oral/inhaled

prostacyclin analogues is recommended to reduce the risk of morbidity/mortality events I

N The addition of oral treprostinil to ERA or PDE5i/

riociguat monotherapy is recommended to reduce the risk of morbidity/mortality events I

R Bosentan added to sildenafil

IIb The addition of bosentan to sildenafil is not

recommended to reduce the risk of morbidity/mortality events III

R Riociguat added to bosentan I The addition of riociguat to bosentan should be considered to improve exercise capacity IIa Treatment of non-vasoreactive patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension who present with cardiopulmonary comorbiditiesb – Recommendation Table 11 N In patients with IPAH/HPAH/DPAH and cardiopulmonary comorbidities, initial monotherapy with

a PDE5i or an ERA should be considered IIa

N In patients with IPAH/HPAH/DPAH with

cardiopulmonary comorbidities who present at intermediate or high risk of death while receiving PDE5i or ERA monotherapy, additional PAH medication may be considered on an individual basis IIb

Efficacy of intensive care management for pulmonary arterial hypertension – Recommendation Table 12 N When managing patients with right HF in the ICU, it is

recommended to involve physicians with expertise, treat causative factors, and use supportive measures including inotropes and vasopressors, fluid management, and PAH drugs as appropriate I

N Mechanical circulatory support may be an option for

selected patients as a bridge to transplantation or to recovery, and interhospital transfer should be considered if such resources are unavailable on site IIa

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026