p.11 抽出テキスト
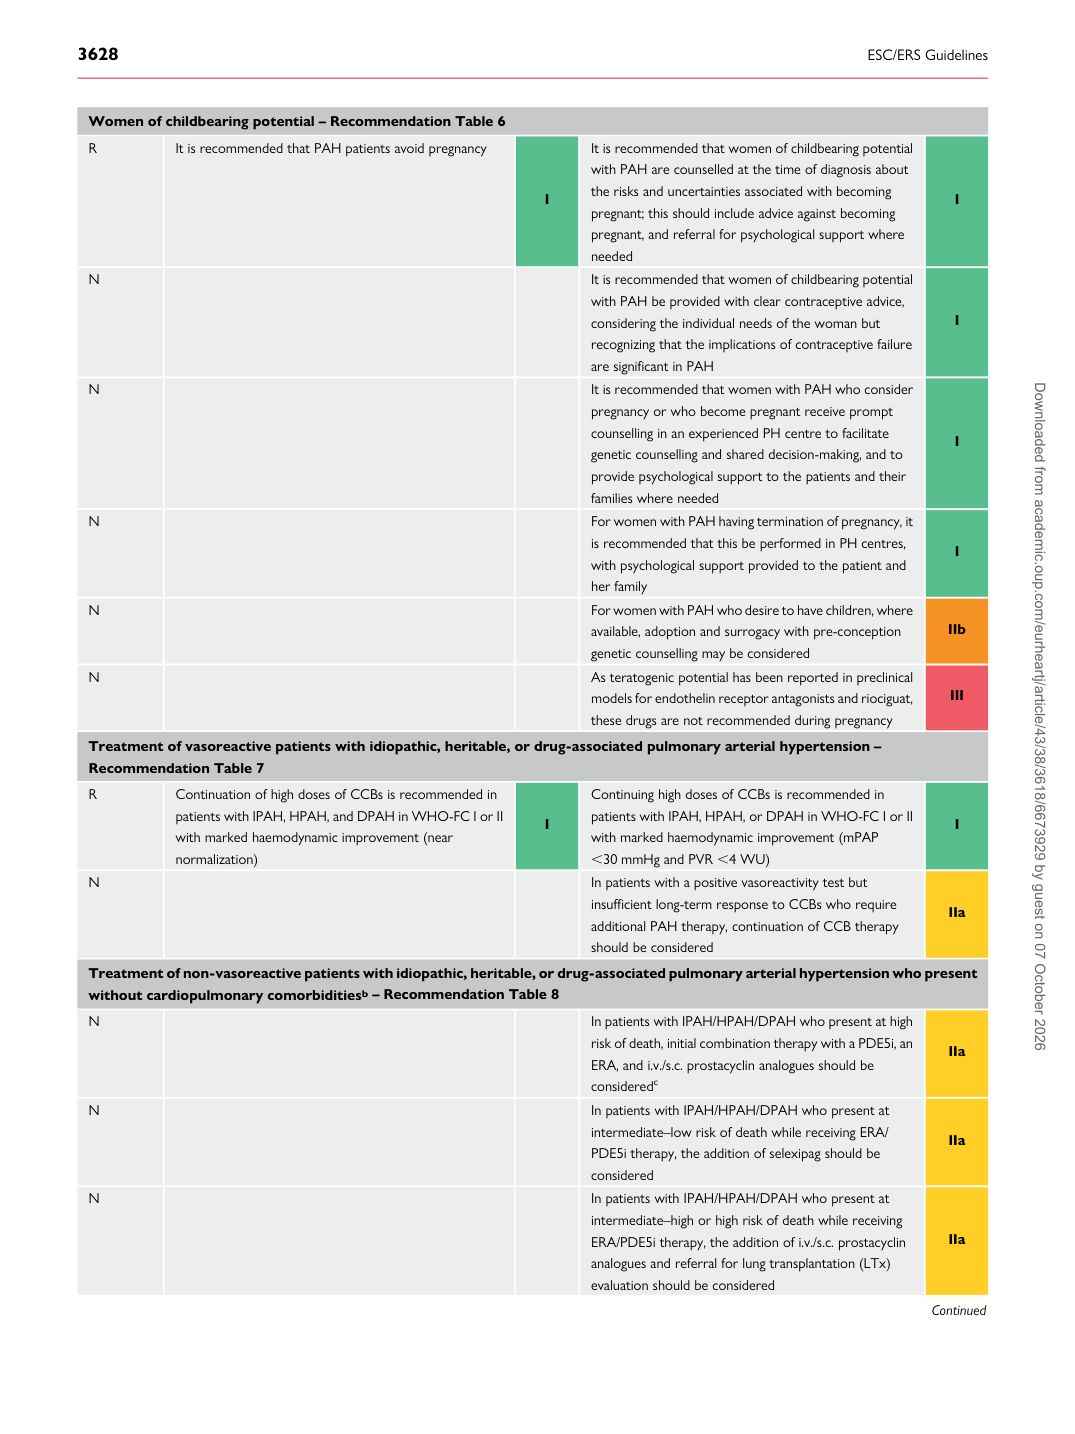
Women of childbearing potential – Recommendation Table 6 R It is recommended that PAH patients avoid pregnancy

I It is recommended that women of childbearing potential

with PAH are counselled at the time of diagnosis about the risks and uncertainties associated with becoming pregnant; this should include advice against becoming pregnant, and referral for psychological support where needed I

N It is recommended that women of childbearing potential

with PAH be provided with clear contraceptive advice, considering the individual needs of the woman but recognizing that the implications of contraceptive failure are significant in PAH I

N It is recommended that women with PAH who consider

pregnancy or who become pregnant receive prompt counselling in an experienced PH centre to facilitate genetic counselling and shared decision-making, and to provide psychological support to the patients and their families where needed I

N For women with PAH having termination of pregnancy, it is recommended that this be performed in PH centres,

with psychological support provided to the patient and her family I

N For women with PAH who desire to have children, where

available, adoption and surrogacy with pre-conception genetic counselling may be considered IIb

N As teratogenic potential has been reported in preclinical models for endothelin receptor antagonists and riociguat,

these drugs are not recommended during pregnancy III

Treatment of vasoreactive patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension – Recommendation Table 7 R Continuation of high doses of CCBs is recommended in

patients with IPAH, HPAH, and DPAH in WHO-FC I or II with marked haemodynamic improvement (near normalization) I Continuing high doses of CCBs is recommended in

patients with IPAH, HPAH, or DPAH in WHO-FC I or II with marked haemodynamic improvement (mPAP ,30 mmHg and PVR ,4 WU) I

N In patients with a positive vasoreactivity test but

insufficient long-term response to CCBs who require additional PAH therapy, continuation of CCB therapy should be considered IIa

Treatment of non-vasoreactive patients with idiopathic, heritable, or drug-associated pulmonary arterial hypertension who present without cardiopulmonary comorbiditiesb – Recommendation Table 8 N In patients with IPAH/HPAH/DPAH who present at high risk of death, initial combination therapy with a PDE5i, an

ERA, and i.v./s.c. prostacyclin analogues should be consideredc IIa

N In patients with IPAH/HPAH/DPAH who present at

intermediate–low risk of death while receiving ERA/ PDE5i therapy, the addition of selexipag should be considered IIa

N In patients with IPAH/HPAH/DPAH who present at

intermediate–high or high risk of death while receiving ERA/PDE5i therapy, the addition of i.v./s.c. prostacyclin analogues and referral for lung transplantation (LTx) evaluation should be considered IIa

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026